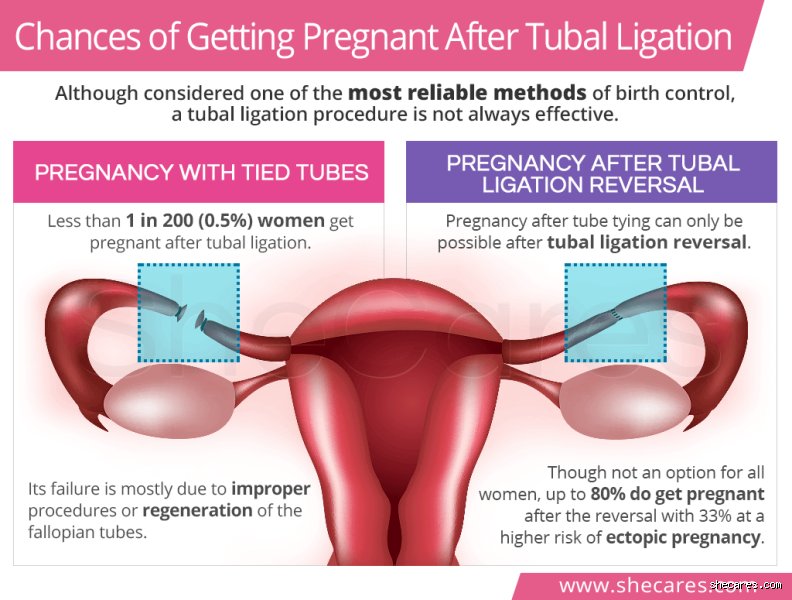
Understanding Tubal ligation and its purpose as permanent contraception
The procedure involves sealing, cutting, banding, or removing sections of the fallopian tubes. By interrupting the physical continuity of these vital pathways, the mechanics of natural conception are successfully blocked. Normally, fertilization occurs when an oocyte (egg) released from the ovary travels into the fallopian tube, where it meets and fuses with a sperm cell travelling upward from the uterus. When the fallopian tubes are blocked or excised, sperm can no longer reach the egg, and the egg cannot travel down into the uterine cavity, effectively preventing conception before it can even begin.
However, life circumstances, relationship changes, or shifts in personal perspective can sometimes lead individuals to reconsider their family planning goals. While medical professionals advise patients to approach tubal ligation with the absolute certainty that they will never desire future pregnancies, medical science recognizes that life is unpredictable. When a pregnancy does occur after a tubal ligation—either through spontaneous recanalization (where the divided tube unexpectedly grows back together) or through surgical reversal or assisted reproductive technologies—important medical questions arise regarding the safety and risk profile of that pregnancy.
Defining the core risk: The spectrum of High-Risk pregnancies
To accurately address whether a pregnancy following tubal ligation is considered "high risk," it is essential to first understand how obstetricians and gynecologists define high-risk status. A high-risk pregnancy is generally defined as any pregnancy that carries an increased health threat to the pregnant individual, the developing fetus, or both. These risks can stem from preexisting medical conditions, maternal age, lifestyle factors, or specific complications unique to the anatomical environment of the pregnancy itself.
When examining pregnancies that happen spontaneously after a tubal ligation has healed, the classification "high risk" is not just a theoretical label; it points directly to specific, well-documented physiological dangers. The most profound and critical risk associated with a post-sterilization pregnancy is the drastically elevated incidence of an ectopic pregnancy, a condition where the fertilized egg implants outside the main cavity of the uterus.
Why Tubal ligation heightens Ectopic pregnancy Risks
Under normal physiological circumstances, a fertilized embryo is gently transported down the fallopian tube toward the uterus by microscopic, hair-like projections called cilia, coupled with muscular contractions of the tube wall. When a tubal ligation is performed, the internal architecture, muscle function, and cellular lining of the fallopian tubes are altered, scarred, or partially destroyed.
If the sterilization fails and a sperm somehow manages to fertilize an egg despite the barrier, the compromised condition of the tube frequently prevents the resulting embryo from completing its journey to the uterus. Instead, the embryo implants prematurely within the narrow, delicate tissue of the fallopian tube itself.
Statistical Significance: Landmark epidemiological research, including classic studies published in journals such as the New England Journal of Medicine, has consistently demonstrated that while tubal ligation dramatically lowers the overall absolute number of pregnancies, if a pregnancy does occur after the procedure, the proportion of those pregnancies that are ectopic is significantly higher than in the general population, with estimates ranging widely depending on the specific type of sterilization performed (such as bipolar coagulation versus unipolar coagulation or clips) (Peterson et al., 1997).
Clinical Urgency: An ectopic pregnancy is an acute medical emergency. Unlike the uterus, which is muscular and designed to stretch exponentially to accommodate a growing fetus, the fallopian tube has virtually no capacity for expansion. As the ectopic embryo grows, it stretches and eventually ruptures the tubal wall, triggering severe internal hemorrhage, profound maternal shock, and potentially fatal consequences if immediate surgical or medical intervention is not administered.
Spontaneous conception vs. Planned fertility Pathways
When evaluating the risk profile of a pregnancy following tubal ligation, medical specialists separate scenarios into two fundamentally different categories: spontaneous post-sterilization pregnancies (where the sterilization failed unexpectedly) and planned pregnancies achieved via fertility treatments (such as tubal ligation reversal surgery or in vitro fertilization).
1. Spontaneous pregnancies due to sterilization failure
When an individual discovers they are pregnant despite having undergone a tubal ligation, panic and confusion are common initial reactions. Because the presence of a tubal scar inherently disrupts normal implantation pathways, clinicians immediately treat any positive pregnancy test in a sterilized patient as a suspected ectopic pregnancy until an early transvaginal ultrasound and serial human chorionic gonadotropin (hCG) blood tests can definitively prove otherwise.
Beyond the immediate threat of ectopic implantation, spontaneous pregnancies that successfully implant within the uterus do not inherently carry exponentially higher risks of standard obstetric complications solely due to the prior sterilization, provided the procedure was uncomplicated. However, the psychological stress, delayed diagnosis due to the assumption of permanent sterility, and the baseline maternal health factors (such as age or chronic medical conditions that may have evolved since the initial sterilization) must all be carefully monitored by a maternal-fetal medicine specialist or obstetrician.
2. Pregnancies following Tubal Reversal surgery
For individuals who actively desire to restore their natural fertility, surgeons can perform a microsurgical procedure known as a tubal reversal (tubal reanastomosis). This intricate operation involves reconnecting the remaining segments of the fallopian tubes. While successful reversal allows many patients to achieve natural intrauterine pregnancies, the structural alterations, scar tissue (adhesions), and shortened tube lengths mean that the reconstructed tubes may still function suboptimally.
Clinical data comparing reproductive outcomes show that while tubal reversal can successfully yield healthy live births, it continues to carry a notably higher risk of ectopic pregnancy compared to non-sterilized populations or pregnancies achieved via assisted reproduction. Studies indicate that ectopic pregnancy rates following tubal reversal can range anywhere from 4% to 15%, depending on the original method of sterilization used and the skill of the microsurgeon (Neef, 2026). The overall live birth rates following reversal decline sharply as maternal age advances, making comprehensive age-based pre-conception counseling vital.
3. Pregnancies following in Vitro Fertilization (IVF)
In contrast to natural conception following tubal reversal, many patients and fertility specialists choose In Vitro Fertilization (IVF) as the preferred pathway to pregnancy after tubal ligation. IVF completely bypasses the fallopian tubes by stimulating the ovaries, retrieving mature eggs, fertilizing them in a specialized laboratory environment, and transferring a healthy embryo directly through the cervix and into the uterine cavity.
Because the fallopian tubes are bypassed entirely during an IVF cycle, the statistical risk of an ectopic pregnancy drops dramatically, typically mirroring baseline population risks of roughly 1% to 2%, rather than the elevated rates seen with natural or surgically reconnected conceptions (Neef, 2026). For patients wishing to expand their families post-sterilization without taking on the heightened anatomical risks associated with damaged or reconstructed fallopian tubes, IVF represents a structurally safer alternative from an implantation standpoint, though it carries its own distinct set of considerations regarding medication protocols, costs, and multiple-pregnancy monitoring.
pregnancy after tubal ligation high risk"
Navigating pregnancy after Tubal ligation: Risks, realities, and Clinical management
While permanent contraception is designed to be irreversible, life circumstances, changes in relationship status, or evolving family goals lead a small percentage of women to seek pregnancy after undergoing a tubal ligation. Whether achieving pregnancy via (IVF) or through a rare spontaneous recanalization, prospective parents are often met with a barrage of medical terminology and anxiety regarding potential complications.
Understanding whether a post-ligation pregnancy is high risk requires parsing the method of conception, the structural integrity of the fallopian tubes, and the vigilant monitoring required by maternal-fetal medicine specialists.
Understanding the mechanics: Spontaneous conception vs. Assisted reproduction
The level of risk and the nature of potential complications in a pregnancy following tubal ligation depend heavily on how the pregnancy was achieved. Medical science generally categorizes these scenarios into two distinct pathways:
1. Spontaneous pregnancy after failed ligation
Tubal ligation is remarkably effective, boasting a failure rate of less than 1% over ten years. However, no permanent sterilization method is 100% foolproof. Failures can occur due to incomplete occlusion, fistula formation (where a new channel forms through the scarred tube), or spontaneous re-anastomosis (the tube healing itself).
When a woman conceives naturally despite having had her tubes tied, the immediate and overriding medical concern is ectopic pregnancy, a condition where the fertilized egg implants outside the main cavity of the uterus, most commonly within the scarred fallopian tube.
The Ectopic Threat: Because the fallopian tubes have been cauterized, clipped, or tied, their normal muscular contractions (peristalsis) and internal architecture are severely disrupted. If a slow-moving sperm manages to fertilize an egg, the resulting embryo often becomes trapped in the damaged tube.
Incidence: While overall pregnancy rates after tubal ligation are low, a disproportionate percentage of those that do occur are ectopic. An ectopic pregnancy is a life-threatening medical emergency requiring immediate intervention to prevent tubal rupture and severe internal hemorrhage.
2. Pregnancy following Tubal Reversal surgery or IVF
Many women who regret their sterilization opt for or bypass the tubes entirely via IVF.
Post-Reversal Risks: Tubal reversal restores the patency of the tubes, allowing for natural intrauterine conception. However, the surgical site on the tube remains a locus of scar tissue (). While the risk of ectopic pregnancy is significantly lower than in an unreversed, failed ligation, it remains higher than in the general, non-sterilized population, typically hovering around 4% to 10%.
IVF Pathways: For women undergoing IVF, the fallopian tubes are bypassed entirely because the embryo is transferred directly into the uterine cavity. Consequently, the statistical risk of an ectopic pregnancy drops dramatically, aligning closely with standard IVF risk profiles. However, advanced maternal age, often a factor for women revisiting family planning later in life, introduces other gestational considerations such as gestational diabetes, hypertension, and chromosomal variations.
Comprehensive risk stratification and Clinical surveillance
When an intrauterine pregnancy is successfully confirmed following tubal ligation or its reversal, obstetricians typically classify the pregnancy as high risk, necessitating an elevated level of prenatal care.
+-------------------------------------------------------------+
| POST-LIGATION PREGNANCY EVALUATION |
+-------------------------------------------------------------+
|
+-----------------------+-----------------------+
| |
v v
[Spontaneous / Reversal] [IVF Pathway]
- High Ectopic Vigilance - Bypasses Tubal Pathology
- Early Serial hCG Tracking - Gestational Age Monitoring
- Targeted First-Trimester Scan - Age-Related Complication Screening
First-Trimester Vigilance
The cornerstone of managing a post-ligation pregnancy is early and aggressive evaluation.
Serial Quantitative hCG Testing: In the earliest weeks, blood tests monitoring human chorionic gonadotropin levels help clinicians determine whether the pregnancy is progressing normally.
Early Transvaginal Ultrasonography: As soon as hCG levels cross the "discriminatory zone" (typically 1,500 to 2,000 mIU/mL), an ultrasound is performed to definitively locate the gestational sac inside the uterine cavity. Confirming an intrauterine location rules out a dangerous tubal ectopic pregnancy.
Second and Third-Trimester Monitoring
Once an intrauterine pregnancy is established and reaches the second trimester, the direct mechanical risks posed by the tubal ligation diminish. However, secondary risk factors must still be managed:
Placental Placement: Scarring from prior tubal surgeries or pelvic inflammatory history can occasionally influence uterine receptivity, though direct structural impact on placental attachment (such as placenta accreta) is more commonly associated with prior uterine surgery (like cesarean sections) rather than tubal surgery.
Maternal Age and Comorbidities: Because sterilization reversal and IVF are often pursued later in reproductive life, maternal age plays a major role. Advanced maternal age increases the baseline risk for gestational complications, requiring detailed anatomical survey ultrasounds at 18 to 20 weeks and rigorous blood pressure monitoring.
Psychological and emotional dimensions
Navigating a pregnancy after choosing permanent sterilization is uniquely complex. Expectant mothers frequently experience a whirlwind of conflicting emotions:
Surprise and Shock: In cases of spontaneous failure, the sudden reality of an unintended pregnancy after making a permanent life choice can induce acute stress and disbelief.
Guilt or Validation: Women who pursued reversal often battle intense emotional pressure, feeling that they must justify their renewed desire for children, while simultaneously managing the physical anxieties of higher-risk monitoring.
Uncertainty: The early weeks of waiting for ultrasound confirmation to rule out an ectopic pregnancy can exact a heavy psychological toll, requiring empathetic support from healthcare providers and counseling resources.
Summary and Clinical recommendations
Pregnancy after tubal ligation is entirely possible, but it is not without distinct clinical hurdles. Whether resulting from a rare procedural failure, a successful surgical reversal, or advanced reproductive technology like IVF, these pregnancies demand heightened medical awareness, primarily due to the elevated risk of ectopic implantation in natural conceptions.
Prospective parents should establish care with an obstetrician-gynecologist or a maternal-fetal medicine specialist immediately upon a positive pregnancy test. Through rigorous early ultrasound tracking, vigilant symptom monitoring, and personalized prenatal care, the vast majority of women navigating this unique reproductive path successfully transition from high-risk monitoring to the delivery of a healthy baby.