Understanding Tubal Ligation and its effectiveness
How Tubal Ligation works
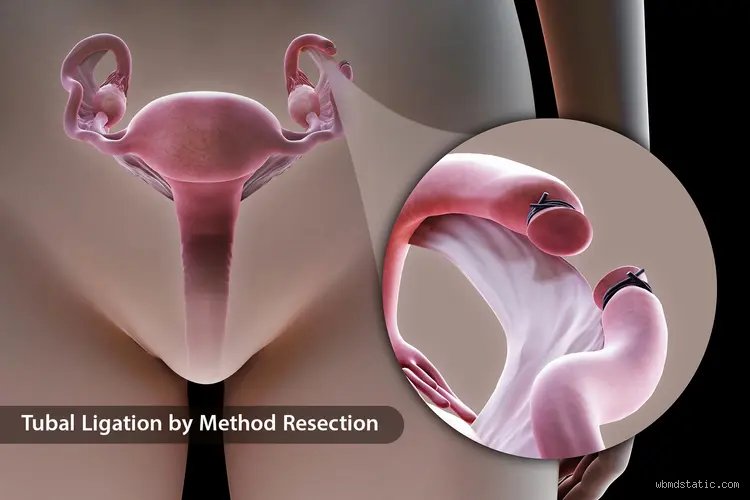
To comprehend why or how a failure might happen, it helps to first look at the mechanics of the procedure. The fallopian tubes are two thin, muscular channels that connect the ovaries to the uterus. Each month, during ovulation, an ovary releases an egg into the abdominal cavity, where it is swept into the opening of the fallopian tube. Fertilization—the meeting of sperm and egg—normally takes place within the ampulla of the fallopian tube. Once fertilized, the egg travels down the tube into the uterine cavity to implant and develop.
Tubal ligation physically interrupts this pathway. A surgeon seals, cuts, ties, or removes portions of the fallopian tubes using various techniques:
Bilateral Tubal Ligation (BTL): Sections of the tubes are tied off and cut, or removed entirely (salpingectomy).
Clips and Rings: Specialized medical devices are clamped over the tubes to block them.
Electrocoagulation: An electric current is used to cauterize and seal segments of the tubes.
By blocking or removing these pathways, sperm are physically prevented from reaching an egg, and eggs are prevented from traveling to the uterus.
Statistical overview of effectiveness
Statistically, tubal ligation is remarkably effective. According to data from organizations like the American College of Obstetricians and Gynecologists (ACOG) and the Centers for Disease Control and Prevention (CDC), the cumulative failure rate is very low, but it varies slightly depending on the specific technique used and the timeframe evaluated.
First Year Failure Rate: Generally, fewer than 1 out of every 100 women (approximately 0.5% to 1.8% depending on the method) will experience a pregnancy in the first year following the procedure.
Long-Term Efficacy: Over a 10-year period, the cumulative failure rate rises slightly, generally settling between 1 and 2 pregnancies per 100 procedures. The younger a person is at the time of the surgery, the higher the lifetime statistical chance of a rare failure, primarily because younger tissue has a more robust capacity for cellular healing and biological recanalization.
The biological phenomenon of recanalization
Why would a procedure designed to be permanent ever fail? The human body possesses an extraordinary capacity for healing and regeneration. In rare instances, the blocked ends of the fallopian tubes manage to heal and reconnect over time, a process known as recanalization.
Fistula Formation: Sometimes, a microscopic channel or fistula forms within the scar tissue of a sealed tube, allowing sperm to pass through to an egg despite the physical barrier.
Incomplete Occlusion: In extremely rare cases, a tube may not have been fully sealed or clipped correctly during the initial surgery, though modern surgical verification greatly minimizes this risk.
Types of pregnancies associated with Tubal Ligation Failure
When a tubal ligation fails, the resulting pregnancy carries unique medical implications that distinguish it from a standard intrauterine pregnancy.
Intrauterine Pregnancy: A standard pregnancy where the fertilized egg successfully travels past the compromised blockage and implants in the uterus. While rare, these do occur.
Ectopic Pregnancy: This is a critical risk factor. Because the fallopian tubes are scarred, damaged, or partially blocked, a fertilized egg may become trapped inside the tube instead of reaching the uterus. An ectopic pregnancy is a medical emergency that requires immediate intervention, as the fallopian tube can rupture and cause severe internal bleeding.
Recognizing the subtle signs and symptoms of a potential failure is vital for timely diagnosis and safeguarding reproductive health.
Understanding the hidden signs: Diagnostic workup and Medical validation
While a missed menstrual cycle or tender breasts often serve as the first major indicators that a permanent birth control method may have been compromised, confirming a tubal ligation failure requires a precise clinical approach. Because the anatomy of the reproductive tract has been altered, traditional home tracking methods can sometimes blur the presentation of symptoms.
The essential role of clinical testing
If you suspect your sterilization procedure has failed, self-assessment alone is insufficient. Healthcare providers rely on a multi-tiered diagnostic framework to differentiate between a normal intrauterine pregnancy, an unruptured ectopic pregnancy, or unrelated endocrine shifts:
Quantitative Beta-hCG Blood Tests: Unlike standard qualitative urine tests that simply show a positive or negative result, serial blood draws measure the exact concentration of human chorionic gonadotropin. In a viable intrauterine pregnancy, these hormone numbers typically double every 48 to 72 hours. Abnormal or sluggish increases heavily flag the possibility of an abnormal implantation site.
Transvaginal Ultrasound: This imaging modality allows clinicians to visualize the uterine cavity directly. If a gestational sac is absent from the uterus despite a positive hormone reading, suspicion immediately shifts toward an extrauterine location.
Laparoscopic Exploration: In ambiguous cases where imaging is inconclusive and hormone levels remain persistently abnormal, direct visualization via a minimally invasive surgical procedure may be required to locate the gestational tissue and protect maternal health.
Critical red flags: Recognizing Ectopic emergencies
The most hazardous aspect of a tubal ligation failure is the disproportionately high rate of ectopic pregnancies, situations where the fertilized egg implants inside the damaged or scarred remnant of the fallopian tube rather than traveling safely to the uterus (Pantigoso-Gutierrez, 0). Because fallopian tubes lack the muscular elasticity of the uterus, they cannot safely accommodate a growing embryo (Miscarriage UK, 2026).
Medical Warning: An ectopic pregnancy is a life-threatening medical emergency. If left untreated, the expanding tissue can cause the fallopian tube to rupture, leading to severe internal hemorrhage, shock, and potentially fatal complications.
Symptoms requiring immediate Medical attention
You should bypass routine scheduling and seek emergency medical care immediately if you experience any of the following warning signs alongside a positive pregnancy test:
Unilateral Pelvic or Abdominal Sharp Pain: A localized, stabbing, or severe cramping pain concentrated heavily on one side of the lower abdomen.
Abnormal Vaginal Bleeding: Spotting or bleeding that differs significantly from a normal period, often appearing watery, dark brown, or resembling "prune juice."
Referred Shoulder-Tip Pain: A unique, sharp pain felt near the tip of the shoulder. This occurs when internal bleeding accumulates in the abdomen and irritates the phrenic nerve beneath the diaphragm.
Systemic Shock Symptoms: Sudden lightheadedness, dizziness, fainting spells, clammy skin, or a rapid pulse, which signal significant internal blood loss.
Long-Term reproductive health and Post-Failure care
Navigating a failed sterilization procedure involves both immediate medical intervention and thoughtful future planning. Once an ectopic or intrauterine pregnancy is safely managed, patients face crucial decisions regarding their ongoing contraceptive and reproductive health.
Evaluating future contraceptive options
If a patient wishes to remain permanently childfree after a tubal failure, relying on another tubal procedure is generally discouraged due to the underlying anatomical factors that caused the initial failure (such as tissue regeneration or recanalization). Instead, healthcare providers frequently counsel patients toward alternatives with exceptionally low failure rates, such as long-acting reversible contraceptives (LARCs) like the hormonal or copper intrauterine device (IUD), or shifting permanent sterilization responsibilities to a partner via a vasectomy.
Conversely, for individuals who experience a change in life circumstances and desire a future pregnancy, specialized surgical evaluations, such as a tubal ligation reversal or utilizing assisted reproductive technologies like in vitro fertilization (IVF), may be discussed with a reproductive endocrinologist once the body has fully healed.
Summary and actionable takeaways
Though tubal ligations remain among the most reliable forms of permanent birth control available, vigilance is paramount. Understanding that the procedure is not entirely infallible empowers you to listen to your body and act swiftly.
Trust your instincts: If your body feels pregnant or you experience irregular cycle changes post-sterilization, take a home test immediately.
Prioritize speed: A positive test following a tubal ligation requires prompt medical confirmation to rule out dangerous extrauterine implantations.
Know when to seek emergency care: Severe one-sided pelvic pain, shoulder pain, or dizziness demand an immediate visit to the nearest emergency department.