Navigating the Long-Term Landscape of Tubal Ligation: What the Science and Clinical Realities Tell Us
Tubal ligation, commonly referred to as "having one's tubes tied," stands as one of the most prevalent and permanent forms of female sterilization worldwide. For millions of individuals, it offers a definitive, highly effective method of birth control, liberating them from the daily cognitive and physiological load of maintaining temporary contraceptive regimens. However, as individuals age and move past the immediate postoperative recovery window, questions regarding the enduring bodily consequences inevitably surface. Patients often search for clarity on whether the procedure casts a long shadow over their hormonal health, menstrual patterns, and overall physical well-being.
Addressing these concerns requires an objective, nuanced examination of what mainstream medical research confirms, what remains clinically debated, and how the intricate anatomy of the female pelvis reacts over decades. While the procedure itself is designed to be a safe, localized mechanical block of the fallopian tubes—preventing sperm from reaching an egg—the broader physiological ripples of undergoing permanent pelvic surgery warrant a thorough, evidence-based review.
The Anatomical Reality: How Tubal Ligation Works
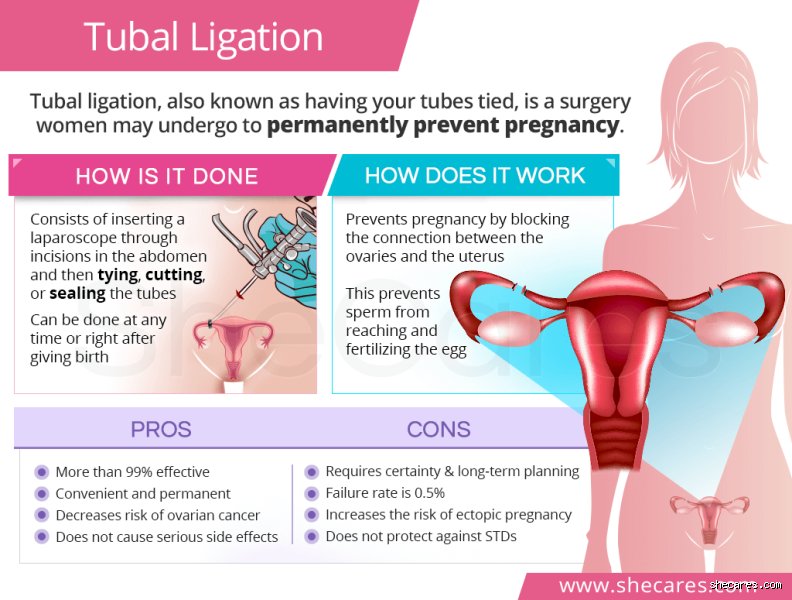
To understand potential long-term downstream effects, one must first look at the mechanics of the procedure. Tubal ligation involves sealing, cutting, banding, or removing sections of the fallopian tubes. Surgical techniques have evolved over decades, ranging from laparoscopic electrocoagulation and silicone rings (tubs bands) to mini-laparotomy and complete bilateral salpingectomy (the total removal of the fallopian tubes, which is increasingly favored today not only for contraception but also for its ovarian cancer risk-reduction benefits).
Crucially, traditional tubal ligation does not remove or structurally alter the ovaries or the uterus. The ovaries continue to function as endocrine organs, synthesizing and releasing estrogen and progesterone on a cyclical basis, and releasing eggs into the pelvic cavity where they are safely reabsorbed by the body. Because the primary hormonal factories remain completely intact, mainstream gynecological consensus maintains that a standard tubal ligation does not induce premature menopause or cause a direct chemical castration effect.
+--------------------------------------------------------------------------+
| OVARIAN HORMONAL AXIS |
| |
| [ Ovaries Intact ] ---> Produce Estrogen & Progesterone (Normal) |
| | |
| v |
| [ Fallopian Tubes ] --> Mechanically Blocked or Removed (Sterilized) |
| | |
| v |
| [ Uterus / Endometrium ] ---> Cyclical Shedding / Menstruation Continues|
+--------------------------------------------------------------------------+
Disentangling Menstrual Changes and the "Post-Tubal Ligation Syndrome" Debate
One of the most frequent long-term complaints reported by patients years after surgery is a noticeable shift in their menstrual cycles. Individuals often note heavier bleeding, more severe cramping (dysmenorrhea), shorter cycle intervals, or intensified premenstrual syndrome (PMS) symptoms. This cluster of grievances has historically been channeled into a heavily debated concept known in alternative and holistic circles as Post-Tubal Ligation Syndrome (PTLS) (Dias et al., 2014).
The Clinical Stance on PTLS
Within formal, evidence-based gynecology, PTLS is not recognized as a distinct, validated medical diagnosis (Dobson, 2026; DiagMe, 2025). Large-scale epidemiological studies comparing sterilized women to non-sterilized control cohorts have consistently failed to isolate a unique, direct endocrinological mechanism where blocking the fallopian tubes compromises ovarian blood flow or disrupts systemic hormone production enough to trigger a uniform syndrome.
Instead, mainstream medicine attributes these observed post-procedure changes to several distinct, overlapping factors:
The Cessation of Hormonal Contraception: A vast majority of women transition directly from long-term hormonal birth control (such as oral contraceptive pills, hormonal intrauterine devices, or injectable depot medroxyprogesterone acetate) to a tubal ligation. Hormonal contraceptives are famous for suppressing natural endometrial growth, resulting in lighter, shorter, and less painful bleeds. Once those medications are stopped and replaced by a mechanical barrier method, the patient's body returns to its true, unmedicated baseline. What feels like a "side effect" of the surgery is often simply the unmasking of the individual’s natural, heavier, and more turbulent baseline cycle.
Aging and Natural Perimenopause: Tubal ligation is most frequently performed on individuals who have completed their families, often in their late 30s or early 40s. This life stage naturally coincides with the onset of perimenopause—a multi-year transition marked by erratic hormone fluctuations, heavier or irregular periods, mood alterations, and vasomotor symptoms like night sweats. It is easy for patients and clinicians alike to mistakenly attribute natural biological aging to a surgical procedure performed years prior.
Vascular and Anatomical Alterations: While rare, some older theories suggested that altering the local mesosalpinx blood supply could theoretically impact ovarian responsiveness. However, physiological studies demonstrate that the ovaries receive a dual blood supply primarily from the ovarian arteries (branching directly off the aorta) and secondary collateral flow from the uterine arteries, making them remarkably resilient to localized tubal interruption.
Long-Term Psychosocial and Sexual Impacts
Beyond physical bleeding patterns, long-term side effects encompass psychological dimensions. For the vast majority, sterilization brings a profound sense of relief, sexual spontaneity, and psychological freedom from the anxiety of unplanned pregnancy. Studies show that when a tubal ligation is chosen freely without coercion, satisfaction rates remain remarkably high over decades.
Conversely, a subset of patients experiences long-term psychological regret. Risk factors for post-sterilization regret include:
Young age at the time of the procedure (particularly under age 30) (NCCRM, 2024).
Undergoing the procedure under duress (partner pressure, financial instability, or immediate postpartum emotional vulnerability).
Unforeseen life changes (such as divorce, the loss of a child, or entering a new relationship where a partner desires children).
When psychological regret sets in, it can manifest somatically as chronic pelvic pain, feelings of incomplete identity, or heightened anxiety, demonstrating how deeply intertwined mental health and pelvic well-being truly are.
Navigating the Long-Term Horizon: Life After Tubal Ligation
While the immediate recovery period following a tubal ligation is typically straightforward—involving a few days of rest and mild abdominal discomfort—the true narrative of permanent female sterilization unfolds over decades. As women move through different life stages following the procedure, questions regarding potential long-term side effects, physiological changes, and hormonal shifts frequently arise.
Understanding what is medically documented versus what remains anecdotal is essential for anyone evaluating this permanent form of birth control or trying to make sense of symptoms experienced years down the road.
The Hormone Controversy: Does Tubal Ligation Affect Ovarian Function?
One of the most persistent concerns surrounding long-term tubal ligation is its impact on menstrual cycles and hormonal balance. Many patients worry that clipping, tying, or removing the fallopian tubes will disrupt their natural endocrine rhythms, leading to premature aging, weight gain, or erratic periods.
The Role of Blood Supply and Ovarian Reserve
From an anatomical perspective, standard tubal ligation procedures—whether through laparoscopy, postpartum minilaparotomy, or hysteroscopic methods—target exclusively the fallopian tubes. The primary blood supply to the ovaries comes from the ovarian arteries, which branch directly from the aorta, whereas the fallopian tubes are supplied by both the ovarian and uterine arteries.
Preserved Ovarian Blood Flow: Standard tubal occlusion techniques are carefully designed to avoid compromising the vascular network feeding the ovaries. Consequently, baseline ovarian hormone production (estrogen and progesterone) remains fundamentally undisturbed.
Post-Tubal Sterilization Syndrome (PTSS): In the medical community, PTSS is a term historically used to describe a constellation of symptoms—including heavy periods, severe cramping, and irregular cycles—reported by some women after sterilization. However, extensive clinical research has consistently failed to validate PTSS as a distinct physiological disease caused by the procedure itself.
Why Cycles May Change Over Time
When women notice shifts in their menstrual patterns post-sterilization, the underlying cause is rarely the tubal ligation itself. Instead, two primary factors usually explain these changes:
Discontinuation of Hormonal Contraception: Many women transition from combined oral contraceptives, injectables, or hormonal intrauterine devices (IUDs) to tubal ligation. Hormonal contraceptives artificially regulate the menstrual cycle, often making periods lighter, shorter, and highly predictable. Returning to a natural, unsuppressed cycle often reveals a woman's true, baseline menstrual pattern, which may naturally feature heavier bleeding or more noticeable premenstrual symptoms.
Natural Aging and Perimenopause: Because tubal ligation is frequently performed in women in their late 20s, 30s, or 40s who have completed their families, chronological aging plays a major role. Natural perimenopausal hormonal fluctuations begin years before final menopause, frequently causing irregular cycles, mood shifts, and changes in flow intensity that coincide chronologically with having had a past sterilization procedure.
Potential Benefits and Protective Effects
While discussions often center on potential side effects, long-term epidemiological studies have revealed several notable health benefits and protective associations linked to tubal ligation.
1. Significant Reduction in Ovarian Cancer Risk
One of the most profound and unexpected long-term findings associated with tubal ligation is a substantially lowered risk of developing epithelial ovarian cancer, which accounts for the vast majority of ovarian malignancies.
The Tubal Origin Theory: Modern gynecological oncology has revolutionized our understanding of ovarian cancer. Many high-grade serous carcinomas—previously thought to originate strictly in the surface epithelium of the ovary—actually begin in the distal fimbriated ends of the fallopian tubes. Pre-malignant cellular changes often migrate from the tubes to the ovaries.
The Barrier Effect: By physically blocking, removing, or sealing the fallopian tubes, the procedure prevents potential carcinogenic or inflammatory fluid movement from the lower reproductive tract into the peritoneal cavity and onto the ovaries. Studies indicate that tubal ligation can reduce the risk of epithelial ovarian cancer by anywhere from twenty to forty percent, depending on the specific surgical technique used.
2. Elimination of Ectopic Pregnancy Risks
By permanently preventing sperm and egg from meeting within the fallopian tube, tubal ligation virtually eliminates the risk of tubal ectopic pregnancies—a potentially life-threatening medical emergency. While the rare occurrence of a post-sterilization pregnancy does carry a higher statistical likelihood of being ectopic, the absolute baseline risk of any pregnancy occurring after successful tubal occlusion is extremely low (typically estimated at less than one percent over a ten-year cumulative period).
Psychological and Emotional Outcomes Over Time
Long-term satisfaction following tubal ligation is generally very high, but psychological trajectories vary depending on age, life circumstances, and pre-existing mental health.
Peace of Mind and Sexual Well-Being
For the vast majority of women, knowing that accidental pregnancy is permanently prevented removes a significant psychological burden. This freedom from the anxiety of unplanned conception frequently translates into:
Enhanced spontaneity and intimacy in relationships.
Relief from the side effects or maintenance required by daily or short-term contraceptive methods (such as pill fatigue or hormonal mood swings).
A profound sense of bodily autonomy and closure regarding family planning.
Regret: Incidence and Risk Factors
While most women remain satisfied with their decision, a small percentage experience long-term regret. Clinical data highlights specific demographic and psychological predictors associated with higher rates of post-sterilization regret:
Young Age at Surgery: Women under the age of thirty at the time of the procedure report higher rates of future regret, largely because life circumstances, relationship statuses, and personal desires regarding children can evolve significantly over subsequent decades.
Decisions Made Under Duress: Procedures performed during high-stress life events, economic hardship, postpartum vulnerability, or under pressure from partners or medical providers strongly correlate with negative emotional outcomes later in life.
Marital Instability: Changes in family dynamics, such as divorce or the loss of a child, can profoundly alter a woman's perspective on permanent sterilization.
For those facing regret, options such as tubal reversal microsurgery or in vitro fertilization (IVF) exist, though success rates vary based on age and the specific method of sterilization initially used.
Long-Term Physical Complications and Rare Risks
While major long-term physical complications are uncommon, certain rare outcomes warrant awareness.
Pelvic Adhesions and Chronic Pain: Surgical interventions in the pelvic cavity can occasionally lead to the formation of scar tissue (adhesions). While rare with minimally invasive laparoscopic techniques, extensive adhesions can sometimes contribute to chronic pelvic pain or painful intercourse (dyspareunia).
Hysteroscopic Sterilization Considerations: For methods that involve placing micro-inserts into the fallopian tubes via hysteroscopy, long-term follow-up studies have occasionally noted reports of localized tissue irritation, chronic pelvic discomfort, or the rare need for subsequent surgical removal due to device migration. Healthcare providers monitor these outcomes closely to refine patient selection criteria.
Conclusion: Weighing the Long-Term Perspective
Tubal ligation remains a safe, highly effective, and permanent method of birth control that stands the test of time for millions of women worldwide. While it does not alter natural ovarian hormone production or induce premature menopause, it can coincide with normal aging processes and the cessation of hormonal contraceptives, which often explains shifts in menstrual patterns.
Ultimately, approaching permanent sterilization with thorough pre-procedure counseling, realistic expectations, and an acute awareness of both its physiological realities and emotional implications ensures the highest likelihood of long-term satisfaction and peace of mind.
Have you or someone you know explored the long-term impacts of permanent birth control, and what specific aspects of post-sterilization health matter most to you?