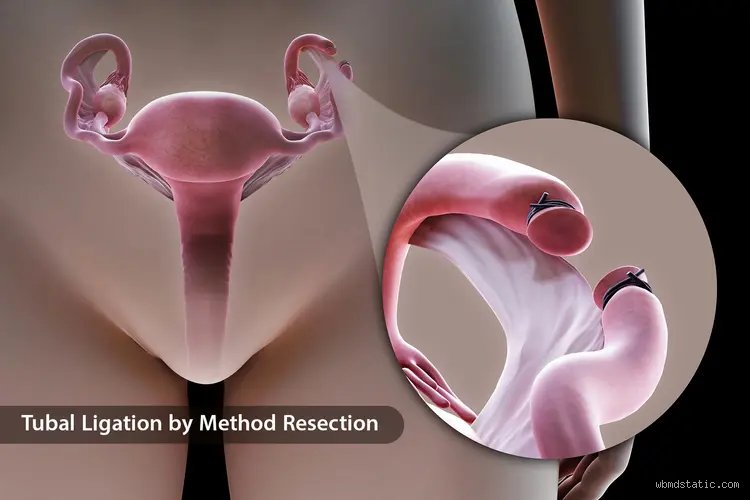
Evaluating whether the procedure is "bad for your body" requires a comprehensive, evidence-based look at what the surgery entails, how it interacts with normal physiological and hormonal functions, and what modern medical science says about its short- and long-term impacts.
1. Demystifying tubal Ligation: What actually happens to the body?
To understand how tubal ligation affects the body, it is essential to first clarify the exact mechanical function of the procedure. The colloquial phrase "getting your tubes tied" is an oversimplification; modern surgical techniques involve cutting, sealing, clipping, or removing sections of the fallopian tubes.
The fallopian tubes are muscular, mucosa-lined channels that connect the ovaries to the uterus. Their primary biological purpose is to serve as the transit pathway for an egg released during ovulation, allowing it to meet sperm and travel to the uterine cavity for implantation.
The Ovaries Remain Intouched: During a standard tubal ligation, the ovaries—which produce estrogen, progesterone, and release eggs, are left completely intact and functional.
The Hormonal Axis is Preserved: Because the ovaries continue to function normally, the body’s natural endocrine (hormonal) rhythms do not stop. Menstruation continues as it did before surgery, regulated by the same hormonal feedback loops involving the hypothalamus, pituitary gland, and ovaries.
The Uterus is Unaltered: The uterus itself remains structurally unchanged, meaning monthly endometrial shedding (periods) continues according to each individual's baseline cycle.
2. Physiological mechanisms: Sorting fact from fiction
One of the most persistent fears regarding tubal ligation is the notion that it causes premature aging, weight gain, mood instability, or early menopause. In clinical literature, these concerns are often mistakenly conflated with natural hormonal shifts or a phenomenon sometimes discussed in older medical communities called "tubal ligation syndrome."
However, extensive clinical studies and data from major gynecological organizations confirm that a standard tubal ligation does not alter hormone levels.
Why hormones stay stable
Because the blood supply to the ovaries travels via separate pathways from the fallopian tubes, interrupting or removing portions of the tubes does not compromise ovarian blood flow. Consequently, the ovaries continue to synthesize and secrete sex hormones at pre-surgery levels until natural menopause occurs.
Understanding "tubal Ligation Syndrome"
In the late 20th century, some patients reported heavier periods, pelvic pain, or irregular cycles after having their tubes tied, leading to the hypothesis of a distinct medical syndrome. Subsequent controlled studies demonstrated that these symptoms were generally attributable to one of two factors:
The Cessation of Hormonal Contraception: Many individuals transitioned from hormonal contraceptives (such as oral birth control pills, which regulate or lighten periods) straight to tubal ligation. Upon stopping the pill, their periods returned to their natural, pre-pill baseline, which might be heavier or more irregular than what they experienced while on hormonal suppression.
Age-Related Changes: As individuals age into their late thirties and forties, natural hormonal fluctuations preceding perimenopause often alter menstrual flow and cycle length independently of any prior sterilization surgery.
3. Surgical realities: Risks and recovery
While tubal ligation does not damage long-term endocrine health, it remains a surgical procedure carrying standard medical and procedural risks. Understanding these realities helps patients make informed decisions.
Immediate Post-Operative Effects: Most tubal ligations are performed laparoscopically under general anesthesia. Common temporary side effects include mild to moderate abdominal soreness, fatigue, shoulder pain (resulting from the carbon dioxide gas used to inflate the abdomen during laparoscopy), and minor incision site discomfort.
Surgical Risks: As with any pelvic surgery, rare risks include infection, bleeding, adverse reactions to anesthesia, or accidental injury to surrounding organs such as the bowel or bladder.
Ectopic Pregnancy Considerations: While tubal ligation is an exceptionally effective form of permanent birth control (with a failure rate of less than 1%), if a pregnancy does occur post-procedure, there is a significantly higher statistical likelihood that it is ectopic (implanting outside the uterus), which requires immediate medical attention.
To explore further aspects of permanent contraception:
Navigating the Long-Term Hormonal and physical reality
While the immediate physical recovery from a tubal ligation is typically straightforward, the conversation surrounding its long-term physiological impact often stirs intense debate. Chief among these discussions is the concept of Post-Tubal Ligation Syndrome (PTLS).
For decades, patients have reported a constellation of symptoms occurring months or years after their sterilization procedure. These include:
Irregular or markedly heavier menstrual cycles
Intensified premenstrual syndrome (PMS) symptoms, such as severe mood swings and bloating
Pelvic discomfort or deep dyspareunia (pain during intercourse)
Systemic complaints like chronic fatigue, sleep disturbances, and unexplained weight fluctuations
However, the medical mainstream maintains a complex stance on PTLS. Major obstetrics and gynecology bodies emphasize that standard tubal ligation techniques, whether clipping, banding, or cutting, do not disrupt the primary blood supply or neuroendocrine messaging to the ovaries. Because the ovaries retain their vascular network, they continue to produce estrogen and progesterone at normal biological rates until natural menopause occurs.
From an empirical standpoint, large-scale epidemiological studies have historically struggled to find a definitive, statistically significant causal link between tubal sterilization and systemic hormonal failure. Experts often attribute post-procedure menstrual shifts to other variables, such as the natural aging process, the discontinuation of hormonal contraceptives (which previously masked irregular cycles or heavy bleeding), or the normal progression of perimenopause.
Yet, dismissing these patient experiences entirely can leave many women feeling unheard. Some clinical specialists theorize that even if ovarian hormone production remains intact, localized surgical trauma, scar tissue (adhesions), or subtle alterations in local uterine blood flow can impact endometrial health and pelvic sensitivity. Recognizing that biological individuality means not every body reacts uniformly to surgery is a critical component of modern, patient-centered gynecological care.
Psychological Well-Being and the weight of permanence
Beyond physical symptoms, evaluating whether getting your tubes tied is "bad for your body" must encompass mental and emotional well-being. For millions of women, permanent sterilization brings an immense sense of psychological relief. Freeing oneself from the anxieties of unwanted pregnancy or the side effects of long-term synthetic hormones can dramatically improve sexual satisfaction and overall quality of life.
Conversely, psychological distress can arise when a permanent choice collides with shifting life circumstances. Regret is one of the most thoroughly documented long-term outcomes of tubal ligation. Statistical analyses show that regret is most frequently observed in women who underwent the procedure at a younger age (typically under 30), those who faced external pressure from partners or medical providers, or those who experienced unexpected life changes, such as the loss of a child or a separation.
Reversing a tubal ligation is technically possible via microsurgery, but it is an intricate, expensive procedure with variable success rates. Alternatively, individuals seeking pregnancy post-sterilization often have to rely on In Vitro Fertilization (IVF). Therefore, the psychological health impact is deeply tied to thorough pre-operative counseling, ensuring the decision is entirely autonomous, self-directed, and made with a clear view of the future.
Weighing the protective benefits
A comprehensive look at tubal ligation would be incomplete without highlighting its documented medical benefits. Beyond serving as a highly effective, maintenance-free form of permanent birth control, clinical data reveals a compelling secondary advantage: a reduced risk of epithelial ovarian cancer.
Pathological evidence increasingly suggests that a significant portion of high-grade serous ovarian cancers actually originate in the fallopian tubes rather than the ovaries themselves. By removing, blocking, or sealing the tubes, the procedure creates a barrier that may significantly lower the lifetime incidence of these aggressive malignancies. For individuals with a family history of specific genetic markers (such as BRCA mutations), risk-reducing salpingectomy (the complete removal of the fallopian tubes) is frequently recommended as a powerful preventative strategy.
Making an empowered decision
Is getting your tubes tied bad for your body? For the vast majority of individuals, the answer is no. Physiologically, it is a safe, highly efficient, and permanent method of contraception that leaves core endocrine function intact.
However, "safe" does not mean entirely devoid of surgical risk or individual variation. Rare complications like chronic pelvic pain, scar tissue formation, surgical misadventures, or the complex, debated realities of post-procedure changes mean that no medical intervention is entirely neutral.
Deciding to undergo a tubal ligation requires a balanced appraisal of your anatomical health, lifestyle goals, reproductive future, and mental well-being. An open, unhurried dialogue with a trusted healthcare provider remains the cornerstone of navigating these choices safely, ensuring that your path forward is defined entirely by informed consent and bodily autonomy.