However, human biology during the transitional years of perimenopause does not adhere to rigid boundaries, and surgical interventions, while remarkably effective, are not entirely infallible over decades. To understand whether pregnancy is possible under this specific dual condition, one must unpack the endocrinology of perimenopause, the mechanics and longevity of tubal sterilization, and the statistical realities that bridge the two.
1. Demystifying perimenopause: The biology of transition
Perimenopause is not a sudden cliff, but rather a prolonged, undulating bridge between reproductive capability and complete ovarian senescence (menopause). During this phase, the ovaries begin to run out of viable follicles, leading to erratic fluctuations in the primary reproductive hormones: estrogen and progesterone.
Unlike the steady hormonal cadence of a person's 20s and 30s, the perimenopausal hormonal environment is characterized by chaos:
Surging Follicle-Stimulating Hormone (FSH): As the ovaries become less responsive, the pituitary gland pumps out higher levels of FSH in an attempt to stimulate follicular growth.
Unpredictable Estrogen Peaks and Valleys: Estrogen levels do not merely decline in a straight line; instead, they can spike dramatically one month and plummet the next.
Sporadic Ovulation: Because estrogen spikes can still trigger the luteinizing hormone (LH) surge, the ovaries can spontaneously release an egg, even if months have passed without a menstrual period.
This erratic ovulation is the crux of why pregnancy remains biologically possible during perimenopause. Many individuals mistakenly believe that irregular periods mean they are completely sterile. In reality, an irregular cycle simply indicates that ovulation is unpredictable. Until a person has gone a full consecutive 12 months without a natural menstrual cycle, the clinical definition of reaching menopause, ovulation can occur spontaneously and without warning.
2. The permanence and limitations of Tubal Ligation
Tubal ligation, or tubal sterilization, involves cutting, tying, sealing, or blocking the fallopian tubes to prevent sperm from reaching an egg. Medical procedures vary, ranging from postpartum partial salpingectomies to laparoscopic bipolar cautery, silicone bands (Yoon rings), or spring-like inserts (though the latter have largely been phased out).
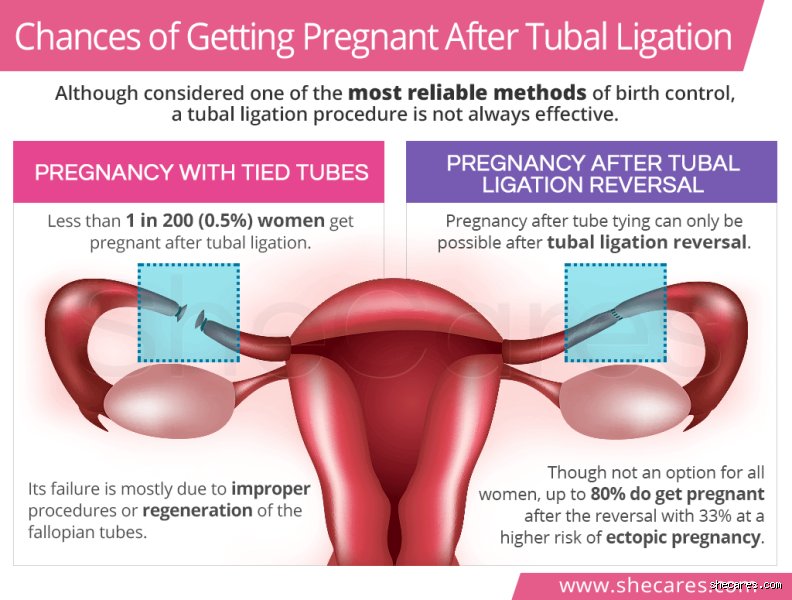
Statistically, tubal ligation is one of the most effective forms of birth control available, boasting a typical-use failure rate of less than 1% in the first year. Over a lifetime, however, cumulative probabilities change. Clinical data from landmark studies, such as the Collaborative Review of Sterilization (CREST) study conducted by the Centers for Disease Control and Prevention (CDC), indicate cumulative failure rates over 10 years:
Bipolar coagulation: Approximately 24.8 failures per 1,000 procedures over 10 years.
Postpartum salpingectomy: Approximately 7.5 failures per 1,000 procedures over 10 years.
Spring-like inserts (Essure): Showed varying long-term efficacy profiles before being discontinued.
The primary mechanisms behind tubal sterilization failure include:
Recanalization: The body possesses a remarkable healing capacity. Over years or even decades, the severed ends of the fallopian tubes can occasionally heal, form a fistula (a new microscopic channel), or reconnect, inadvertently restoring a pathway for gametes.
Luteal Phase Conception at the Time of Surgery: On rare occasions, a patient may already be pregnant at the very moment the surgery is performed if conception occurred late in the preceding cycle and was undetectable by standard pre-op testing.
Misidentification or Incomplete Occlusion: Though rare with experienced surgeons, anatomical anomalies can occasionally prevent complete closure of the lumen.
3. The overlap: Perimenopause meets Sterilization
When considering the combination of perimenopause and a prior tubal ligation, the statistical risk of pregnancy drops significantly compared to someone relying solely on barrier methods during perimenopause. A sterilized fallopian tube provides a formidable mechanical barrier against sperm migration.
Nevertheless, the word "impossible" is rarely used in reproductive medicine. While the likelihood of spontaneous pregnancy after tubal ligation during perimenopause is exceedingly low, it is not mathematically zero. The convergence of two factors creates unique clinical scenarios:
The Persistence of Ovarian Function: As long as the ovaries produce eggs and hormonal surges occur, the raw material for fertilization exists.
The Integrity of the Barrier: If micro-channels have formed via recanalization over the 10, 15, or 20 years since the sterilization procedure was performed, sperm encountering a spontaneously released perimenopausal egg could theoretically achieve fertilization.
It is vital to distinguish between intrauterine pregnancy and ectopic pregnancy. Following tubal ligation, if a failure does occur, the risk of an ectopic pregnancy, where the fertilized egg implants outside the uterine cavity, most commonly within the scarred fallopian tube, is proportionally higher. Ectopic pregnancies represent a medical emergency requiring prompt evaluation.
Navigating the intersection of perimenopause and Tubal Ligation
As a woman transitions through the natural hormonal shifts of midlife, understanding the mechanics of birth control becomes uniquely complex. While a tubal ligation, commonly known as having one's "tubes tied", is widely recognized as a permanent method of sterilization, it is not an absolute guarantee against pregnancy. Coupled with the unpredictable hormonal fluctuations of perimenopause, navigating reproductive health during this phase requires clarity, awareness, and medical insight.
The realities of Tubal Ligation Integrity over Time
A tubal ligation works by blocking, cutting, or sealing the fallopian tubes, which effectively prevents sperm from reaching and fertilizing an egg. Statistically, this procedure is more than 99% effective. However, biological anomalies do occur. In rare instances, the fallopian tubes can naturally recanalize, meaning the severed ends find a way to heal and reconnect over time. Alternatively, if the original surgical seal was incomplete, a microscopic passage may remain.
When a structural failure happens, natural conception remains physically possible, even if highly improbable. This baseline risk does not drop to zero simply because a woman enters her late thirties or forties. Instead, the physiological landscape shifts as the ovaries begin their transition toward the end of their active reproductive cycle.
Perimenopausal hormones and masked symptoms
Perimenopause introduces a high degree of unpredictability into a woman’s monthly cycle. Estrogen and progesterone levels surge and plummet erratically, leading to irregular periods, missed menses, night sweats, and mood changes.
This hormonal turbulence creates a diagnostic challenge for women with tied tubes. A missed or late period is typically the primary indicator of pregnancy. Yet, during perimenopause, irregular periods are so common that a missed cycle is easily attributed to "the change of life" rather than a possible conception. Consequently, early pregnancy signs, such as mild fatigue, breast tenderness, nausea, or bloating, can easily be misinterpreted as standard perimenopausal symptoms. Women relying solely on their age or previous sterilization may overlook these bodily signals, delaying recognition of an unexpected pregnancy.
Understanding the risks: Ectopic pregnancy
If a pregnancy does occur after a tubal ligation, the statistical likelihood of it being an ectopic pregnancy increases significantly. An ectopic pregnancy happens when a fertilized egg implants outside the main cavity of the uterus, most frequently inside a damaged or partially blocked fallopian tube.
Because the fallopian tubes are compromised by the initial sterilization procedure, an embryo can easily become trapped. An ectopic pregnancy cannot proceed normally and poses a severe medical emergency. Symptoms that warrant immediate medical evaluation include:
Sharp, persistent, or one-sided pelvic and abdominal pain
Abnormal vaginal bleeding or spotting
Dizziness, fainting, or shoulder tip pain
Healthcare professionals emphasize that any woman experiencing unusual pelvic discomfort alongside late or irregular bleeding during perimenopause should seek prompt clinical evaluation to rule out complications.
Medical evaluation and diagnostic vigilance
Because bodily changes during this life stage can be ambiguous, consulting a gynecologist or healthcare provider is essential for any persistent or unusual symptoms. Simple diagnostic tools, such as standard urine or blood hormone tests (checking human chorionic gonadotropin levels), can quickly clarify whether symptoms stem from a changing hormonal profile or an unexpected gestation.
Medical guidance also reminds individuals that while overall natural fertility declines sharply as women age into their late forties, erratic perimenopausal ovulation can occasionally produce viable eggs. As long as intermittent ovulation occurs and a structural pathway exists via a compromised tubal ligation, biological surprises, though rare, remain within the realm of possibility.
Empowering your midlife health journey
Maintaining open communication with a healthcare professional ensures that any physical shifts during midlife are properly understood and addressed. Whether dealing with irregular cycles, managing perimenopausal symptoms, or clarifying long-term contraceptive security, staying informed remains a vital part of personal well-being. Regular check-ups help demystify the physiological changes of this transition, offering peace of mind and safeguarding overall health.
Can You Get Pregnant After Tubal Ligation?
This video provides an overview of how tubal ligation works and the biological factors surrounding rare instances of pregnancy post-procedure.