To answer this question thoroughly, we must examine the anatomical structures involved, the biological mechanisms behind spontaneous recanalization, the subtle or prominent signs that may indicate a reversal of the procedure, and the definitive diagnostic methods used by medical professionals to confirm tubal patency.
1. The anatomical landscape: Fallopian tubes and ligation methods
To understand how fallopian tubes might reconnect, one must first appreciate their normal structure and function. The fallopian tubes are two thin, muscular tubes lined with delicate, hair-like cilia. They serve as the vital highway connecting the ovaries to the uterus. Each month, during ovulation, an egg is released from an ovary and travels down the fallopian tube, where fertilization by sperm typically takes place before the fertilized embryo implants into the uterine lining.
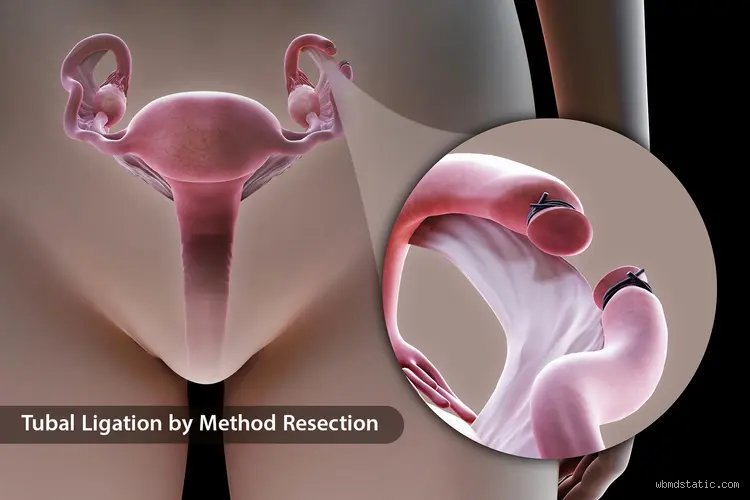
Tubal ligation interrupts this pathway. Depending on the specific surgical technique utilized during the original operation, the physical disruption takes different forms:
Surgical Clips and Rings: Devices such as Filshie clips or Falope rings are placed externally over a segment of the tube, compressing the tissue to block the passage of eggs and sperm while causing localized necrosis (tissue death) that seals the segment.
Partial Salpingectomy (Pomeroy Technique): A loop of the fallopian tube is tied off with a suture and a portion of the loop is excised and removed, leaving two separate, cauterized, or tied ends.
Electrocoagulation (Bipolar or Monopolar): Electrical current is applied to burn and destroy a section of the fallopian tube tissue, creating scar tissue that permanently obstructs the lumen.
Tubal Implants (Essure - historical): Micro-inserts placed via hysteroscopy into the tubal ostia, stimulating scar tissue growth over time to block the tubes (though largely phased out or recalled in many regions).
Despite these robust physical and thermal barriers, the body's innate wound-healing cascade occasionally initiates processes that defy the intended permanence of the surgery.
2. Defining spontaneous Tubal recanalization
When people ask whether their tubes have "grown back together," they are referring scientifically to spontaneous tubal recanalization. This rare physiological phenomenon occurs when the severed, clipped, or cauterized ends of the fallopian tubes manage to heal, form a new channel (fistula or lumen), and re-establish a continuous passage between the ovaries and the uterus.
Recanalization does not happen overnight. It is usually the result of gradual tissue remodeling, inflammation resolution, and cellular migration. The body's immune and vascular systems constantly work to repair damaged tissue. If a clip slips, migrates, or erodes slightly, or if the scar tissue barrier is incomplete or bridges over time, microscopic channels can form. Once a microscopic pathway opens up, fluid, sperm, and eventually an ovum may successfully traverse the previously blocked segment.
3. Early warning signs and clinical indicators
Recognizing that tubal patency has returned is rarely straightforward, as there is no universal physical sensation associated with the tubes reconnecting. Instead, detection usually hinges on secondary biological events or incidental findings.
Unintended Pregnancy
The most common and definitive indicator that fallopian tubes have re-established patency is an unintended pregnancy. Because tubal ligation prevents sperm and egg from meeting, the sudden restoration of tubal continuity removes that mechanical barrier. If recanalization occurs, pregnancies can sometimes be ectopic (implanting outside the uterus, most commonly within the fallopian tube itself). Ectopic pregnancies constitute a severe medical emergency characterized by sharp pelvic pain, abnormal vaginal bleeding, and dizziness, requiring immediate medical evaluation.
Changes in menstrual cycles or pelvic sensations
Some patients report noticing subtle shifts in their pelvic awareness or menstrual cycles, though these are rarely specific enough on their own to confirm recanalization. Hormonal fluctuations remain governed primarily by the ovaries, which continue to function normally after a tubal ligation since blood supply and endocrine function are preserved. Therefore, standard menstrual cycles typically persist unchanged after sterilization. Any drastic changes in pelvic pain, unusual cramping, or atypical spotting warrant professional investigation to rule out other gynecological conditions, such as ovarian cysts, endometriosis, or indeed, tubal recanalization.
Diagnostic verification and advanced medical evaluation
When physiological signs or unexpected fertility changes suggest that fallopian tubes may have spontaneously recanalized (grown back together) after a tubal ligation, physical symptoms alone cannot provide a definitive diagnosis. Because spontaneous recanalization, also known as a sterilization failure, carries unique medical implications, proper diagnostic verification is essential.
Healthcare providers rely on a series of progressive clinical evaluations to confirm whether tubal continuity has truly been re-established.
1. Pregnancy testing and quantitative hCG tracking
The most common catalyst for investigating tubal recanalization is an unexpected positive pregnancy test. If a patient believes their permanent birth control is completely protective, a missed period or early pregnancy symptoms prompt immediate clinical testing.
Serum hCG Blood Tests: Unlike qualitative urine strips, quantitative beta-hCG blood tests measure the exact concentration of human chorionic gonadotropin in the bloodstream. Tracking these values over a 48-to-72-hour window helps medical professionals determine whether a pregnancy is progressing normally.
Evaluating Doubling Times: In a healthy intrauterine pregnancy, hCG levels typically double approximately every 48 to 72 hours. Abnormal doubling patterns or sluggish rises often serve as an initial warning sign of potential complications.
2. Transvaginal ultrasound imaging
Once pregnancy is detected or an anatomical evaluation is required, a transvaginal ultrasound is the primary imaging tool utilized by gynecologists.
Locating the Gestational Sac: The primary objective in the context of potential recanalization is confirming whether the fertilized egg has implanted safely inside the uterine cavity.
Screening for Ectopic Pregnancy: Because healed or partially reconnected fallopian tubes often feature narrowed lumens, scar tissue, or structural irregularities, fertilized eggs can become trapped. An ectopic pregnancy (most commonly occurring within the fallopian tube) is a critical medical emergency. Early ultrasound imaging aims to rule out ectopic implantation before it leads to rupture or internal hemorrhage.
3. Hysterosalpingography (HSG) and specialized imaging
If a patient is not currently pregnant but is undergoing an investigation into why fertility has unexpectedly returned, or to evaluate structural patency, specialized radiology procedures may be performed.
Hysterosalpingogram (HSG): This fluoroscopic procedure involves introducing a water-soluble or oil-based contrast dye through the cervix into the uterine cavity.
Fluoroscopic Visualization: As the radiologist monitors the contrast via real-time X-ray imaging, they can observe whether the dye flows freely through the uterine cornua and spills out through the ends of the fallopian tubes, confirming whether one or both tubes are open.
Clinical implications and management strategies
Discovering that fallopian tubes have grown back together changes a patient's reproductive health profile significantly. Because a spontaneous recanalization represents a failure of a permanent sterilization method, proactive management and