However, life is dynamic, circumstances change, and bodies possess a complex, sometimes unpredictable capacity for healing and cellular regeneration. Whether driven by a shifting desire for family expansion, new relationship dynamics, symptoms of post-tubal ligation syndrome, or simply a deep-seated need for absolute medical certainty, the question of how to verify the current status of a previous sterilization procedure is more common than many realize.
Determining whether your fallopian tubes remain successfully occluded, blocked, or severed is not a matter of guesswork, physical sensation, or at-home observation; rather, it requires a sophisticated intersection of gynecological history, advanced medical imaging, and professional clinical evaluation.
Navigating the landscape of reproductive anatomy and surgical verification can feel overwhelming, particularly when dealing with medical terminology, imaging options, and the emotional weight often attached to reproductive health decisions. This comprehensive guide explores the physiological reality of tubal ligations, the biological phenomena behind rare procedural failures or recanalization, the specific clinical diagnostic tools used to assess tubal patency, and what steps you can take if your medical reality does not match your current life goals.
Understanding Tubal Ligation: Anatomy and methods
To understand how a tubal ligation can be checked, one must first understand what actually happens to the reproductive anatomy during the initial surgical procedure. The fallopian tubes are a pair of muscular, epithelium-lined conduits stretching from the superior corners of the uterus out toward the ovaries. Their primary biological function is to act as the transit highway for an oocyte (egg) released during ovulation, providing the critical site where fertilization by a sperm cell typically takes place before the resulting embryo travels down into the uterine cavity for implantation.
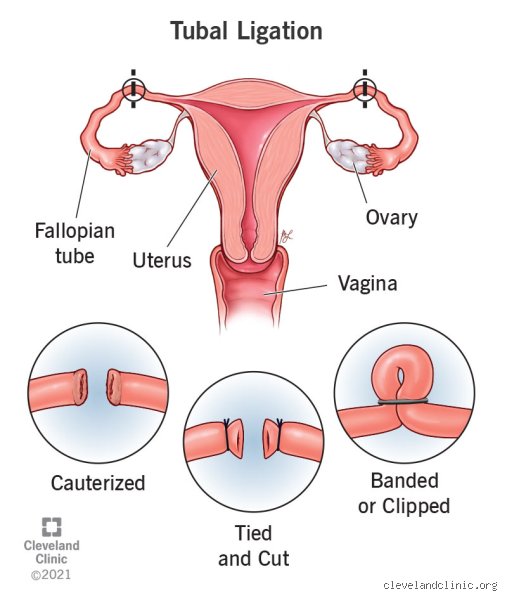
A tubal ligation is designed to mechanically or thermally interrupt this highway, creating an impassable barrier that prevents sperm from reaching the egg, or prevents the egg from reaching the uterus, thereby preventing fertilization. Over the decades, medical science has developed several distinct surgical techniques to achieve this permanent occlusion:
Bilateral Tubal Ligation (BTL) via Suture and Resection (Pomeroy Technique): Historically the most common method, a loop of the fallopian tube is lifted, tied off with a suture, and a small segment of the tube is surgically cut and removed. As the tissue heals, the two separated ends pull apart and seal over with scar tissue.
Electrocautery (Bipolar or Monopolar): Electrical current is applied to destroy a specific segment of the fallopian tube tissue, sealing the lumen closed and frequently destroying a small section of the tube to ensure permanent separation.
Mechanical Rings and Clips (Falope rings, Filshie clips): Specialized plastic or titanium medical devices are clamped tightly across the fallopian tube, crushing the tissue and blocking the lumen without necessarily cutting it immediately, though necrosis eventually seals the tube shut beneath the device.
Hysteroscopic Sterilization (e.g., Essure): Though largely phased out or withdrawn from many global markets due to complications, this method involved placing small metallic micro-inserts into the openings of the fallopian tubes from inside the uterus, prompting scar tissue to grow around the coils over a three-month period.
Salpingectomy: Increasingly performed not just for sterilization but for ovarian cancer risk reduction, total or partial salpingectomy involves the complete surgical removal of the fallopian tubes. When the tubes are entirely removed, the possibility of natural recanalization is reduced to absolute zero.
Because each of these techniques alters the anatomy differently, the method of your original surgery matters a lot in determining how a doctor will approach verifying your current tubal status.
Why patients seek verification
The motivation to check whether fallopian tubes are still tied or blocked generally falls into two distinct categories: clinical necessity and personal life transition.
From a clinical standpoint, although tubal ligation has a cumulative failure rate of roughly 1 in 200 over a ten-year period, failures do occasionally happen. If a patient who has undergone a tubal ligation experiences unusual pelvic pain, missed menstrual cycles, abnormal uterine bleeding, or symptoms that mimic early pregnancy, such as breast tenderness, nausea, or fatigue, investigating the structural integrity of the tubes becomes critical.
Of particular medical importance is the risk of ectopic pregnancy. If a tubal ligation fails and an egg is successfully fertilized, the anatomical distortion or scarring within the tube often prevents the embryo from reaching the uterus, leading it to implant dangerously within the narrow confines of the fallopian tube itself. An ectopic pregnancy is a life-threatening medical emergency requiring immediate intervention. Therefore, ruling out or confirming tubal patency in the presence of pregnancy symptoms is paramount.
Conversely, personal life transitions drive a massive volume of inquiries regarding tubal status. Individuals who underwent sterilization under financial stress, young age, medical pressure, or relationship circumstances that have since changed often experience profound changes of heart. When contemplating family expansion later in life, patients must determine whether their tubes can support a surgical reversal (tubal anastomosis) or if they must bypass the tubes entirely through assisted reproductive technologies like In Vitro Fertilization (IVF). In both scenarios, knowing the precise anatomical state of the remaining tubal segments dictates the roadmap for future reproductive choices.
The myth of Self-Assessment: Why external signs fall short
A frequent point of confusion among patients is whether there are physical signs, changes in menstruation, or bodily sensations that can indicate whether a tubal ligation remains effective. It is critical to establish a foundational medical truth early: There is no physical symptom, sensation, or hormonal fluctuation that can reliably confirm whether your tubes are still tied.
Many individuals mistakenly believe that the presence or absence of regular menstrual cycles indicates tubal status. However, tubal ligation does not affect the ovaries or the endocrine system. Your ovaries continue to produce estrogen and progesterone, and you will continue to experience regular ovulatory cycles and menstruation (unless you are concurrently using a hormonal contraceptive or reaching perimenopause) regardless of whether your fallopian tubes are open, clipped, tied, or completely removed.
Similarly, changes in libido, weight fluctuations, mood shifts, or pelvic aches are entirely unrelated to the mechanical patency of the fallopian tubes. Relying on physical feelings to gauge sterilization status is medically unsafe. The only way to definitively know if your tubes are still occluded is through direct visualization or specialized diagnostic imaging performed by a qualified healthcare professional.
Diagnostic evaluation methods: Verifying Tubal Ligation status
When an individual seeks definitive confirmation of whether a prior tubal ligation procedure remains intact and effective, clinical evaluation goes far beyond simple physical examinations or patient history. Because anatomical structures inside the pelvic cavity cannot be visualized from the exterior, specialized radiological and surgical procedures are required to directly assess the patency or closure of the fallopian tubes.
1. Hysterosalpingography (HSG)
One of the primary and most commonly utilized diagnostic tools for evaluating fallopian tube status is the Hysterosalpingogram (HSG). This specialized fluoroscopic X-ray procedure examines the shape of the uterine cavity and the condition of the fallopian tubes.
The Procedure: A radiopaque contrast medium is introduced into the uterine cavity via a thin catheter placed through the cervix. As the fluid fills the uterus, real-time X-ray imaging (fluoroscopy) tracks its flow.
Interpretation: If the tubes are successfully blocked, clipped, or tied off without recanalization, the contrast dye will fill the uterine cavity but will fail to spill out into the peritoneal cavity through the ends of the tubes. Conversely, if the contrast liquid spills freely into the pelvic cavity, it indicates that at least one fallopian tube is open or has recanalized.
2. Pelvic ultrasound (transvaginal and Hysterosalpingo-Contrast Sonography)
While standard pelvic ultrasound offers excellent visualization of the ovaries and the general contour of the uterus, visualizing the exact closure mechanism of normal-caliber fallopian tubes can be challenging. However, advanced ultrasound modalities provide non-invasive alternatives:
Hysterosalpingo-Contrast Sonography (HyCoSy): This method uses a sterile saline and air mixture or specialized ultrasound contrast agents rather than X-ray radiation and iodine dye. Ultrasound technicians monitor how the fluid traverses the uterine cornua and whether it passes through the fallopian tubes.
Surgical Clips and Rings: In cases where metal clips (such as Filshie clips) or Silastic bands were used during the initial sterilization procedure, high-resolution transvaginal ultrasound can sometimes identify the radiopaque or hyperechoic foreign bodies in the expected anatomical locations near the isthmus of the tubes.
3. Diagnostic Laparoscopy
Considered the gold standard for absolute definitive confirmation, diagnostic laparoscopy is a minor surgical procedure that allows direct visualization of the reproductive organs.
Direct Visualization: A surgeon inserts a small laparoscope (a fiber-optic camera) through a tiny incision near the navel. This provides high-definition, direct optical verification of whether the fallopian tubes have been sectioned, tied, cauterized, or fitted with permanent mechanical occlusion devices.
Chromotubation: During laparoscopy, a harmless blue dye (such as methylene blue) can be injected through the cervix and uterus. Surgeons directly watch the fimbriated ends of the tubes to see if any dye emerges, providing immediate, unmistakable proof of tubal patency or complete blockage.
Clinical implications and understanding recanalization
While tubal ligation is designed to be a permanent form of female sterilization, medical literature notes that rare instances of spontaneous recanalization, where the severed or blocked ends of the fallopian tubes heal and re-establish a microscopic channel, can occur. The probability of recanalization depends heavily on the specific surgical technique originally employed:
Electrocoagulation (Cautery): Extensive thermal destruction of a larger segment of the tube typically carries the lowest failure and recanalization rates.
Postpartum Partial Salpingectomy (e.g., Pomeroy technique): Highly effective, though incomplete tissue destruction can occasionally lead to atypical healing.
Clips and Rings: Mechanical closure devices carry a slightly higher long-term cumulative failure rate compared to extensive cautery or total salpingectomy, as the tissue beneath clips can occasionally atrophy or slip.
Patients seeking definitive answers regarding their reproductive anatomy should consult with a qualified gynecologist or reproductive endocrinologist to discuss which diagnostic imaging or surgical modality is safest and most appropriate for their individual health history.