Understanding where aneurysms most commonly develop requires an exploration of human vascular anatomy, fluid dynamics, and regional histopathology. Clinically, aneurysms are broadly divided into two major anatomical realms: aortic (systemic) aneurysms and intracranial (cerebral) aneurysms, with additional peripheral presentations occurring in localized vascular beds. This first part of our comprehensive expert analysis examines the primary anatomical zones where aneurysms originate, focusing intensely on the aorta and the foundational mechanisms driving site-specific vulnerability.
1. The Aorta: The preeminent Site for systemic Aneurysms
By far the most common and clinically significant systemic site for aneurysm formation is the aorta, the body’s largest artery. Originating at the left ventricle of the heart, the aorta carries oxygenated blood through the chest and abdomen, enduring immense hemodynamic loads with every cardiac cycle. Because of its sheer size and the magnitude of blood pressure it handles, the aorta accounts for the vast majority of major arterial aneurysms.
However, aneurysms do not form uniformly across the length of the aorta. They exhibit a distinct predilection for two primary zones: the abdominal segment and, less frequently, the thoracic segment.
A. The Abdominal Aorta (Abdominal Aortic Aneurysms - AAAs)
The single most common location for a major arterial aneurysm in the human body is the infrarenal segment of the abdominal aorta.
Anatomical Definition: The abdominal aorta is the section of the vessel passing through the abdominal cavity, spanning from the diaphragm down to its bifurcation into the common iliac arteries. The infrarenal region refers specifically to the portion of the abdominal aorta located below the branching of the renal (kidney) arteries.
Why This Site is Vulnerable:
Histological Composition: Unlike the thoracic aorta, which is rich in elastic lamellar units designed to absorb high-frequency pulse waves, the infrarenal abdominal aorta possesses a significantly lower density of elastin and a higher proportion of stiffer collagen and smooth muscle cells. This makes it intrinsically less resilient to chronic cyclic fatigue.
Hemodynamic Wave Reflection: Pulse wave reflections from the lower extremities converge at the distal abdominal aorta, magnifying local systolic pressure spikes.
Atherosclerotic Predilection: The abdominal aorta is a frequent site for advanced atherosclerotic plaque accumulation. Chronic inflammation driven by plaque buildup degrades the media layer, destroying vascular smooth muscle cells and breaking down extracellular matrix proteins such as elastin.
Statistically, abdominal aortic aneurysms disproportionately affect older adults, particularly males over the age of sixty who have a history of tobacco use. When the wall at this specific infrarenal junction weakens, it progressively dilates, turning what should be a smooth, uniform conduit into a high-risk pulsatile mass.
B. The Thoracic Aorta (Thoracic Aortic Aneurysms - TAAs)
While less common than abdominal aortic aneurysms, the thoracic aorta—encompassing the aortic root, the ascending aorta, the aortic arch, and the descending thoracic aorta—represents another vital site for aneurysm development.
Ascending Aorta and Aortic Root: Aneurysms here are frequently driven by degenerative processes known collectively as cystic medial degeneration, where smooth muscle cells undergo apoptosis and elastic fibers become fragmented. Genetic connective tissue disorders, such as Marfan syndrome, Loeys-Dietz syndrome, and bicuspid aortic valves, heavily predispose individuals to aneurysms in the ascending aorta due to inherent structural flaws in extracellular matrix proteins.
Descending Thoracic Aorta: Aneurysms in this region are more commonly linked to chronic hypertension and advanced atherosclerosis, mirroring the degenerative mechanisms seen lower down in the abdominal aorta.
2. Hemodynamic stress and arterial geometry
To fully appreciate why aneurysms localize to specific anatomical junctions, one must examine the interaction between wall shear stress (WSS) and arterial geometry.
Arteries are not straight, uniform pipes; they branch, curve, and taper. Every bifurcation and curve introduces complex fluid dynamics:
Flow Separation and Oscillation: At arterial branch points, blood flow splits, creating zones of low or oscillatory wall shear stress alongside areas of high impact. These alterations disrupt endothelial cell function, triggering inflammatory pathways that weaken the underlying media.
Matrix Metalloproteinase (MMP) Activation: Hemodynamic turbulence stimulates local cells to release enzymes (such as MMP-2 and MMP-9) that actively digest collagen and elastin. Once this structural scaffolding is compromised, the continuous outward pressure of blood forces the wall to expand outward, initiating the aneurysmal cycle.
In the upcoming second part of this analysis, we will explore intracranial (brain) aneurysms, specifically focusing on the Circle of Willis, branching mechanics, and peripheral vascular beds, to complete our mapping of where aneurysms most commonly develop.
The anatomy of vulnerability: High-Risk arterial zones
To understand where aneurysms most commonly develop, one must first recognize the underlying hemodynamic principles governing arterial wall stress. Arteries are engineered to withstand continuous pulsatile pressure, possessing resilient muscular and elastic walls. However, regions subjected to extreme mechanical force, sharp hemodynamic transitions, or structural congenital vulnerabilities become prime candidates for wall degradation.
Statistically and clinically, aneurysms cluster predominantly in two major anatomical domains: the aorta (the body's main arterial trunk) and the cerebral vasculature (the intricate network of vessels supplying the brain).
1. The Aorta: The Primary Site for systemic Aneurysms
The aorta experiences the highest volume and pressure of blood output directly from the left ventricle of the heart. Consequently, aortic aneurysms represent the most common and structurally devastating vascular dilations outside of the central nervous system. Within the aorta, vulnerability is sharply concentrated into two distinct zones:
The Abdominal Aorta (Abdominal Aortic aneurysm - AAA)
By far the most common location for a major systemic aneurysm is the abdominal aorta, specifically the segment running through the lower abdomen below the renal arteries.
Hemodynamic Factors: As the aorta descends from the chest into the abdominal cavity, it tapers in diameter, and the surrounding structural support from the chest wall diminishes. The transition point experiences high pulse-wave reflections and turbulent flow profiles.
Demographic Predilection: AAAs predominantly affect older adults, particularly males over the age of 60 with a history of tobacco use, atherosclerosis, and hypertension. Because the abdominal cavity can accommodate considerable expansion before adjacent organs signal distress, AAAs often grow silently until they leak or rupture, triggering catastrophic internal hemorrhage.
The Thoracic Aorta (Thoracic Aortic aneurysm - TAA)
Though less frequent than abdominal variants, aneurysms also form in the upper portion of the aorta traversing the chest cavity (the ascending aorta, aortic arch, and descending thoracic aorta).
Etiology: These are frequently linked to genetic connective tissue disorders (such as Marfan syndrome or Ehlers-Danlos syndrome), bicuspid aortic valves, chronic hypertension, or localized infections. The ascending aorta experiences immense, repetitive biomechanical stretch with every single cardiac contraction, making its elastic media prone to cystic medial degeneration over time.
2. Cerebral vasculature: The hub of intracranial Aneurysms
When looking inside the skull, intracranial or brain aneurysms present a completely different epidemiological and anatomical profile. Up to 90% of cerebral aneurysms are saccular, colloquially known as "berry" aneurysms due to their spherical, sac-like appearance attached to a parent vessel.
Intracranial aneurysms do not develop randomly across the brain's vast capillary network; instead, they display a fierce predilection for specific arterial junctions characterized by high directional shear stress and congenital gaps in the internal elastic lamina.
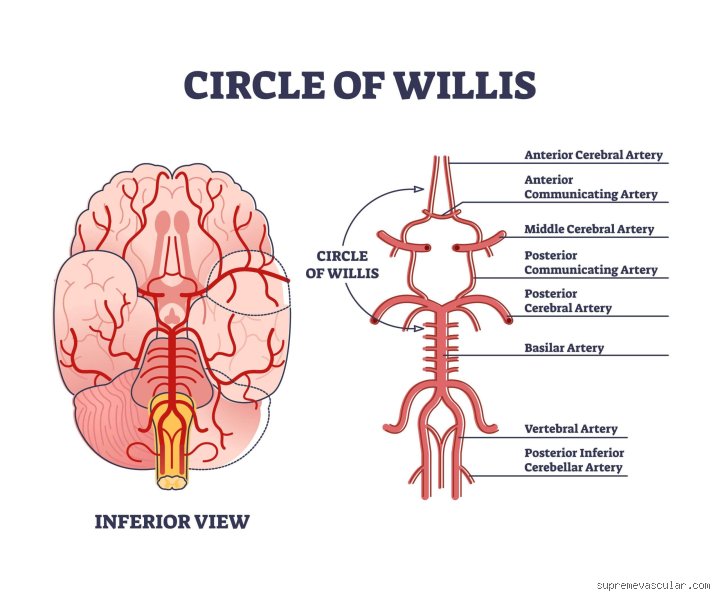
The Circle of Willis
The vast majority of brain aneurysms form within or immediately adjacent to the Circle of Willis, the ring-like vascular anastomosis located at the base of the brain that ensures collateral blood supply. Because this junction redistributes blood flow across multiple branching pathways, it acts as a permanent hydraulic stress-test center.
Within this region, specific hotspot intersections account for the overwhelming majority of clinical presentations:
Anterior Communicating Artery (AComA): Statistically the most common site for a cerebral aneurysm. Situated at the front of the Circle of Willis where the right and left anterior cerebral arteries connect, its sharp directional angles focus intense fluid impact. A rupture here frequently leads to subarachnoid hemorrhage, often accompanied by visual disturbances, acute behavioral shifts, or memory complications.
Middle Cerebral Artery (MCA) Bifurcation: The MCA branches sharply outward toward the lateral cortex. Aneurysms commonly develop directly at the apex where the main trunk splits into primary divisions. Because these vessels overlie motor and sensory cortices, ruptures or mass effects can directly impact speech, facial movement, and limb coordination.
Posterior Communicating Artery (PComA): Located where the internal carotid artery meets the posterior cerebral circulation. PComA aneurysms are notorious for expanding outward and directly compressing the adjacent oculomotor nerve (cranial nerve III), frequently presenting clinical warning signs like double vision, a "blown" (dilated) pupil, or drooping eyelids prior to a full rupture.
Basilar Artery Tip: Situated deep within the posterior fossa where the basilar trunk bifurcates into the posterior cerebral arteries. Though less common, aneurysms here carry high procedural complexity and significant clinical risk due to their proximity to vital brainstem control centers.
3. Peripheral and Visceral arterial sites
While the aorta and the cerebral circulation dominate clinical statistics, aneurysms can occasionally manifest in peripheral or visceral arterial beds. Understanding these secondary sites completes the map of human vascular vulnerability:
Popliteal Artery Aneurysms: Located behind the knee joint, the popliteal artery is the most common site for peripheral (non-aortic, non-cerebral) aneurysms. Unlike aortic variants that threaten life via rupture, popliteal aneurysms frequently threaten limbs by serving as incubators for blood clots (thrombi) that break loose and obstruct blood flow to the lower leg and foot.
Splenic and Visceral Artery Aneurysms: Found within the tortuous branches supplying visceral organs like the spleen, liver, and intestines. Splenic artery aneurysms, for example, show a notable prevalence in women and carry unique risks during physiological stress such as pregnancy.
Summary Matrix of Common locations
| Vascular Region | Specific Common Site | Typical Morphology | Primary Clinical Risk |
|---|---|---|---|
| Abdomen | Abdominal Aorta (infrarenal) | Fusiform / Asymmetric | Massive retroperitoneal hemorrhage / Rupture |
| Chest | Thoracic Aorta (ascending/arch) | Fusiform / Saccular | Aortic dissection, heart failure, rupture |
| Brain | Anterior Communicating Artery (AComA) | Saccular ("Berry") | Subarachnoid hemorrhage (stroke) |
| Brain | Middle Cerebral Artery (MCA) Bifurcation | Saccular ("Berry") | Intracerebral / Subarachnoid hemorrhage |
| Knee | Popliteal Artery | Fusiform | Acute limb ischemia via distal thromboembolism |
Recognizing that aneurysms overwhelmingly target high-pressure hydraulic junctures, such as the infrarenal abdominal aorta and the branching points of the Circle of Willis, underscores why systemic blood pressure control, smoking cessation, and routine vascular screening remain the bedrock of modern preventive cardiology and neurosurgery.