The biological origins of silent cerebrovascular dilatation
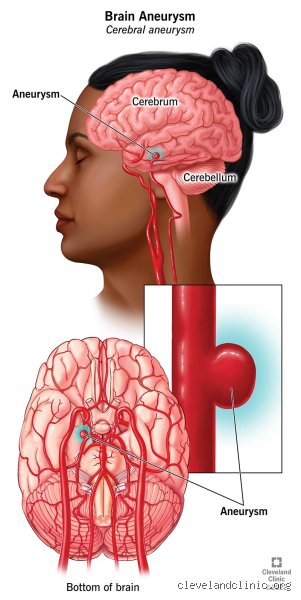
To comprehend how long a brain aneurysm can persist without detection, one must examine how these vascular anomalies form and evolve. Cerebral aneurysms most frequently arise at the bifurcation points of major arteries within the circle of Willis, the anatomical ring of blood vessels situated at the base of the brain. At these junctions, hemodynamic stress—the continuous physical force exerted by flowing blood—places immense pressure on the vessel walls.
Over many years, microscopic structural vulnerabilities within the tunica media, the muscular middle layer of the arterial wall, can cause localized degradation. The internal elastic lamina gradually fragments, allowing the inner endothelial lining to herniate outward under arterial pressure. This process is rarely abrupt; instead, it unfolds slowly over a prolonged period. During the initial developmental phases, the lesion is typically minuscule, often referred to as a micro-aneurysm, measuring only a few millimeters in diameter. At this microscopic or sub-centimeter scale, the aneurysm does not displace adjacent brain tissue, compress cranial nerves, or disrupt normal cerebral blood flow in a manner that triggers neurological deficits. Consequently, the affected individual experiences zero biological feedback indicating that a vascular weakness has formed.
The chronology of asymptomatic persistence
Clinical observation and neurosurgical data demonstrate that a brain aneurysm can remain asymptomatic for an entire human lifespan. Autopsy studies consistently reveal that a significant percentage of the general population, estimates range from approximately two to five percent, harbors unruptured cerebral aneurysms, yet the vast majority of these individuals never experience a rupture or associated symptoms.
When an aneurysm remains small (typically under seven millimeters in diameter), the risk of rupture is statistically low, and the likelihood of mass effect symptoms is practically zero. Because cerebral blood vessels lack somatic pain receptors inside the cranium, the structural stretching of the arterial wall itself does not cause localized physical pain. Unless the aneurysm expands rapidly, begins to leak microscopic amounts of blood (a phenomenon sometimes called a sentinel bleed), or grows large enough to exert direct mechanical pressure on critical neighboring structures, it generates no clinical footprint.
Consequently, a person can easily live with an unruptured brain aneurysm for twenty, thirty, forty, or fifty years without a single diagnostic indicator. Many individuals who eventually discover they have an aneurysm do so entirely by coincidence, an incidental finding during magnetic resonance imaging (MRI) or computed tomography (CT) scans performed for unrelated medical issues, such as chronic headaches, sinus evaluations, or minor head trauma.
Factors influencing silent longevity versus vulnerability
While an aneurysm can endure silently for decades, the duration of its silent phase depends heavily on a complex interplay of genetic, structural, and environmental variables. Not all aneurysms remain stable over time; some undergo progressive enlargement, while others remain static from the moment of formation.
Structural wall composition plays a decisive role. Aneurysms characterized by thick, organized collagen deposition and stable mural cell populations may remain dormant indefinitely. Conversely, lesions subject to ongoing cellular inflammation, continuous matrix degradation by enzymes known as matrix metalloproteinases, and turbulent intra-aneurysmal flow dynamics are more prone to structural fatigue.
Hemodynamic stress further modulates this timeline. Chronic hypertension places continuous, elevated strain on the fragile dome of the aneurysm, accelerating wall thinning and dimensional expansion. Lifestyle factors such as cigarette smoking introduce systemic endothelial dysfunction and systemic inflammation, which can compromise vascular integrity throughout the body, including the cerebral vasculature. Despite these destabilizing forces, the transitional window between a stable, silent aneurysm and a symptomatic or ruptured state can span decades, illustrating the remarkable capacity of cerebral blood vessels to tolerate chronic structural anomalies under specific physiological conditions.
Diagnostic challenges and the elusive nature of silent lesions
The primary reason brain aneurysms persist without detection is the profound absence of early warning signs combined with the limitations of routine clinical screening. Standard physical examinations, routine blood tests, and basic neurological assessments cannot detect a small, unruptured intracranial aneurysm. Cranial nerves function normally, cognitive processing remains intact, and systemic biomarkers generally show no specific abnormalities.
Because broad, population-wide screening using advanced neuroimaging techniques like magnetic resonance angiography (MRA) or computed tomography angiography (CTA) is neither cost-effective nor clinically indicated for asymptomatic individuals without specific risk profiles, silent aneurysms remain hidden in plain sight. They occupy a diagnostic blind spot until an imaging study is ordered for an entirely separate medical indication, or until the catastrophic event of a rupture forces emergency medical intervention. This diagnostic latency underscores why neurovascular researchers frequently categorize unruptured cerebral aneurysms as silent time bombs, not because all of them inevitably detonate, but because their quiet presence is fundamentally undetectable through standard medical oversight.
The silent timeline: Why Brain Aneurysms can go undetected for decades
When exploring the hidden nature of cerebrovascular abnormalities, one of the most pressing questions patients and medical researchers ask is: How long can you actually have a brain aneurysm without knowing it?
The short answer is decades, or even an entire lifetime. Because unruptured cerebral aneurysms typically develop silently, expanding at a microscopic or extremely gradual rate (often fractions of a millimeter per year), millions of people walk around completely unaware that a localized, weak pouch has formed on one of their brain’s arterial walls.
The Pathophysiology of "the silent years"
To understand why an aneurysm can remain hidden for so long, it helps to examine how these structures evolve. An aneurysm forms at the bifurcation points of major cerebral arteries, most commonly within the Circle of Willis at the base of the brain, where the muscular middle layer of the blood vessel wall is inherently thinner.
As hemodynamic stress (blood pressure and turbulent flow) beats against this vulnerable spot year after year, the wall balloons outward. During this developmental phase:
Absence of Pain Receptors: The brain tissue itself and the walls of intracranial arteries lack somatic pain receptors. Consequently, the physical stretching of the arterial wall does not trigger localized headaches or discomfort.
Preserved Neurological Function: Unless the expanding sac presses directly against a critical cranial nerve or restricts localized micro-circulation, surrounding brain regions continue to function seamlessly.
Variable Growth Trajectories: Clinical data demonstrates that many aneurysms remain static in size for decades after initial formation. Some studies suggest average growth rates are so minuscule that it can take upwards of 20 to 30 years for a small aneurysm to experience measurable structural shifts, provided external risk factors remain controlled.
Subtle clues: The "Sentinel" signs people miss
While true unruptured aneurysms are famously asymptomatic, a subset of patients experience subtle, transient warning signs months or even years before a major medical event. Unfortunately, these "sentinel symptoms" are frequently misattributed to everyday ailments:
The "Thunderclap" Warning (Sentinel Leaks): A micro-leak can sometimes occur, causing a sudden, sharp headache, often described as a "warning leak", that resolves on its own within hours## Unruptured Brain Aneurysms: Clinical Latency, Pathophysiology, and Long-Term Surveillance
While the initial formation and early silent phase of a cerebral aneurysm are critical medical concepts, understanding the long-term clinical latency, how long one can harbor an unruptured aneurysm without knowing it, requires a deep dive into neurovascular dynamics, diagnostic thresholds, and contemporary management strategies. For many individuals, an unruptured aneurysm remains completely asymptomatic throughout their entire lifetime, often discovered incidentally during neuroimaging performed for unrelated conditions such as headaches, sinus evaluations, or minor head trauma.
The natural history of Latency: Why some Aneurysms remain silent
The vast majority of saccular (berry) aneurysms begin as microstructural defects at the bifurcation points of major cerebral arteries, most commonly within the Circle of Willis. Once formed, their latency period is dictated by a delicate equilibrium between hemodynamic stress, the force exerted by pulsating blood flow, and the structural integrity of the arterial wall’s extracellular matrix.
During this latent phase, which can span decades or a full human lifespan, the aneurysm may undergo several distinct trajectories:
Static Stability: The most common fate for small aneurysms (under 5 millimeters) is structural arrest. Cellular repair mechanisms within the vascular wall manage to match or keep pace with the localized hemodynamic stress, preventing further outpouching or wall thinning. In these cases, the patient can have the aneurysm for 50, 60, or 80+ years without ever experiencing symptoms or rupture.
Slow Progressive Growth: In some patients, continuous pulsatile stress leads to the gradual degradation of collagen and elastin fibers. The aneurysm slowly expands over years. Even during slow growth, symptoms rarely manifest unless the expanding dome exerts localized mass effect on adjacent cranial nerves or brain parenchyma.
Remodeling and Thrombosis: Occasionally, partial thrombosis (clot formation) occurs within the aneurysm sac. While this alters blood flow dynamics, it does not guarantee clinical safety and can sometimes complicate subsequent surgical or endovascular interventions.
Subclinical manifestations: The "Warning signs" before a crisis
Although true asymptomatic aneurysms produce no neurological signals, a subset of patients experience subclinical or subtle symptoms years or months before a major rupture or catastrophic event. Recognizing these neurological red flags is vital for shortening the unknown latency period:
Sentinel Headaches: Often described as a "thunderclap" headache or an unusually severe, sudden headache unlike any previous episodes. These are frequently attributed to minor, sentinel leaks, microscopic seepage of blood through a thinning aneurysm wall prior to a full rupture.
Cranial Nerve Compression: Aneurysms located in specific anatomical locations can impinge on cranial nerves. For instance, a posterior communicating artery aneurysm can compress the oculomotor nerve (cranial nerve III), leading to acute ipsilateral pupil dilation, double vision (diplopia), or drooping of the eyelid (ptosis). Ophthalmic artery aneurysms can similarly affect vision by pressing on the optic chiasm or nerve.
Focal Neurological Deficits: Rare mass-effect symptoms can include transient ischemic attacks (TIAs), localized facial numbness, or subtle motor weakness if the expanding sac disrupts localized microcirculation or brain tissue.
Modern diagnostic horizons: Catching the unseen
Because the duration of an unknown aneurysm can span decades, modern preventative medicine increasingly relies on advanced neuroimaging to identify high-risk vascular anomalies before they transition from latent to lethal.
Magnetic Resonance Angiography (MRA): A non-invasive imaging modality that utilizes powerful magnetic fields and radio waves to visualize blood vessels within the brain without requiring contrast agents or ionizing radiation. MRA is the primary screening tool for individuals with a strong family history of intracranial aneurysms.
Computed Tomography Angiography (CTA): Utilizing rapid computed tomography combined with an intravenous iodine-based contrast injection, CTA provides exceptionally high-resolution 3D reconstructions of the cerebral vasculature, making it highly effective for detecting aneurysms greater than 2 to 3 millimeters in diameter.
Digital Subtraction Angiography (DSA): Regarded as the gold standard in vascular imaging, DSA involves catheterization (typically via the femoral or radial artery) to inject radiopaque contrast directly into the cerebral circulation, allowing for real-time fluoroscopic evaluation of blood flow dynamics, aneurysm neck morphology, and perforating vessel involvement.
Risk stratification: When to treat vs. When to monitor
Discovering an unruptured brain aneurysm initiates a complex risk-benefit analysis for neurovascular teams. Not all aneurysms require immediate surgical or endovascular intervention. The decision to treat a previously unknown aneurysm is guided by validated predictive models, such as the PHASES score (Population, Hypertension, Age, Size, Earlier subarachnoid hemorrhage, Site), which evaluates the cumulative 5-year rupture risk based on multiple clinical and morphological parameters.
Key determinants of rupture risk
Size and Morphology: Aneurysms under 7 millimeters in anterior circulation sites carry a notably low annual rupture risk, whereas those exceeding 10 millimeters (or possessing irregular, multilobed "daughter" sacs) exhibit significantly higher hemodynamic instability.
Anatomical Location: Aneurysms located in the posterior circulation (e.g., basilar artery, vertebrobasilar junction) carry a statistically higher risk of rupture compared to similar-sized aneurysms in the internal carotid artery.
Patient-Specific Factors: Active cigarette smoking, uncontrolled chronic hypertension, a history of excessive alcohol consumption, and a positive family history of intracranial aneurysms drastically elevate the risk of progression and rupture during the latency period.
For small, low-risk, incidental aneurysms, the management protocol often shifts to conservative surveillance, periodic MRA or CTA imaging paired with aggressive blood pressure management and smoking cessation counseling. Conversely, high-risk aneurysms are managed via minimally invasive endovascular coiling/flow diversion or traditional surgical microsurgical clipping to permanently isolate the lesion from the arterial circulation.
Living with vascular awareness
The question of how long someone can have a brain aneurysm without knowing it has no single numerical answer; for many, it is a silent companion for an entire lifetime, while for others, its presence is unmasked only when hemodynamic thresholds are breached. Advances in non-invasive neuroimaging continue to improve our ability to detect these silent vascular variations early. By understanding the underlying biology, recognizing subtle warning signs, and engaging in appropriate risk stratification, clinicians and patients can navigate the silent phase of cerebral aneurysms with precision, foresight, and improved long-term neurological outcomes.