When to worry about aneurysm size? A comprehensive clinical guide (part 1)
At the center of this anxiety lies a single, critical question: When do we actually need to worry about the size of an aneurysm?
In vascular medicine and neurosurgery, size is undeniably one of the most powerful predictors of rupture risk. However, viewing an aneurysm purely through the lens of a ruler or a caliper is a dangerous oversimplification. Understanding when an aneurysm becomes a threat requires looking at a sophisticated interplay between physical dimensions, anatomical location, biological morphology, and patient-specific risk factors.
This first part of our comprehensive guide explores the fundamentals of aneurysm sizing, how clinicians measure these vascular anomalies, and the baseline thresholds that separate routine monitoring from immediate clinical action.
1. The anatomy of a vascular weakness: What is an aneurysm?
Before examining size thresholds, it is essential to understand what an aneurysm is at a physiological level. Arteries are specialized, dynamic blood vessels designed to withstand the pulsatile pressure of blood being pumped from the heart. They consist of three distinct layers: the intima (inner lining), the media (muscular middle layer), and the adventitia (outer protective layer).
An aneurysm develops when a localized section of the arterial wall undergoes structural degradation, often due to a combination of genetic predisposition, chronic hypertension, atherosclerosis, and hemodynamic stress. As the muscular and elastic fibers of the media break down, the wall loses its structural integrity. Under the relentless force of blood pressure, the wall balloons outward, creating a pouch or sac.
Saccular Aneurysms ("Berry"): These look like tiny berries attached to the side of a main blood vessel, most commonly found in the cerebral circulation (the Circle of Willis). They have a distinct "neck" and "dome," and their morphology plays a massive role in rupture risk.
Fusiform Aneurysms: These involve a circumferential widening of the entire blood vessel wall, creating a spindle-shaped bulge rather than a localized pouch. These are frequently found in the aorta and certain segments of intracranial arteries.
Because the wall of an aneurysm is inherently thinner and structurally compromised than healthy vascular tissue, the primary clinical concern is rupture, which can lead to catastrophic internal bleeding, stroke, or death. This is why determining the precise size of the sac is the cornerstone of clinical decision-making.
2. The precision of measurement: How clinicians quantify risk
When a radiologist or vascular specialist evaluates an aneurysm, precision is paramount. A difference of just two millimeters can mean the difference between a recommendation for conservative surveillance ("watch and wait") and immediate surgical or endovascular intervention.
Modern imaging modalities allow for exceptional precision:
Computed Tomography Angiography (CTA): Uses X-rays combined with a contrast dye to generate detailed 3D reconstructions of blood vessels. CTA is exceptionally fast and provides clear visualization of calcifications and bone-vessel relationships.
Magnetic Resonance Angiography (MRA): Utilizes magnetic fields and radio waves (often without contrast) to map blood flow and vascular structures. It is frequently used for serial monitoring of unruptured brain aneurysms because it avoids ionizing radiation.
Digital Subtraction Angiography (DSA): The gold standard of vascular imaging. A catheter is guided through the arterial system (usually from the groin or wrist) to inject contrast dye directly into the target vessels, capturing high-resolution dynamic video of blood flow.
Duplex Ultrasound: The primary screening and monitoring tool for abdominal aortic aneurysms (AAAs), offering safe, non-invasive, real-time measurements without radiation.
When reviewing these scans, specialists measure multiple dimensions: the maximum transverse diameter, the neck width, and the height of the dome. In clinical practice, however, maximum diameter remains the universal baseline metric used in guidelines worldwide.
3. Categorizing Aneurysms by size: General thresholds
While specific risk thresholds vary depending on whether an aneurysm is located in the brain, the chest (thoracic aorta), or the abdomen (abdominal aorta), vascular specialists generally group aneurysms into broad sizing categories to guide management:
Small Aneurysms
Brain (Intracranial): Typically under 7 millimeters (mm). The vast majority of small, unruptured incidental brain aneurysms carry a very low annual rupture risk, particularly in patients with no history of prior subarachnoid hemorrhage.
Abdominal Aorta (AAA): Between 3.0 cm and 4.4 cm. These are typically managed with lifestyle modifications (smoking cessation, blood pressure control) and surveillance ultrasounds every 6 to 12 months.
Medium Aneurysms
Brain (Intracranial): Between 7 mm and 12 mm. Risk begins to escalate, especially when combined with high-risk anatomical locations or patient risk factors.
Abdominal Aorta (AAA): Between 4.5 cm and 5.4 cm. Surveillance intervals typically shorten (every 3 to 6 months), and discussions regarding elective repair begin if rapid growth is detected.
Large to giant Aneurysms
Brain (Intracranial): Large aneurysms measure 13 mm to 24 mm; Giant aneurysms measure 25 mm (2.5 cm) or greater. These carry a significantly elevated risk of rupture and can also cause neurological deficits by exerting mass effect on surrounding brain tissue or cranial nerves.
Abdominal Aorta (AAA): 5.5 cm or greater. In standard clinical guidelines, this threshold represents the point where the cumulative risk of rupture outweighs the surgical risks of elective repair, prompting a strong recommendation for intervention (open surgery or endovascular aneurysm repair - EVAR).
4. Size as a primary metric, but not the sole predictor
A common misconception among patients is that size is the only thing that matters. Landmark epidemiological studies, such as the International Study of Unruptured Intracranial Aneurysms (ISUIA), revealed a more complex reality. While a larger size undeniably correlates with a higher likelihood of rupture, location and patient history are equally critical variables.
For instance, an intracranial aneurysm measuring 5 mm located in the cavernous internal carotid artery carries a remarkably low lifetime rupture risk. Conversely, an aneurysm of the exact same size (5 mm) situated in the posterior circulation (such as the basilar tip or posterior inferior cerebellar artery) statistical models show a significantly higher baseline risk of rupture.
Biological and lifestyle factors heavily modulate how dangerous a given size is:
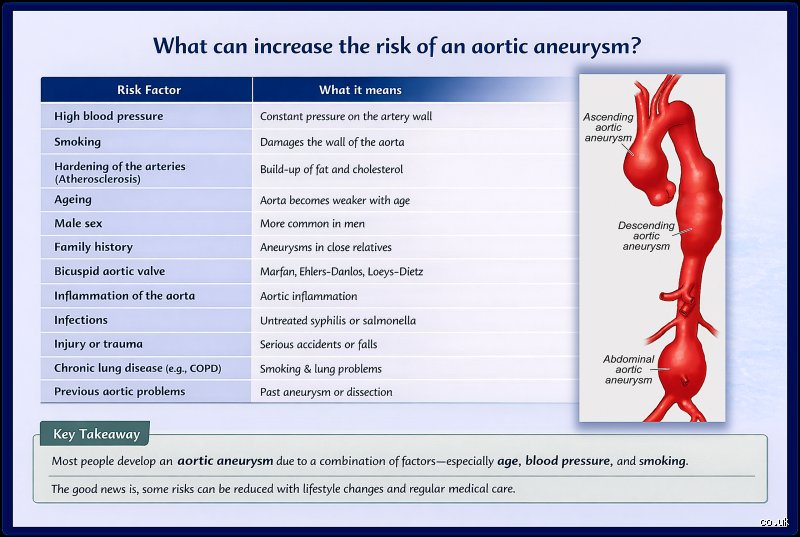
Active Cigarette Smoking: Dramatically accelerates vascular wall degradation and increases rupture risk across all sizes.
Uncontrolled Hypertension: Increases the hemodynamic wall stress acting upon the aneurysm dome.
Family History: Patients with a first-degree relative who has suffered an aneurysm rupture often have lower threshold guidelines for intervention because their familial vascular tissue may be inherently more fragile.
Morphological Irregularities: The presence of "blebs" (secondary miniature bulges protruding from the main dome) or an irregular, multi-lobed shape indicates structural instability, even in smaller aneurysms.
Summary and what to expect in part 2
Size is the foundational metric clinicians use to gauge the urgency of an aneurysm, but it is part of a much broader clinical equation. Small aneurysms are frequently monitored safely over many years, while larger lesions or those in high-risk zones demand proactive intervention.
In the second part of this guide, we will dive deeper into location-specific risk profiles, the difference between monitoring and surgical/endovascular treatment options (such as coiling, flow diversion, and surgical clipping), and the crucial lifestyle modifications proven to stabilize vascular health.
Disclaimer: This article is for educational and informational purposes only and should not be construed as medical advice. Any concerns regarding vascular health or aneurysm diagnosis should be discussed directly with a qualified neurosurgeon, vascular surgeon, or cardiologist.
Location matters: Cerebral versus aortic thresholds
When evaluating aneurysm size, the anatomical site changes the calculus entirely. The body handles vascular stress differently depending on whether a bulge forms within the high-pressure circulatory network of the brain or along major systemic pathways## Monitoring Protocols and Imaging Surveillance
For patients diagnosed with an unruptured brain aneurysm that does not immediately meet the criteria for surgical or endovascular intervention, active monitoring and surveillance become the cornerstone of long-term management. Because brain aneurysms are dynamic structures that can change over time, establishing a structured imaging schedule is vital for catching growth or morphological shifts before a catastrophic rupture occurs.
The standard Surveillance schedule
Typically, neurologists and neurosurgeons recommend a baseline follow-up imaging session approximately 6 months to 1 year after the initial discovery of an unruptured aneurysm. This initial scan helps clinicians establish the stability of the lesion, essentially checking whether it is static or actively changing.
Stable Findings: If the aneurysm shows zero growth and no structural changes on the one-year follow-up, the interval between subsequent scans is often extended to every 2 to 3 years, depending on the patient's overall health profile, age, and risk factors.
High-Risk Profiles: Patients with a history of smoking, uncontrolled hypertension, a strong family history of subarachnoid hemorrhage, or aneurysms located in high-risk territories (such as the posterior circulation) may require more frequent, rigorous monitoring schedules.
Imaging modalities used in Surveillance
To minimize patient burden while maximizing diagnostic accuracy, medical teams utilize advanced, non-invasive imaging techniques:
Magnetic Resonance Angiography (MRA): Often the preferred choice for long-term monitoring because it utilizes powerful magnetic fields and radio waves rather than ionizing radiation. MRA allows clinicians to visualize the blood vessels in the brain in high detail and measure the exact dimensions of the aneurysm sac over time.
Computed Tomography Angiography (CTA): While highly accurate and rapid, CTA involves exposure to ionizing radiation and contrast dye. It is frequently utilized if MRA results are inconclusive or if rapid, high-resolution bone-to-vessel anatomical mapping is required prior to a procedural intervention.
Digital Subtraction Angiography (DSA): Considered the gold standard for vascular imaging, DSA is an invasive catheter-based procedure. Because it carries a small procedural risk, it is rarely used for routine, low-risk surveillance, but it is indispensable when planning endovascular coiling or surgical clipping.
Modifiable risk factors and lifestyle Management
While anatomical dimensions and genetic predispositions are fixed variables, patients diagnosed with an aneurysm possess significant power over modifiable risk factors. Controlling these elements can drastically alter the natural history of an aneurysm, reducing the likelihood of growth, weakening of the wall, or sudden rupture.
1. Rigorous blood pressure control
Hypertension is arguably the single most critical modifiable risk factor associated with aneurysm rupture. Chronic high blood pressure exerts continuous, elevated mechanical stress on the already thinned walls of the aneurysm sac.
Target Metrics: Most medical guidelines recommend maintaining blood pressure consistently below 130/80 mmHg for individuals with unruptured aneurysms.
Management Strategies: This is achieved through a combination of tailored antihypertensive medications (such as ACE inhibitors, ARBs, or beta-blockers), regular blood pressure monitoring at home, and sodium reduction in the diet.
2. Smoking Cessation
Tobacco smoke introduces numerous toxic compounds into the bloodstream that cause endothelial dysfunction, systemic inflammation, and accelerated atherosclerosis. Clinical studies consistently demonstrate that current smokers have a substantially higher risk of both aneurysm formation and rupture compared to non-smokers.
The Healing Process: Quitting smoking halts the ongoing chemical degradation of the vascular walls and improves overall endothelial health. Healthcare providers strongly encourage utilization of cessation aids, including nicotine replacement therapies, counseling, and prescription support medications.
3. Managing physical exertion and valsalva maneuvers
Sudden, extreme spikes in blood pressure, often caused by heavy lifting, straining, or intense isometric exercises, can temporarily increase intracranial pressure and stress cerebral vessels.
Safe Activity: Moderate aerobic exercises, such as brisk walking, swimming, or cycling, are generally encouraged as they support cardiovascular health without inducing dangerous blood pressure spikes.
Precautions: Patients should consult their neurologist regarding specific weightlifting limits or high-intensity training regimens to ensure their physical routine remains safe.
When to seek emergency medical attention
Even with careful monitoring and strict lifestyle management, patients and their families must remain vigilant. Recognizing the warning signs of a sentinel bleed (a small, preliminary leak) or an acute rupture is critical for saving lives, as immediate emergency intervention drastically improves survival and recovery outcomes.
The Classic "Thunderclap Headache"
The hallmark symptom of an acute aneurysm rupture is a sudden, excruciating headache unlike anything the patient has ever experienced before.
Characteristics: Often described by survivors as the "worst headache of my life," this pain typically reaches maximal intensity within seconds to a minute.
Distinction: Unlike a standard migraine or tension headache, which builds gradually, a rupture-induced headache strikes with explosive suddenness.
Associated neurological red flags
Depending on the exact location of the bleeding or the pressure exerted by a rapidly expanding aneurysm, patients may exhibit a cluster of acute neurological symptoms. If you or someone you know experiences any of the following signs alongside a severe headache, call emergency services immediately:
Visual Disturbances: Sudden double vision, blurred vision, loss of vision, or drooping eyelids (often linked to compression of the third cranial nerve).
Focal Deficits: Sudden numbness, weakness, or paralysis, typically affecting one side of the face or body.
Cognitive and Mental Status Changes: Confusion, lethargy, sudden extreme drowsiness, disorientation, or loss of consciousness.
Autonomic Symptoms: Nausea, vomiting, sudden sensitivity to light (photophobia), or a stiff neck.
Seizures: New-onset seizure activity triggered by the acute irritation of brain tissue.
Crucial Takeaway: Never wait to see if a "thunderclap" headache will pass on its own. Time is brain tissue, and early arrival at an emergency department equipped with neurosurgical capabilities is the single most important factor in determining the outcome of a ruptured aneurysm.
Balancing vigilance with quality of life
Navigating a diagnosis of a brain aneurysm is undoubtedly a psychological and medical journey. The realization that a silent, fragile blood vessel resides within the brain can provoke understandable anxiety, fear, and hyper-vigilance. However, understanding the nuances of aneurysm size, location, risk factors, and monitoring protocols transforms fear into an actionable, structured healthcare plan.
The decision to treat or monitor an unruptured aneurysm is a deeply personalized partnership between the patient and an experienced multidisciplinary team comprising neurologists, neurosurgeons, and interventional neuroradiologists. By synthesizing anatomical data, such as size, shape, and growth rate, with individual health profiles and lifestyle factors, modern medicine can expertly navigate the fine line between overtreatment and dangerous neglect.
With rigorous blood pressure control, smoking cessation, and adherence to recommended imaging schedules, the vast majority of patients with unruptured aneurysms live long, active, and healthy lives, successfully keeping the threat of rupture at bay.
How has your medical team discussed monitoring or managing your specific situation so far?