Introduction: The Anatomy of a Vascular Crisis
When patients or medical students first encounter the pathology of vascular disease, one of the most frequently asked yet profoundly complex questions is: "What is the worst aneurysm to have?"
On the surface, the answer might seem straightforward. An aneurysm is, by definition, a localized, balloon-like swelling or bulge in the wall of a blood vessel, occurring because the structural integrity of that vessel wall has compromised and weakened under the relentless, pulsatile pressure of blood flow.
However, ask any neurosurgeon, vascular surgeon, or cardiothoracic specialist this question, and you will receive a nuanced, highly guarded answer. The "worst" aneurysm cannot be declared based on size alone. Instead, it is determined by a confluence of lethal variables:
Anatomical Location: The specific vessel involved and its proximity to critical organ systems (such as the central nervous system or the heart).
Hemodynamic Environment: The sheer volume of blood flow and pressure pulsing through the affected vessel.
Symptomatic Stealth: Whether the aneurysm presents with early warning signs or remains entirely asymptomatic—a true "silent killer"—until the moment of rupture.
Interventional Accessibility: How surgically accessible the vessel is, and whether emergency intervention can be deployed quickly enough to save the patient’s life.
To truly understand what makes one aneurysm more perilous than another, we must dive deep into vascular hemodynamics, tissue mechanics, and the specific pathology of arterial beds throughout the human body. This first part of our comprehensive expert analysis will establish the foundational physics of aneurysms, map the primary contenders across the human anatomy, and deeply examine the catastrophic threat posed by thoracic aortic pathologies.
The Physics of Failure: Why Aneurysms Kill
To evaluate which aneurysm is the most dangerous, we must first examine the mechanical forces at play within the circulatory system. Arteries are not inert rubber tubes; they are dynamic, multi-layered living structures composed of an inner endothelial lining (tunica intima), a robust middle layer of smooth muscle and elastic fibers (tunica media), and an outer protective connective tissue sheath (tunica adventitia).
When genetic predispositions, chronic hypertension, atherosclerosis, trauma, or inflammatory diseases degrade the elastin and collagen matrix of the tunica media, the wall loses its elasticity and structural resilience. According to the physiological principles governing wall tension (famously modeled by Laplace's Law in vascular mechanics), as the radius of a blood vessel increases at a localized weakened spot, the tension on the remaining wall fibers increases proportionally.
This creates a vicious, self-perpetuating mechanical cycle:
A small section of the vessel wall weakens and bulges outward.
The radius of the vessel at that site increases.
Wall tension rises, forcing further expansion.
The remaining wall tissue thins out exponentially, bringing the structure closer to its ultimate tensile breaking point.
When this structural failure occurs in a low-pressure venous bed, the consequences, while serious, often unfold more slowly. But when it occurs in high-pressure arterial beds—directly connected to the pumping power of the heart—the results are measured in seconds.
Mapping the Contenders: The Vascular Spectrum
Aneurysms can theoretically form in any artery in the body, but clinical medicine generally categorizes them into three primary domains based on their anatomical territory:
1. Central Nervous System (Cerebral Aneurysms)
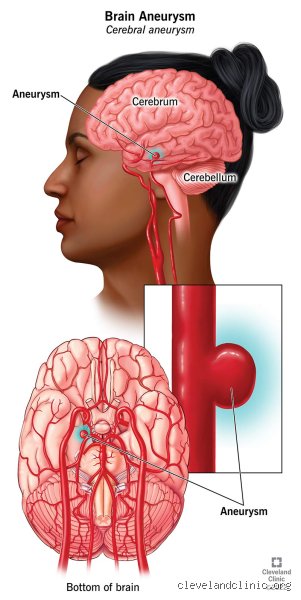
Saccular (Berry) Aneurysms: Small, pouch-like bulges that typically form at the bifurcations of the major arteries at the base of the brain (the Circle of Willis).
Fusiform Aneurysms: A symmetrical widening of the entire circumference of a cerebral artery segment, often harder to clip or coil surgically.
2. The Great Conduit (Aortic Aneurysms)
Thoracic Aortic Aneurysms (TAA): Developing in the chest cavity, encompassing the aortic root, ascending aorta, aortic arch, and descending thoracic aorta.
Abdominal Aortic Aneurysms (AAA): Occurring below the diaphragm in the abdomen, representing the most frequently diagnosed form of aortic aneurysm.
3. Peripheral and Visceral Aneurysms
Visceral Artery Aneurysms: Affecting vessels supplying internal organs such as the splenic artery, renal artery, or mesenteric arteries.
Peripheral Aneurysms: Most commonly found in the popliteal artery behind the knee or the femoral artery in the groin.
While a ruptured popliteal aneurysm can lead to limb-threatening ischemia due to downstream blood clots, and a ruptured splenic artery aneurysm carries an exceptionally high mortality rate in pregnant individuals, the consensus among trauma surgeons and vascular specialists points toward the central vascular hubs—the brain and the aorta—when discussing the absolute "worst" variants.
Deep Dive into Category One: Thoracic Aortic Pathologies
If we evaluate the sheer volume of blood flow, baseline mortality, and the speed at which death occurs, many cardiovascular experts point to Thoracic Aortic Aneurysms (TAAs)—specifically those involving the ascending aorta that progress to Type A Aortic Dissections—as strong contenders for the most lethal vascular events known to human medicine.
The Anatomy of the Ascending Aorta
The aorta is the body's master highway, directly receiving 100% of the oxygenated blood output ejected by the left ventricle of the heart with every single heartbeat. The ascending aorta experiences immense, repetitive hydraulic shock waves.
When an aneurysm forms in this specific segment, or when the inner layer of the aorta tears—allowing high-pressure blood to tunnel between the layers of the vessel wall (a dissection)—the structural integrity of the entire circulatory system is instantly compromised.
Why Type A Aortic Dissection is Terrifyingly Lethal
Medical literature classifies thoracic aortic dissections using the Stanford system:
Stanford Type A: Involves the ascending aorta (and potentially extends down into the arch and descending aorta). This is a absolute surgical emergency.
Stanford Type B: Involves only the descending aorta (starting after the left subclavian artery branches off), which is often managed medically or with less invasive endovascular stents unless complications arise.
A Type A dissection originating from a thoracic aortic weakness is widely considered one of the most terrifying medical emergencies on the planet for several reasons:
The Mortality Clock Ticks Extremely Fast: Statistically, for every hour that passes after the onset of an acute Type A aortic dissection without surgical intervention, the patient’s mortality rate increases by roughly 1% to 2%. Within the first 24 to 48 hours, up to 40% to 50% of untreated patients will die.
Catastrophic Cascading Failures: As the false lumen (the blood-filled channel tearing through the wall) expands, it can occlude critical branch vessels departing from the aortic arch. This means a single aortic event can simultaneously trigger:
Massive Stroke: By cutting off blood flow to the carotid arteries supplying the brain.
Acute Myocardial Infarction (Heart Attack): By dissecting backward into the coronary ostia that feed the heart muscle itself.
Cardiac Tamponade: If the tear breaks completely through the outer wall into the pericardial sac, filling the sac with blood and crushing the heart so it can no longer beat (pulseless electrical activity and rapid death).
Acute Aortic Valve Regurgitation: Causing sudden, catastrophic heart failure as the aortic valve ring is distorted and leaks massively.
Deceptive and Sudden Presentation: Like many aneurysms, a thoracic aortic aneurysm often expands silently.
When it begins to dissect or rupture, the patient typically experiences an abrupt, tearing, or ripping pain felt intensely in the chest, back (between the shoulder blades), or neck. This pain is frequently mistaken by patients—and occasionally by emergency responders—for a standard heart attack, delaying critical specialized triage unless high clinical suspicion is maintained.
Looking Ahead
While the thoracic aorta presents a mechanical nightmare of high pressure and multi-organ threat, cerebral aneurysms introduce an entirely different dimension of danger, tied directly to the delicate, confined environment of the skull and the irreplaceable nature of neurological tissue.
In the subsequent section of this analysis, we will explore the landscape of cerebral berry aneurysms, the devastating reality of subarachnoid hemorrhage, and weigh the anatomical advantages and disadvantages of brain versus aortic vascular failures to determine which truly holds the title of the worst aneurysm to encounter.
Diagnostic Challenges and the Importance of Screening
When discussing the worst aneurysms to have—namely, large aortic dissections or ruptured abdominal aortic aneurysms—the margin between life and death often hinges on timely detection.
Medical guidelines strongly advocate for targeted screening protocols, particularly for high-risk demographics. For instance, a single abdominal ultrasound screening is recommended for men aged 65 to 75 who have a history of smoking.
Modern Treatment Breakthroughs and Surgical Interventions
The prognosis for individuals diagnosed with high-risk vascular balloons has improved dramatically over recent decades, thanks to revolutionary advancements in surgical techniques. While traditional open-chest or open-abdomen surgeries remain vital for complex cases, minimally invasive endovascular aneurysm repair (EVAR) and thoracic endovascular aortic repair (TEVAR) have transformed patient recovery.
Endovascular Stent Grafting: Surgeons navigate specialized delivery systems through small incisions in the groin, placing a synthetic graft inside the weakened artery to reinforce the wall and divert blood flow away from the danger zone.
Fenestrated and Branched Devices: Custom-engineered grafts now allow specialists to treat aneurysms close to critical visceral branches (such as the renal and mesenteric arteries) without sacrificing vital organ perfusion.
Emergency Rapid Protocols: Major medical centers utilize coordinated response systems (often called "Code Rupture" protocols) to streamline imaging, anesthesia, and surgical teams the moment a patient arrives with a suspected tear.
Preventive Strategies and Long-Term Management
Mitigating the risk of developing a catastrophic vascular event involves strict management of underlying cardiovascular risk factors. Because continuous mechanical stress weakens arterial walls over time, keeping systemic blood pressure within a healthy range is paramount.
Patients diagnosed with smaller aneurysms that do not yet meet the surgical threshold must commit to lifelong lifestyle modifications. Key pillars of preventative management include:
Smoking Cessation: Stopping tobacco use significantly slows the expansion rate of arterial walls and reduces overall vascular inflammation.
Blood Pressure Control: Regular monitoring and adherence to antihypertensive medications minimize peak forces exerted on vulnerable vessel segments.
Cholesterol Management: Controlling lipid profiles helps curb atherosclerosis, which stiffens and damages arterial structures.
Regular Surveillance Imaging: Periodic CT scans or ultrasounds ensure that any dimensional changes are caught early, allowing medical teams to act proactively rather than reactively.
Ultimately, while aortic and complex cerebral aneurysms carry some of the most daunting survival statistics in modern medicine, heightened awareness, targeted screening, and swift surgical execution continue to save countless lives each year.