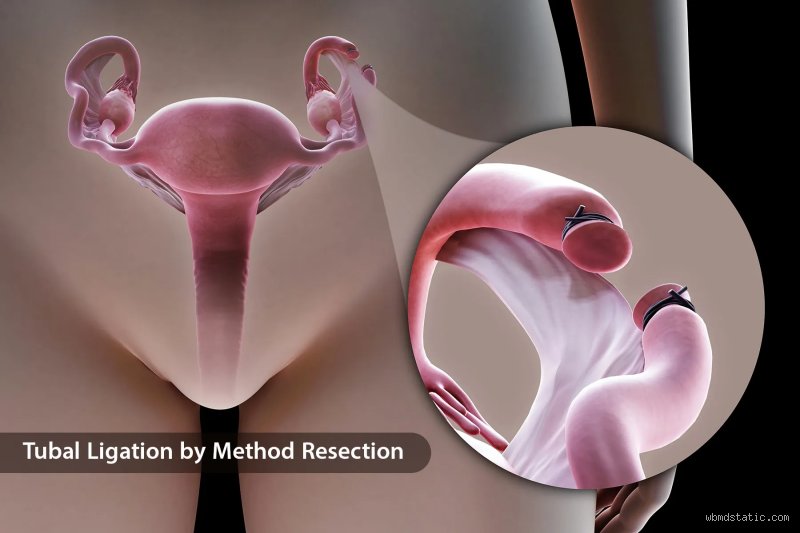
Tubal ligation, often colloquially referred to as "having one's tubes tied," stands as one of the most definitive and widely chosen forms of permanent female sterilization worldwide. Millions of individuals opt for this surgical intervention during their reproductive years, driven by the profound certainty that their family-building journeys are complete. Yet, while the immediate postoperative recovery period—characterized by a few days of abdominal soreness, fatigue, and the gradual return to daily activities—receives extensive documentation in medical literature, the long-term horizon remains comparatively opaque in the public consciousness.
What truly happens to the human body, the hormonal landscape, and the psychological wellbeing of an individual a decade after undergoing this procedure?
To answer this comprehensively, one must look far beyond the operating room and examine the intricate, decade-long interplay between surgical anatomy, natural biological aging, and the psychological evolution of identity.
The Myth of Hormonal Disruption: Debunking the Ten-Year Aftermath
One of the most persistent and anxiety-inducing myths surrounding tubal ligation is the fear of premature menopause or abrupt hormonal chaos. Patients frequently voice concerns that sealing, cutting, or removing the fallopian tubes will somehow choke off the blood supply to the ovaries, plunging them into a premature hormonal winter long before their natural time.
Because the ovaries derive their primary vascular supply from the ovarian arteries—which branch directly from the aorta—and not from the fallopian tubes themselves, their endocrine function remains entirely undisturbed by the procedure.
And this physiological independence is precisely why comprehensive long-term studies, including the landmark Collaborative Review of Sterilization (CREST) study funded by the Centers for Disease Control and Prevention, have consistently demonstrated that tubal ligation does not induce early menopause.
But what about the phenomenon known colloquially as "post-tubal ligation syndrome"?
While some individuals report irregular cycles, heavier bleeding, or heightened mood swings years after their surgery, mainstream gynecological science attributes these symptoms not to the tubal ligation itself, but to the natural transition of perimenopause, the removal of prior hormonal contraceptives (such as oral contraceptive pills or hormonal intrauterine devices that previously masked underlying cycle irregularities), or simply the normal chronological aging of the endocrine system. (It is worth noting that many patients who previously relied on hormonal birth control methods experience a stark awakening when those exogenous hormones cease, mistaking natural bodily shifts for surgical side effects.)
Ten years post-procedure, the ovaries continue to produce estrogen and progesterone according to their genetically programmed timeline, meaning that the natural onset of menopause occurs at virtually the exact same average age for sterilized individuals as it does for their non-sterilized peers.
Anatomical Evolution and the Ten-Year Scarscape
Surgical scars are living, dynamic tissues that undergo a fascinating maturation process over the span of a decade. Immediately following a laparoscopy or minilaparotomy for tubal ligation, the abdominal incisions appear pink, slightly raised, and tender to the touch. Over the ensuing ten years, collagen remodeling gradually softens these marks, transforming them into pale, flat, nearly imperceptible silver lines hidden within natural skin folds or the pubic hairline.
Internally, however, the anatomical narrative is equally compelling. The fallopian tubes, once patent conduits designed to capture an oocyte released from the ovary and guide it toward the uterus, have undergone significant fibrosis. Depending on the specific technique utilized a decade prior—whether through postpartum partial salpingectomy (the Pomeroy technique), bipolar electrocoagulation, mechanical silicone rings (Falope rings), spring-loaded clips (Filshie clips), or complete bilateral salpingectomy (which has increasingly become the gold standard due to its emerging role in ovarian cancer risk reduction)—the local tissue has settled into a permanent state of fibrous closure.
Could the body attempt to undo this surgical permanence through recanalization?
While extremely rare, spontaneous recanalization—where the severed ends of the tubes miraculously find a way to reconnect through microscopic fistula formation—can theoretically occur, though it is statistically insignificant on a population level over a ten-year window.
For the vast majority, the internal landscape is one of absolute permanence: scar tissue encapsulates the ligation sites, and the surrounding pelvic organs glide smoothly against one another, largely indifferent to the structural alterations introduced years prior.
Psychological Resilience, Regret, and the Passage of Time
The psychological dimensions of tubal ligation ten years down the line are perhaps the most nuanced, deeply personal, and variable aspects of the entire post-surgical journey. When a person in their late twenties or thirties elects for permanent sterilization, they are making a binding contract with their future self—a self that they cannot possibly fully know or predict.
And this brings us to the profound emotional dichotomy that defines the decade-mark milestone: for the overwhelming majority of individuals, the passage of ten years solidifies a deep, unshakeable sense of reproductive liberation, freeing them from the cognitive load, hormonal side effects, and daily vigilance of contraception, yet for a small, statistically documented minority (ranging anywhere from five to twenty percent depending on age at the time of surgery and underlying socioeconomic factors), the ten-year mark introduces a complex wave of grief, shifting desires, or existential questioning regarding lost fertility.
And so, as life circumstances shift—perhaps through unexpected divorce, the loss of a child, the formation of a new partnership with a partner who desires children, or simply the psychological maturation that accompanies entering a new decade of life—the permanence of tubal ligation transforms from a welcome shield into a formidable wall.
When regret strikes a decade later, it is rarely a superficial whim; rather, it is a profound, deeply felt mourning for a biological door that was locked long ago with the best available intentions.
Conversely, for those who experience sustained peace with their decision, the ten-year anniversary is a quiet, powerful celebration of bodily autonomy, a silent acknowledgement that their reproductive destiny remained entirely within their own hands, unburdened by fear, failure rates, or future planning.
Long-Term Health Outcomes and Physiological Shifts
Decade-long evaluations of tubal ligation reveal important physiological patterns that extend far beyond initial recovery periods. While primary contraceptive goals are permanently achieved in the vast majority of cases, the aging body interacts with altered tubal anatomy in ways that become clinically observable around the ten-year mark.
One of the most notable long-term phenomena is the alteration of menstrual bleeding profiles. Although permanent sterilization does not directly induce early menopause, patients often report a distinct evolution in their cycle characteristics as they transition through their late thirties and forties. This is largely attributed to natural perimenopausal hormone fluctuations rather than the surgical procedure itself. However, women who relied on hormonal contraceptives prior to undergoing sterilization frequently note heavier or more painful menses once those artificial hormones are removed from the equation—a contrast that becomes pronounced over a ten-year horizon.
Ovarian Function and Hormonal Longevity
A persistent clinical question surrounds the long-term impact of tubal ligation on ovarian blood supply and endocrine output. Extensive epidemiological tracking over ten years confirms that permanent occlusion of the fallopian tubes does not accelerate the onset of natural menopause. The primary blood supply to the ovaries originates from the ovarian arteries, which remain undisturbed during standard tubal ligation procedures (whether via postpartum partial salpingectomy, laparoscopic electrocoagulation, or mechanical banding).
Psychological and Quality-of-Life Dimensions
The psychological landscape a decade after tubal ligation is overwhelmingly characterized by sustained reproductive autonomy and peace of mind. Clinical surveys tracking patients ten years post-procedure demonstrate high levels of satisfaction, particularly among individuals who finalized their family planning goals early.
Despite this high overall satisfaction rate, a small percentage of patients experience psychological adjustment challenges, occasionally termed post-tubal sterilization syndrome in older literature—though contemporary medicine attributes these symptoms to co-existing gynecological conditions like adenomyosis, endometriosis, or natural hormonal shifts rather than a direct psychological syndrome caused by the surgery. Comprehensive counseling prior to the initial procedure remains the single most effective safeguard against long-term regret.