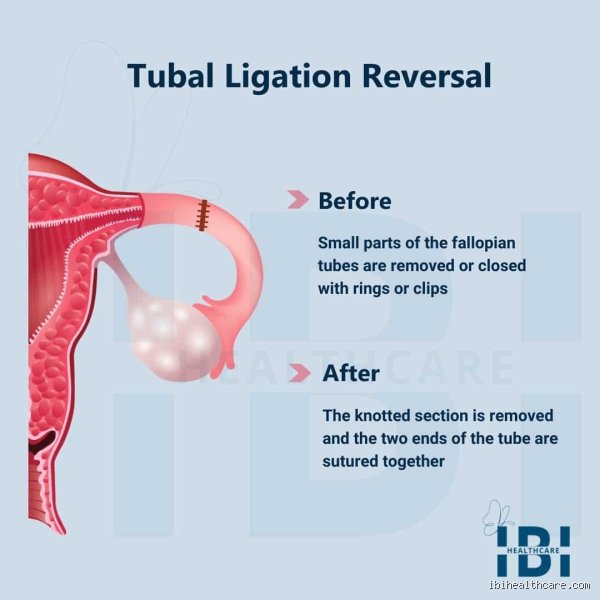
Mechanisms of spontaneous tubal recanalization
When a fallopian tube undergoes spontaneous recanalization, it does not regenerate wholesale in the manner of an amphibian limb; rather, it heals through a localized inflammatory and fibrotic repair process. The human body treats surgical disruption—whether a segment of the tube is excised, cauterized, banded, or clipped—as a wound requiring immediate healing.
The inner epithelial lining of the fallopian tube, known as the mucosa, possesses high cellular turnover and regenerative capacity. If the severed or occluded ends of the tube remain in close anatomical proximity, or if a thermal injury creates a slow-healing fistula, mucosal cells can proliferate across the microscopic gap. Over time, these cells form a continuous epithelial micro-channel through the scar tissue. While this passage is often exceptionally narrow, frequently measuring only fractions of a millimeter, it can be entirely sufficient to allow a microscopic spermatozoon to traverse upstream to fertilize an oocyte, or to permit a newly fertilized zygote to drift down toward the uterine cavity.
The probability of this biological bridge forming depends heavily on the specific technique utilized during the original sterilization procedure:
Electrocoagulation: Techniques that utilize thermal energy to burn and destroy significant lengths of the fallopian tube generally present the lowest risk of spontaneous recanalization. The extensive tissue destruction creates a wide thermal gap that is difficult for mucosal cells to bridge.
Partial Salpingectomy (Pomeroy and Modified Techniques): Removing a distinct segment of the tube significantly reduces the likelihood of natural reconnection, though rare failures still occur if a tuboperitoneal fistula develops or if stumps migrate close together.
Mechanical Barriers (Clips and Rings): Methods that compress the tube without destroying a large segment sometimes leave room for tissue necrosis and subsequent minor shifting, which can occasionally allow a micro-channel to form over a multi-year period.
Clinical implications and the danger of ectopic pregnancy
The phenomenon of spontaneous recanalization carries unique medical risks that differentiate it from intended fertility treatments. When a fallopian tube reconnects via uncontrolled scar remodeling, the newly formed internal pathway is invariably irregular, scarred, and lacking normal muscular peristalsis.
These structural defects severely impair the tube's natural ability to transport a fertilized egg into the uterus. Consequently, while spontaneous recanalization can occasionally result in a normal intrauterine pregnancy, it is statistically disproportionately associated with ectopic pregnancy, a life-threatening condition where the embryo implants outside the uterine cavity, most commonly within the narrow confines of the fallopian tube itself.
Patients who have undergone tubal ligation should remain vigilant. Because sterilization failure rates generally range between 0.2%0.2\%0.2% and 2%2\%2% cumulatively over a woman's reproductive lifetime, any delayed symptoms suggestive of pregnancy, such as missed menstrual cycles, unilateral pelvic cramping, or abnormal spotting, warrant immediate clinical evaluation, regardless of how many years have passed since the original procedure.
Conclusion
While popular misconceptions suggest that fallopian tubes can easily "grow back together" like untied shoelaces, true spontaneous recanalization is an uncommon and highly unpredictable biological event driven by microscopic tissue remodeling and epithelial regeneration. Sterilization remains a permanent and exceptionally effective form of birth control, yet the inherent regenerative capability of human tissue means that the risk of failure is never truly zero. For patients seeking to restore fertility deliberately, structured microsurgical tubal reanastomosis remains the gold standard, offering controlled anatomical alignment and high success rates that starkly contrast with the erratic nature of spontaneous recanalization.