The historical foundations of Inflammation: From Celsus to modern medicine
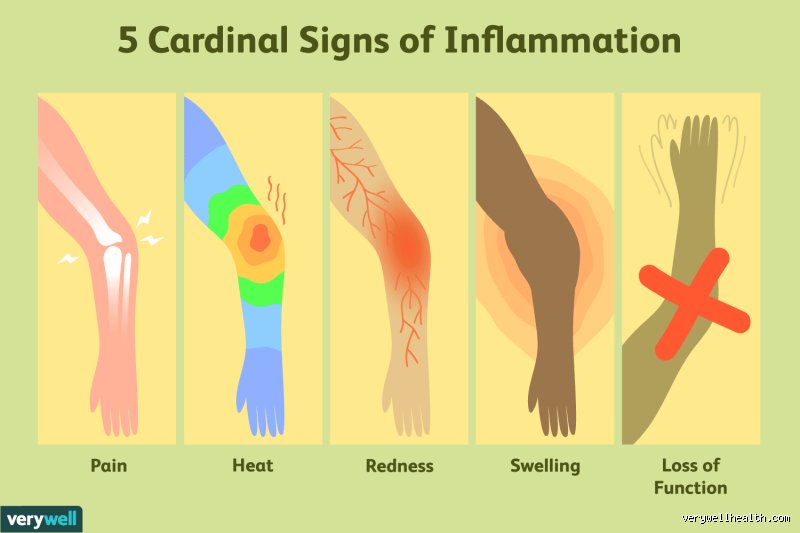
The scientific journey to defining inflammation began over two thousand years ago. Around the first century AD, the Roman encyclopedist Aulus Cornelius Celsus documented the physical manifestations of an inflamed tissue in his monumental medical treatise De Medicina. Celsus identified four distinct local cardinal signs that occur when the body responds to trauma, infection, or irritation:
Rubor (Redness)
Calor (Heat)
Tumor (Swelling)
Dolor (Pain)
Centuries later, around the middle of the nineteenth century, the German pathologist Rudolf Virchow—often hailed as the father of modern cellular pathology—added a fifth sign to the canon: functio laesa, or the loss of function. While Virchow's addition completed the classic clinical picture of acute inflammation, the original four signs identified by Celsus remain the cornerstone of how physicians and researchers recognize acute inflammatory responses in clinical practice today.
To appreciate why these four signs occur, we must dive deep into the microscopic battleground of the immune system. Inflammation is not a single process; it is a meticulously coordinated vascular and cellular cascade designed to isolate the harmful stimulus, clear away dead cells and debris, and pave the way for tissue repair.
Sign #1: Rubor (Redness), the vascular gateway
The first striking visual sign of acute inflammation is rubor, or redness. Whether you scrape your knee, burn your finger on a hot stove, or develop a bacterial infection in a hair follicle, the affected area almost instantly takes on a pink or deep red hue.
The physiological mechanism: Vasodilation
The redness is caused by a dramatic increase in blood flow to the affected site, a process known as hyperemia. Under normal conditions, the arterioles supplying a tissue maintain a certain degree of tone, regulating the volume of blood passing through the capillary beds. However, when tissue is injured or infected, resident immune cells, specifically mast cells and macrophages, release a barrage of chemical signaling molecules called inflammatory mediators.
Chief among these mediators are:
Histamine: Released rapidly by mast cells, histamine acts directly on the smooth muscle surrounding local blood vessels, causing them to relax and widen.
Prostaglandins: These lipid compounds amplify the vascular response and sensitize nerve endings.
Nitric Oxide (NO): A potent vasodilator produced by endothelial cells lining the blood vessels.
As these chemical signals flood the microcirculation, local arterioles and capillary beds dilate significantly. This widening allows a massive surge of oxygenated, red blood cell-rich blood to rush into the superficial capillaries beneath the skin. Because the blood vessels are engorged and closer to the surface, the tissue turns visibly red.
Clinical Significance
Redness is more than just a cosmetic change; it is the body's way of flashing a high-priority distress signal. By opening the vascular floodgates, the body ensures that an army of white blood cells, platelets, nutrients, and oxygen molecules are rapidly delivered to the exact coordinates where they are needed most. Without this initial rush of blood, the immune system would lack the immediate reinforcements required to contain a localized threat.
Sign #2: Calor (Heat), fueling the cellular furnace
Closely tied to redness is the second cardinal sign: calor, or localized heat. If you touch an inflamed joint or a freshly infected pimple, you will immediately notice that the skin feels noticeably warmer than the surrounding healthy tissue.
The source of thermal energy
The increase in temperature is a direct physical consequence of the first sign, hyperemia. Blood is the body’s thermal regulator, maintaining a core temperature of roughly 98.6°F (37°C). When a massive volume of warm blood is suddenly diverted from the body's core into a localized, superficial capillary bed, it transfers its thermal energy directly to the surrounding skin and subcutaneous tissues.
However, vascular influx is only part of the story. At the microscopic level, inflammation is an intensely energetic metabolic event. As millions of neutrophils and macrophages migrate into the tissue, they ramp up their metabolic activity. These cells consume high amounts of glucose and oxygen to fuel oxidative bursts, a process where they generate reactive oxygen species to destroy invading pathogens. This spike in cellular metabolism releases chemical energy, much of which is dissipated as localized thermal energy.
Why Heat matters
While the warmth can sometimes feel uncomfortable, elevated local temperature plays an active role in fighting off pathogens. Many common bacteria and viruses have strict optimal temperature ranges for replication. A localized rise in temperature can slightly inhibit microbial proliferation, slowing down an infection while simultaneously boosting the enzymatic kinetics and mobility of the body's own immune cells.
Sign #3: Tumor (Swelling), the fluid shield
The third sign, tumor (from the Latin word for swelling or mass, entirely distinct from the medical term for a neoplasm), describes the puffy, distended appearance of inflamed tissue.
The Mechanics of Edema
Swelling is driven by dramatic alterations in vascular permeability. Normally, blood vessel walls act as semi-permeable barriers, keeping blood cells and large proteins inside the circulatory system while allowing water and small nutrients to pass into tissues.
During acute inflammation, inflammatory mediators (especially histamine and bradykinin) cause the endothelial cells that line the capillaries to contract slightly. This contraction creates microscopic gaps between the cells, allowing fluid, proteins, and eventually white blood cells to leak out of the blood vessels and into the interstitial space, the tissue surrounding the cells. This protein-rich fluid accumulation is known as exudate (or edema).
As fluid pours into the tissue spaces, the local hydrostatic pressure rises, causing the tissue to expand and puff outward.
Protective Isolation
While swelling causes physical distortion and tightness, it serves a critical tactical purpose. The influx of fluid creates a localized "moat" around the site of injury or infection. This exudate contains clotting factors like fibrinogen, which strands together to form a meshwork. This meshwork traps pathogens and prevents them from entering the broader lymphatic and circulatory systems, effectively quarantining the threat to a single localized area. The swelling dilutes any toxins produced by bacteria, reducing their immediate destructive capacity on surrounding healthy cells.
Sign #4: Dolor (Pain), the biological alarm system
The final classic sign identified by Celsus is dolor, or pain. While pain is universally disliked, it is perhaps the most critical protective mechanism in human biology. Without pain, we would repeatedly injure our bodies without realizing the damage being done.
How Inflammation Triggers Pain receptors
Pain during inflammation is generated through both mechanical and chemical pathways:
Mechanical Pressure: As fluid accumulates in the tissue (tumor), it creates physical tension. This swelling exerts immense mechanical pressure on local nociceptors, the specialized sensory nerve endings responsible for detecting noxious stimuli.
Chemical Sensitization: Inflammatory mediators directly stimulate and sensitize these nerve fibers. Prostaglandins, bradykinin, serotonin, and potassium ions released from damaged cells lower the activation threshold of nociceptors. This means that even a gentle touch that would normally be painless now triggers intense pain signals, a phenomenon known as hyperalgesia.
Behavioral Modification
The evolutionary purpose of inflammatory pain is clear: behavioral modification. Pain forces rest. When you sprain your ankle or burn your hand, the resulting pain ensures that you stop using that body part, preventing catastrophic secondary injury and allowing the physiological repair machinery uninterrupted time to rebuild the damaged architecture.
The transition from Acute to Chronic Inflammation
It is vital to distinguish between acute inflammation, the short-term, highly regulated, life-saving response characterized by Celsus's four signs, and chronic inflammation.
While acute inflammation resolves successfully once the threat is neutralized and tissue homeostasis is restored, chronic inflammation is a prolonged, dysregulated immune response. In chronic conditions, the rubor, calor, tumor, and dolor of acute inflammation may be subtle or absent, replaced instead by a silent, smoldering immune attack that damages healthy organs over months or years. Understanding the acute cardinal signs provides the foundational knowledge required by modern scientists to tackle chronic inflammatory diseases like atherosclerosis, rheumatoid arthritis, and metabolic syndrome.
To explore further into the science of immunity and pathology:
The fifth element: Loss of function and the evolutionary design
While the historic medical texts formalized by Aulus Cornelius Celsus in the first century A.D. famously outlined only four cardinal manifestations, rubor, calor, tumor, and dolor, later medical pioneers like Galen recognized a critical final consequence that naturally completes the physical picture: functio laesa, or the loss of function.
When combined, these signs are not merely an arbitrary collection of discomforts; they represent a brilliantly coordinated, highly evolved physiological defense strategy. Understanding how these localized symptoms transition into systemic healing provides profound insight into human pathology.
Deconstructing the quartet: Physiological synergy
To fully appreciate the continuation of the inflammatory narrative, one must examine how the four primary signs work in precise synchronization:
Rubor (Redness) and Calor (Heat): Driven by localized vasodilation, arterioles expand to flood the compromised matrix with oxygen-rich blood and vital immune cells. This microvascular hyper-perfusion naturally elevates skin temperature and creates a visible flush.
Tumor (Swelling): Increased capillary permeability permits plasma proteins and fluid to flood the interstitial space (edema). This localized fluid shift creates a hydrostatic pressure barrier that helps isolate pathogens and prevents them from spreading systematically.
Dolor (Pain): Chemical mediators such as bradykinin, prostaglandins, and histamine directly bind to and sensitize local nociceptors (pain receptors). Far from being a flaw, this acute discomfort acts as an evolutionary alarm system, forcing behavioral modification and ensuring the organism protects the damaged site from further trauma.
From Acute response to Chronic implications
While acute inflammation is a life-saving mechanism designed to neutralize foreign invaders and clear cellular debris, the biological narrative changes drastically when the switch fails to turn off.
Acute vs. Chronic pathways
| Characteristic | Acute Inflammation | Chronic Inflammation |
|---|---|---|
| Duration | Days to weeks | Months to years |
| Primary Cells | Neutrophils, macrophages | Lymphocytes, plasma cells, macrophages |
| Primary Triggers | Pathogens, tissue trauma, burns | Persistent toxins, autoimmune triggers, prolonged stress |
| Clinical Outcome | Healing and tissue regeneration | Fibrosis, tissue destruction, scarring |
When the immune system remains locked in a prolonged state of activation, the classic signs, particularly localized heat, swelling, and continuous sub-clinical pain, transform into systemic drivers of long-term pathology. Conditions ranging from cardiovascular disease to metabolic dysfunction often share a common root in dysregulated, low-grade inflammatory pathways.
Clinical implications and modern therapeutics
Modern medicine relies heavily on recognizing these cardinal indicators to differentiate between localized tissue injury, infection, and autoimmune flares. Clinicians look for disproportionate presentations, such as severe pain (dolor) absent of significant trauma, as critical diagnostic clues.
Therapeutic interventions are equally rooted in modulating these pathways:
Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): Target the cyclooxygenase (COX) enzymes to suppress prostaglandin synthesis, thereby dampening pain and localized swelling.
Corticosteroids: Broadly inhibit inflammatory cytokine production, interrupting the cascade at a transcriptional level to manage severe immune overactivity.
Targeted Biologics: Focus specifically on individual signaling molecules, such as Tumor Necrosis Factor-alpha (TNF-α\alphaα), to halt chronic tissue destruction in conditions like rheumatoid arthritis.
The quartet of redness, heat, swelling, and pain serves as an enduring medical blueprint. It reminds us that what feels like an affliction is, at its core, the body's ancient, relentless drive to protect and restore itself.
Understanding Inflammation in the Body
This video provides a helpful visual breakdown of the cellular mechanisms behind the classic signs of inflammation.