Beyond the acute horizon
To understand the dangers of Long COVID is to confront a medical phenomenon that resists simple categorization. It is characterized by an erratic constellation of symptoms, spanning neurological, cardiovascular, immunological, and gastrointestinal domains, that can persist for months or even years after an initial infection that was often mild enough to be managed at home. As global health research deepens, the medical community increasingly views Long COVID not as a single unified pathology, but as an umbrella term for overlapping disease subtypes driven by distinct biological mechanisms. Examining these dangers requires a rigorous look into how a respiratory virus can leave a permanent imprint on the human body, transforming a temporary acute illness into a chronic landscape of vulnerability.
1. The Multi-Systemic architecture of pathology
Unlike targeted chronic conditions that predominantly affect a single organ, Long COVID is defined by its multi-systemic reach. The virus responsible for COVID-19, SARS-CoV-2, utilizes angiotensin-converting enzyme 2 (ACE2) receptors, which are abundantly expressed not only in the respiratory tract, but also in endothelial cells lining blood vessels, the heart, the kidneys, the intestines, and various regions of the brain. This widespread cellular distribution sets the stage for a cascading array of long-term dangers.
Neurological and cognitive devastation: The reality of "brain fog"
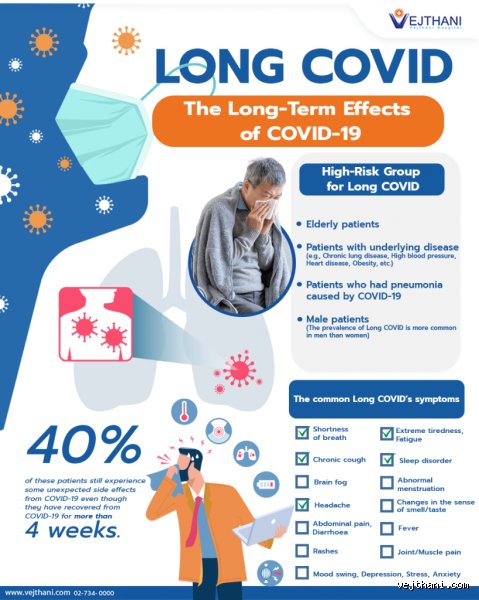
One of the most insidious dimensions of Long COVID involves the central and peripheral nervous systems. Patients frequently report severe cognitive dysfunction, colloquially termed "brain fog," which encompasses profound difficulties with concentration, short-term memory retrieval, word-finding, and executive function. Beyond cognitive slowing, individuals often endure debilitating headaches, sensory neuropathies, and autonomic nervous system dysfunction, most notably Postural Orthostatic Tachycardia Syndrome (POTS). POTS triggers erratic heart rate spikes, severe dizziness, and pre-syncopal episodes merely upon standing, upending a patient’s ability to maintain an upright posture or perform basic daily routines.
Pathophysiological investigations suggest these neurological symptoms stem from chronic, low-grade neuroinflammation. Researchers have identified persistent activation of microglial cells within the brain, potentially incited by initial viral invasion or sustained systemic inflammation. Microvascular injury and tiny blood clots (microthrombi) can impair optimal tissue perfusion and neurotransmission, resulting in a brain starved of optimal cellular maintenance and environmental resilience.
Cardiovascular compromise and subclinical injury
The cardiovascular system bears a heavy burden in the architecture of Long COVID. Even individuals who experienced asymptomatic or mild initial infections can develop long-term cardiac manifestations, including persistent chest pain, palpitations, exercise intolerance, and a sustained resting tachycardia. Autopsy and biomarker studies have revealed structural and functional abnormalities such as myocarditis (inflammation of the heart muscle), myocardial fibrosis, and subclinical reductions in left ventricular contractility.
The danger here is cumulative. When the heart muscle undergoes persistent, low-level inflammatory signaling or microvascular ischemia, its long-term functional reserve diminishes. This leaves patients at an elevated risk for rhythm disturbances (arrhythmias) and progressive cardiac remodeling, turning a routine post-viral phase into a long-term cardiac management challenge.
2. Cellular energy collapse: The core mechanism of Post-Exertional Malaise (PEM)
At the heart of many debilitating Long COVID cases lies a symptom profile that separates it from standard fatigue: Post-Exertional Malaise (PEM). PEM is a profound, disproportionate crash, encompassing physical exhaustion, cognitive collapse, and flu-like aches, that occurs hours or even days after minimal physical, mental, or emotional exertion. For a person with PEM, carrying groceries, reading a book, or engaging in a brief conversation can trigger a severe relapse that confines them to bed for days.
Mitochondrial dysfunction and metabolic arrest
Recent biomedical research has increasingly pointed toward mitochondrial dysfunction as a primary driver of this energy crisis. Mitochondria, recognized as the cellular powerhouses responsible for generating adenosine triphosphate (ATP), appear to be structurally and functionally disrupted following SARS-CoV-2 infection.
Impaired Oxidative Phosphorylation: Cells lose their efficiency in converting nutrients into usable cellular energy.
Oxidative Stress: Damaged mitochondria generate excessive reactive oxygen species (ROS), leading to progressive cellular damage and metabolic fatigue.
Fatty Acid Metabolism Alterations: Plasma profiling of patients with post-acute sequelae reveals systemic disruptions in lipid and fatty acid metabolism, indicating that the body's fundamental metabolic machinery is struggling to sustain basal energy demands.
When cellular power plants fail on a systemic scale, the body enters a perpetual state of energy scarcity. Traditional rehabilitation strategies, such as graded exercise therapy, which encourages pushing through fatigue, have proven not only ineffective for these patients, but genuinely dangerous, often triggering deep, irreversible physiological crashes that deepen disability.
3. Immune dysregulation, viral reservoirs, and autoimmunity
The persistence of symptoms over months and years forces researchers to look closely at the immune system. Why does the body continue to fight an enemy that has technically cleared? Several leading hypotheses explain this sustained state of internal alarm.
The hidden threat of viral reservoirs
Emerging evidence suggests that in a subset of individuals, SARS-CoV-2 or its viral fragments do not entirely vanish from the body. Instead, they take up residence in "viral reservoirs", hidden within tissues such as the gut mucosa, lymph nodes, or the central nervous system. These lingering viral antigens continuously stimulate the immune system, maintaining a smoldering, low-grade inflammatory response that damages surrounding healthy tissue over time.
Autoimmunity and molecular mimicry
Another profound danger of Long COVID is the induction of autoimmunity. During an acute infection, the immune system mounts a massive defense. In some individuals, this process misfires. The antibodies and T-cells generated to neutralize the virus begin recognizing and attacking the body's own structural proteins, a phenomenon known as molecular mimicry. Studies have documented the proliferation of various autoantibodies targeting the body's own receptors, vascular tissues, and regulatory proteins, predisposing patients to new-onset autoimmune conditions that persist long after the acute virus is gone.
4. Socioeconomic and psychological toll
The dangers of Long COVID extend far beyond the physiological boundaries of the human body, cascading into the psychological, professional, and economic spheres of a patient's existence.
The burden of validation and social isolation
Because many routine diagnostic tests (such as standard blood panels, basic chest X-rays, and standard MRIs) frequently return "normal" results for Long COVID patients, individuals often face a harrowing psychological hurdle: medical invalidation. Patients report spending months or years navigating healthcare systems where their debilitating symptoms are met with skepticism or misattributed entirely to anxiety. This systemic gaslighting breeds profound psychological distress, compounding the physical burden with chronic anxiety, depression, and social isolation.
Economic vulnerability and loss of livelihood
The chronicity of the condition translates directly into economic fragility. A significant proportion of individuals suffering from moderate-to-severe Long COVID experience profound disruptions in their work capacity. Many are forced to reduce their hours, transition to remote work, or abandon their careers entirely. The sudden loss of financial independence, combined with escalating healthcare expenditures for specialized management and therapies, places an immense burden on both the individual and household stability, turning a medical diagnosis into an economic crisis.
Summary and ongoing horizons
Long COVID represents a multifaceted medical challenge that tests the limits of contemporary clinical science. By attacking multiple organ systems, disrupting cellular energy production, fostering immune dysregulation, and eroding socioeconomic stability, its dangers are vast and deeply interconnected. Understanding these foundational mechanisms is the first critical step toward destigmatizing the condition, guiding accurate clinical evaluation, and directing research toward targeted therapeutic interventions.
Navigating the multiorgan threat: Neurological, cardiovascular, and metabolic Sequelae
While the initial phase of SARS-CoV-2 infection is widely recognized for its respiratory presentation, the true danger of long COVID lies in its systemic, multiorgan nature. As millions globally have discovered months after clearing the acute virus, the condition is far from a simple lingering cold. Instead, it frequently manifests as a complex matrix of chronic illnesses affecting nearly every major physiological system. Understanding these profound dangers requires looking closely at how the condition disrupts neurological integrity, cardiovascular stability, and metabolic function.
Neurological and cognitive destruction: Beyond "brain fog"
One of the most debilitating dimensions of long COVID involves the central and peripheral nervous systems. Patients frequently report profound cognitive disruption, colloquially and widely termed "brain fog". Far more than mere forgetfulness, this symptom encompasses severely impaired concentration, slowed processing speeds, and acute word-finding difficulties that often render complex employment or academic study impossible.
Recent clinical findings have shed light on the physical roots of these complaints. Advanced neuroimaging and biomarker analyses indicate that persistent neuroinflammation and microglial activation can result in measurable structural changes. Crucially, research highlights potential damage or dysregulation within the brain's dopamine-releasing neuronal pathways. This disruption directly correlates with extreme physical and mental fatigue, a lack of motivation, and persistent motor or executive dysfunction.
Coupled with these central nervous system impacts are peripheral neuropathies, chronic headaches, and severe sleep architecture disturbances. Together, these neurological markers create an exhausting daily landscape where sufferers struggle not only with intellectual execution but with basic autonomous regulation.
Cardiovascular instability and vascular damage
The dangers of long COVID extend deeply into the circulatory system, introducing long-term risks even for individuals who experienced mild initial infections. Among the most prevalent cardiovascular manifestations is Postural Orthostatic Tachycardia Syndrome (POTS) and other forms of dysautonomia. Patients experience erratic heart rate spikes, severe lightheadedness, blood pressure fluctuations, and exercise intolerance simply from moving from a lying to a standing position.
More alarmingly, persistent immune activation and endothelial dysfunction, damage to the delicate inner lining of blood vessels, can promote ongoing microvascular abnormalities and a hypercoagulable state. This creates elevated risks for:
Endothelial inflammation and compromised tissue oxygenation
Persistent chest pain and palpitations
Myocardial and pericardial inflammation (myocarditis/pericarditis)
Long-term structural cardiac strain and heightened vulnerability to ischemic events
Because these vascular changes often bypass standard diagnostic blood panels, patients frequently face a frustrating diagnostic odyssey while harboring genuine, structural cardiovascular vulnerabilities.
Post-Exertional Malaise (PEM) and metabolic crash
A hallmark physiological danger that defines a substantial subset of long COVID cases is Postural Exertional Malaise (PEM). For individuals experiencing PEM, physical, cognitive, or even emotional exertion that would normally be trivial, such as walking down the block or reading a book, triggers a severe, delayed systemic collapse.
This "crash" is rooted in fundamental cellular and metabolic failures, including severe mitochondrial dysfunction and impaired cellular energy production (ATP synthesis). Instead of recovering normally from exertion, patients experience a profound worsening of all symptoms, ranging from flu-like body aches to acute cognitive paralysis, that can last for days or weeks.
Crucially, attempting to "push through" PEM via aggressive physical therapy or graded exercise regimens can permanently worsen a patient's baseline health, driving them deeper into disability. Recognizing PEM as a biological limit rather than a psychological barrier is one of the most critical paradigms in modern clinical management.
Socioeconomic toll and the path forward
The cumulative impact of these overlapping systemic dangers reaches far beyond the individual clinic visit. Long COVID represents a massive public health crisis characterized by lost workforce participation, economic instability, and profound strain on social support networks. Studies show that working-age adults, particularly women and socially vulnerable populations, bear a disproportionate share of this burden, frequently facing years of reduced earning capacity and mounting medical expenses.
Addressing this crisis requires shifting away from dismissal or unproven quick fixes toward structured, multidisciplinary care. Emphasizing radical pacing strategies for energy conservation, deploying targeted symptom management under expert supervision, and funding large-scale biomedical research are essential steps. Only through rigorous scientific inquiry and validated clinical pathways can medicine hope to restore health and futures to the millions living in the shadow of long COVID.