Decoding the Invisible Maze: How Do They Diagnose Long COVID?
The Elusive Target of Modern Medicine
When someone steps into a doctor's office months after clearing a viral infection, still battling a crushing fatigue that defies sleep or a brain fog that turns simple math into an insurmountable hurdle, they are looking for answers. But the thing is, medicine has traditionally relied on definitive tests—a positive culture, a shadow on an X-ray, a specific biomarker spiking in a blood panel—to validate human suffering. When it comes to post-acute sequelae of SARS-CoV-2, commonly known as long COVID, those tidy diagnostic shortcuts largely vanish.
The clinical reality is complex and multifaceted. Major health organizations, including the Centers for Disease Control and Prevention (CDC) and the World Health Organization (WHO), define the condition through sustained clinical criteria rather than a single lab assay. Generally, a diagnosis requires a history of probable or confirmed SARS-CoV-2 infection, with symptoms persisting past the three-month mark and lasting for at least two months without any other identifiable cause.
Why Standard Lab Tests Fall Short
Patients often undergo a battery of routine blood tests, thyroid panels, and basic imaging expecting a clear-cut indicator, only to be told that their results are completely normal. People don't think about this enough: a normal blood test does not mean the pathology is absent; it often just means our current commercial screening tools are looking in the wrong places or measuring the wrong parameters.
Because there is no universal diagnostic blood test or scan for long COVID, clinicians must utilize a process of rigorous exclusion. They need to systematically rule out alternative diagnoses—such as pre-existing autoimmune disorders, unmanaged thyroid disease, primary sleep apnea, or standard post-viral syndromes—that could account for the ongoing decline in health. This diagnostic strategy requires patience and immense validation, as patients navigating a system that frequently questions invisible illnesses face immense emotional and physical tolls.
Navigating the Diagnostic Gray Area
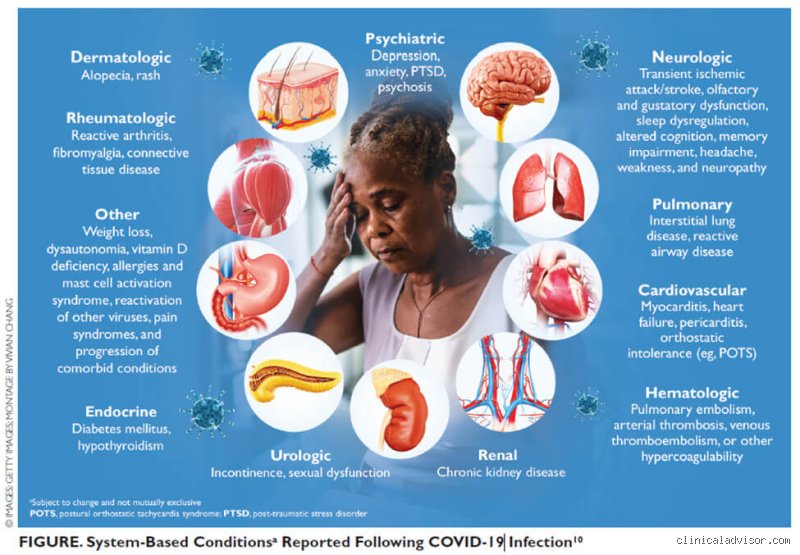
As research progresses, the medical community recognizes that long COVID is not a single monolith, but rather a collection of overlapping sub-phenotypes. Some individuals present primarily with respiratory limitations, others with cardiovascular abnormalities like postural orthostatic tachycardia syndrome (POTS), and still others with profound neurological and cognitive deficits.
Mapping these distinct presentations demands specialized testing, such as orthostatic vitals, cognitive screening modules, or cardiopulmonary exercise testing—though the latter must be handled with extreme care in patients vulnerable to energy crashes. We're far from it when it comes to having a simple finger-prick test that can definitively label the condition on demand, but understanding the existing diagnostic framework is the crucial first step toward effective management and validation.
Navigating the Diagnostic Labyrinth
To arrive at a clear diagnosis of post-COVID conditions, clinicians must balance broad clinical guidelines with the reality of highly variable patient presentations. Because there remains no single, definitive laboratory biomarker or universal blood test to isolate the syndrome, the diagnostic process relies heavily on comprehensive clinical evaluation, symptom mapping, and the systematic ruling out of alternative pathologies (CDC, 2026).
The Diagnostic Framework: Steps in Clinical Practice
When a patient presents with chronic, debilitating symptoms months after an initial infection, a physician's evaluation typically follows a structured path:
Detailed Medical History: Reviewing the timeline of the initial infection—even if it was mild or asymptomatic—and documenting the persistence or delayed onset of symptoms over a minimum three-month window.
Targeted Laboratory Testing: Ordering standard panels (complete blood counts, thyroid panels, inflammatory markers like C-reactive protein, and kidney/liver function tests) to eliminate other common causes of fatigue and pain.
Subtype and Organ-Specific Workups: Deploying specialized diagnostics depending on the dominant presentation, such as tilt-table testing for suspected autonomic dysfunction or postural orthostatic tachycardia syndrome (POTS), and pulmonary function tests for lingering respiratory deficits.
Evaluating Post-Exertional Malaise (PEM): Carefully screening for severe energy crashes following minor physical or cognitive exertion, a hallmark feature that shifts management strategies dramatically.
Note: A positive SARS-CoV-2 viral or antibody test is helpful for documentation, but it is not strictly required to establish a diagnosis, as many early or asymptomatic cases went untested (CDC, 2026).
A Strong Position: Beyond the "Diagnosis of Exclusion" Trap
It is time to move past the outdated notion that long COVID is merely a "diagnosis of exclusion"—a polite medical translation for “all your labs are normal, so your symptoms must be in your head.”
For years, treating chronic post-viral illness as a last resort category has delayed critical care and alienated patients. Clinicians must adopt a strong stance: long COVID is a positive clinical diagnosis driven by characteristic symptom clusters, distinct physiological markers, and well-documented post-viral mechanisms. Recognizing patterns like autonomic instability and immune dysregulation upfront prevents patients from enduring an endless carousel of dismissive consultations.
Admitting Limits and a Touch of Irony
Of course, medical science must humbly admit its current limits: despite immense global research efforts, we still lack a simple, standardized kit that can stamp a definitive "positive" or "negative" on a blood drop for long COVID.
It carries a certain clinical irony that in an era of hyper-advanced artificial intelligence, multi-omics, and precision genomic medicine, one of our most effective diagnostic tools remains a low-tech patient symptom diary and a clinician who is simply willing to listen. Until objective biomarkers catch up to clinical reality, the art of listening to the patient remains our most powerful instrument.