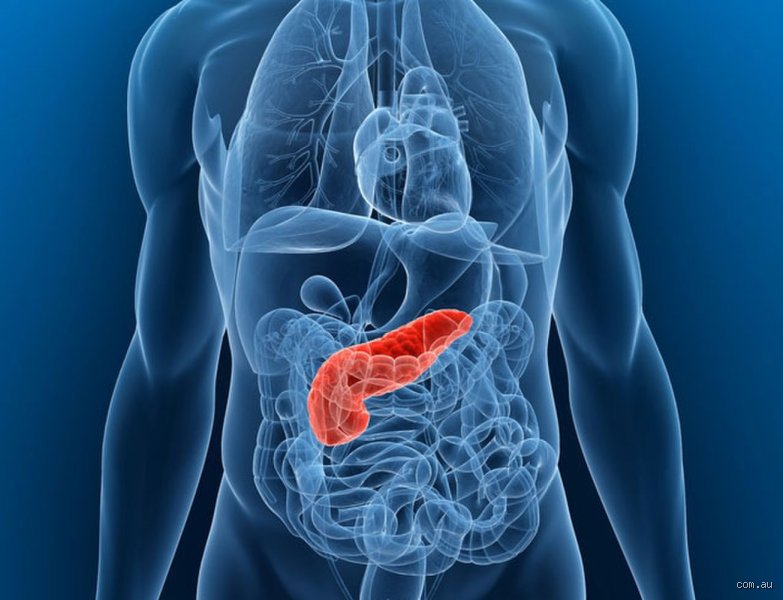
Understanding how the pancreas functions—and recognizing the subtle, often cascading symptoms that arise when it begins to fail—is critical for maintaining long-term wellness. When the pancreas experiences dysfunction, inflammation, or structural degradation, the effects ripple through virtually every major organ system, manifesting in ways that can be both bewildering and debilitating.
The dual role of the pancreas: Endocrine and exocrine mastery
To understand the warning signs of a struggling pancreas, one must first appreciate its dual nature. The pancreas is essentially two organs in one, divided into distinct functional zones that handle entirely different physiological workloads:
1. The endocrine pancreas (hormonal regulation)
Embedded throughout the pancreatic tissue are microscopic clusters of cells known as the Islets of Langerhans. These clusters act as the body's premier chemical thermostat, directly monitoring nutrient levels in the bloodstream and releasing vital hormones straight into circulation.
Insulin: Produced by beta
The cascade of endocrine dysfunction: Blood sugar imbalances
While the exocrine failure results in digestive chaos, a malfunctioning pancreas simultaneously disrupts the body's delicate endocrine system. The Islets of Langerhans, the micro-organs embedded within the pancreatic tissue, are responsible for synthesizing and secreting vital hormones directly into the bloodstream, chief among them insulin and glucagon. When chronic inflammation, tissue destruction, or neoplastic growth compromises these cells, systemic glucose regulation collapses.
The onset of pancreatic-induced diabetes (often clinically classified as Type 3c diabetes or pancreatogenic diabetes) presents distinct diagnostic challenges. Unlike classical Type 1 or Type 2 diabetes, this form involves a concurrent loss of both insulin-secreting beta cells and glucagon-secreting alpha cells.
Key endocrine warning Signs
Volatile Blood Glucose Swings: Patients frequently experience extreme instability, swinging dangerously between hyperglycemia (high blood sugar) and hypoglycemia (low blood sugar), because the body lacks the counter-regulatory glucagon response to rescue crashing glucose levels.
Classic Poly-Symptoms: Unexplained, intense thirst (polydipsia), frequent urination (polyuria, especially nocturia, waking multiple times a night), and persistent, ravenous hunger (polyphagia) coupled paradoxically with weight loss.
Decompensated Fatigue: Cellular starvation due to inefficient glucose uptake leads to an overwhelming, chronic exhaustion that sleep does not resolve.
Obstructive dynamics and systemic red flags: The Signs of pancreatic masses
When a structural lesion, cyst, or malignancy (such as pancreatic ductal adenocarcinoma) obstructs the normal flow through the pancreatic or common bile ducts, an entirely new array of distinct, high-acidity warning signs emerges. Because the head of the pancreas sits adjacent to the biliary tree, even a small obstruction rapidly impacts systemic chemistry.
Critical Red-Flag indicators
Obstructive Jaundice: A painless yellowing of the skin and the sclera (whites of the eyes), caused by a backup of bilirubin when a tumor blocks the common bile duct. This is frequently accompanied by dark, cola-colored urine and unnaturally pale, clay-colored stools.
Pruritus (Severe Itching): Circulating bile salts accumulating in the dermal tissues due to biliary blockage trigger an intractable, deep-seated skin itchiness that resists standard topical treatments.
Migratory Superficial Thrombophlebitis (Trousseau’s Syndrome): A lesser-known but critical indicator where spontaneous blood clots form in superficial veins across different parts of the body, often signaling an underlying hypercoagulable state triggered by pancreatic pathology.
New-Onset Depression or Anxiety: Unexplained shifts in mood, sudden-onset clinical depression, or profound psychological unease have frequently been documented as early neurological manifestations preceding physical tumor diagnosis by several months.
Differential diagnosis and Clinical pathways
Because symptoms like upper abdominal discomfort, bloating, and irregular bowel habits overlap heavily with common gastrointestinal conditions such as irritable bowel syndrome (IBS), gastritis, or gallbladder disease, diagnosing pancreatic dysfunction requires targeted clinical investigation.
[Clinical Presentation]
│
├──> Persistent Epigastric Pain radiating to Back? ──> Order CT / MRI / Lipase
├──> Steatorrhea / Malabsorption Signs? ──> Check Fecal Elastase-1 (FE-1)
├──> Unexplained Jaundice / Weight Loss? ──> Urgent Biliary Imaging / Ultrasound
Physicians typically deploy a multi-tiered approach when pancreatic failure is suspected:
Biochemical and Stool Assays: Checking serum lipase and amylase levels, alongside a fecal elastase-1 (FE-1) test to measure exocrine enzyme output directly from stool.
Advanced Imaging: Utilizing contrast-enhanced cross-sectional imaging (CT or MRI/MRCP) to visualize structural atrophy, calcifications, ductal dilation, or mass lesions.
Endoscopic Ultrasound (EUS): Providing high-resolution visualization of the pancreatic parenchyma and enabling fine-needle tissue acquisition if a neoplasm is suspected.
Recognizing the threshold for intervention
The pancreas may be small, nestled quietly deep behind the stomach, but its dual responsibilities dictate the metabolic rhythm of the entire body. Whether through the agonizing flare-ups of acute inflammation, the quiet, corrosive progression of exocrine failure and malabsorption, or the systemic alarms of structural obstruction, a failing pancreas communicates its distress through signals that demand immediate medical attention.
Early identification of these symptoms alters the clinical trajectory entirely, allowing for prompt enzyme replacement therapies, aggressive metabolic management, or life-saving surgical intervention. Persistent, unexplained shifts in digestive health, glucose stability, or upper abdominal comfort should never be dismissed as routine stress or simple indigestion.