The details
To fully grasp the divergence between osmotic and secretory diarrhea, one must examine the micro-environment of the enterocyte and the biophysics of paracellular versus transcellular transport.
In a healthy human gastrointestinal tract, the mucosa processes roughly 9 liters of fluid daily—comprising dietary intake and endogenous secretions from salivary glands, the stomach, the pancreas, and the biliary tree. The small intestine and colon reabsorb over 99% of this load. Pathophysiologically, diarrhea ensues when this precise equilibrium is compromised.
[Luminal Space] <--- Osmotic Gradient ---> [Enterocyte/Epithelium]
(Accumulation of non-absorbable solutes) (Pulls water passively via tight junctions)
[Luminal Space] <--- Active Secretion ---- [Crypt Cells]
(Driven by active cAMP/cGMP cascades) (Pumps Cl- and HCO3- outward, pulling Na+ and H2O)
At the molecular level, osmotic diarrhea is fundamentally a defect in solute handling. When poorly absorbable, osmotically active molecules (such as magnesium sulfate, lactulose, or unabsorbed carbohydrates like lactose in lactase deficiency) accumulate in the lumen, they create a hypertonic environment. Water is pulled down its concentration gradient across the intestinal mucosa into the lumen to achieve osmotic equilibrium. The epithelial lining itself remains structurally intact and functions normally; it is simply overwhelmed or bypassed by the presence of these trapping solutes.
Conversely, secretory diarrhea represents an active, pathological secretory state driven by cellular signaling pathways. Enterocytes and crypt cells are hijacked or stimulated to oversecrete electrolytes—predominantly chloride (Cl− ext{Cl}^-Cl−) and bicarbonate (HCO3− ext{HCO}_3^-HCO3−), into the intestinal lumen. This active ion transport is typically mediated by intracellular second messengers such as cyclic adenosine monophosphate (cAMP), cyclic guanosine monophosphate (cGMP), or intracellular calcium (Ca2+ ext{Ca}^{2+}Ca2+).
For example, enterotoxigenic bacterial toxins (like cholera toxin) permanently activate adenylate cyclase, driving intracellular cAMP sky-high. This opens the cystic fibrosis transmembrane conductance regulator (CFTR) channels wide, resulting in an unremitting efflux of chloride ions. Sodium (Na+ ext{Na}^+Na+) and water follow passively to maintain electrical and osmotic neutrality, turning the intestinal crypts into an open, high-volume faucet.
Little-known aspect
While medical textbooks cleanly separate these two mechanisms, clinical reality frequently introduces complex overlaps that challenge diagnosticians. A striking example of this gray area is bile acid malabsorption (BAM).
Often classified clinically under chronic secretory diarrhea, BAM actually possesses a subtle, hybrid mechanism. When the terminal ileum is diseased or has been surgically resected, bile acids escape normal reabsorption and spill into the colon. Once in the colon, these unabsorbed bile acids exert a dual effect:
They act as mild osmotic agents, drawing a modest amount of water into the lumen.
Far more importantly, they act as active chemical irritants that stimulate colonic enterocytes to secrete fluid and mucus and accelerate motility via local prostaglandin and cAMP activation.
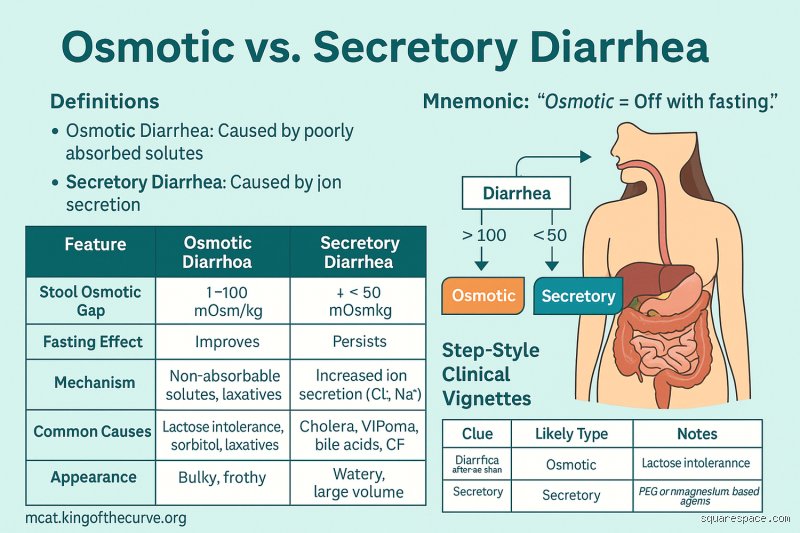
Another under-appreciated nuance involves the behavior of the stool osmotic gap (SOG). Calculated using the formula:
SOG=290−2×([Na+]+[K+]) ext{SOG} = 290 - 2 imes \left([ ext{Na}^+] + [ ext{K}^+] ight)SOG=290−2×([Na+]+[K+])
...the gap helps differentiate the two. An osmotic diarrhea classically features a high osmotic gap (> 100 mOsm/kg ext{> } 100 ext{ mOsm/kg}> 100 mOsm/kg), because the measured stool osmolality is made up of the unmeasured, unabsorbed solutes. A secretory diarrhea features a low osmotic gap (< 50 mOsm/kg ext{< } 50 ext{ mOsm/kg}< 50 mOsm/kg), because the osmolality is almost entirely accounted for by active secreted electrolytes (Na+ ext{Na}^+Na+ and K+ ext{K}^+K+).
However, clinicians can be tricked: if a patient with secretory diarrhea heavily ingests magnesium-containing laxatives or sports drinks concurrently, or if bacterial fermentation of unabsorbed carbs in osmotic diarrhea breaks them down into short-chain fatty acids (which multiply the particle count), the stool osmotic gap can yield intermediate, misleading numbers.
So, what is the answer?
Distinguishing between osmotic and secretory diarrhea requires synthesizing clinical history, chronicity, and biochemical markers. The single most reliable bedside differentiator remains the response to fasting (or a trial of NPO status). Because osmotic diarrhea relies entirely on the presence of exogenous or malabsorbed luminal solutes, withdrawing the offending substance halts the process; the osmotic gradient collapses, and the diarrhea resolves.
Secretory diarrhea, driven by autonomous or receptor-mediated cellular secretion, is entirely indifferent to food intake. The volume remains persistently high, frequently exceeding 1 liter per day, even during a complete fast, putting patients at rapid risk of severe hypokalemia and metabolic acidosis.
| Feature | Osmotic Diarrhea | Secretory Diarrhea |
|---|---|---|
| Primary Mechanism | Unabsorbed luminal solutes draw water in | Active electrolyte (Cl−) secretion by crypt cells |
| Response to Fasting | Resolves or significantly improves | Persists unabated (high volume) |
| Stool Osmotic Gap | High (>100 mOsm/kg) | Low (<50 mOsm/kg) |
| Common Triggers | Lactose intolerance, magnesium antacids, sugar alcohols | Neuroendocrine tumors, bacterial enterotoxins (cholera) |
Final verdict
Understanding the divergence between osmotic and secretory diarrhea transforms a bewildering symptom into a precise physiological map. Osmotic diarrhea is fundamentally a problem of what goes in and stays unabsorbed, a physical consequence of concentration gradients. Secretory diarrhea is a problem of cellular rebellion, an active, energy-consuming process where the gut lining itself turns against the host, pumping out ions and flooding the lumen.
Recognizing these distinct pathways is what allows modern medicine to transition from generalized fluid management to targeted interventions, whether that means eliminating a dietary sugar, utilizing oral rehydration therapy to exploit coupled sodium-glucose transport, or identifying a hidden neuroendocrine tumor.