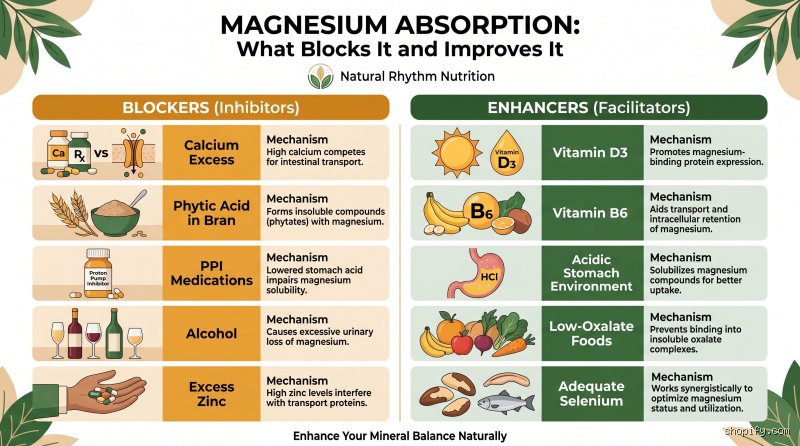
A central driver of this paradox is not merely inadequate dietary intake, but rather the complex physiological and biochemical barriers that impede intestinal absorption. Even individuals consuming a nutrient-dense diet may experience compromised magnesium status due to dietary antagonists, gastrointestinal pathophysiology, mineral competition, and pharmacological interference.
Understanding what blocks the absorption of magnesium requires a granular examination of gastrointestinal physiology, molecular transport mechanisms, and the intricate matrix of dietary chemistry.
1. The physiological landscape of Magnesium absorption
To comprehend how magnesium absorption is blocked, one must first understand the normal route and mechanisms by which the body assimilates the mineral.
Dietary magnesium enters the gastrointestinal tract and is dissolved in gastric secretions, where ionized Mg2+ ext{Mg}^{2+}Mg2+ becomes available for uptake. Absorption occurs across the entire length of the intestine, but the primary sites are the distal small intestine (the ileum) and the proximal colon.
Two distinct pathways facilitate intestinal magnesium transport:
Paracellular Passive Transport: This is a concentration-dependent, non-saturable pathway occurring predominantly in the jejunum and ileum. It relies on tight junctions between enterocytes, regulated by transmembrane proteins known as claudins (specifically claudin-16 and claudin-19). This pathway accounts for the majority of magnesium absorption under normal dietary conditions.
Transcellular Active Transport: Operating primarily in the distal convoluted tubule of the kidney and the distal small intestine/colon, this pathway is saturable and protein-mediated. It utilizes specialized apical ion channels, principally Transient Receptor Potential Melastatin type 6 and 7 (TRPM6 and TRPM7), alongside basolateral extrusion mechanisms like the sodium-magnesium exchanger (SLC41A1).
Any factor that disrupts tight junction integrity, downregulates TRPM6/TRPM7 expression, alters luminal pH, or precipitates ionized magnesium into insoluble complexes will critically impair both paracellular and transcellular absorption.
2. Dietary antagonists: Phytates and oxalates
The most pervasive inhibitors of magnesium absorption are naturally occurring antinutrients found in plant-based foods. While plants such as grains, beans, nuts, seeds, and leafy greens are touted as primary sources of magnesium, their internal chemical defense mechanisms can significantly reduce net mineral bioavailability.
Phytic Acid (Myo-inositol 1,2,3,4,5,6-hexakisphosphate)
Phytate, commonly referred to as phytic acid, is the principal storage form of phosphorus in plant seeds. Because of its highly reactive structure adorned with six negatively charged phosphate groups, phytate acts as a potent chelating agent.
When consumed, phytic acid readily binds to positively charged divalent and trivalent mineral ions, including magnesium (Mg2+ ext{Mg}^{2+}Mg2+), calcium (Ca2+ ext{Ca}^{2+}Ca2+), iron (Fe2+ ext{Fe}^{2+}Fe2+/ ext{Fe}^{3+}),andzinc(), and zinc (),andzinc( ext{Zn}^{2+}$), forming insoluble, mixed-cation complexes known as phytates or phytin.
The Mechanistic Blockade: Once chelated within the gastric and upper intestinal lumen, these mineral-phytate complexes precipitate out of solution at physiological pH. Because insoluble phytate precipitates cannot pass through the brush border membrane or enter paracellular transport channels, the bound magnesium is excreted unabsorbed in the feces.
Mitigation Factors: Traditional culinary preparation methods, such as prolonged soaking, sprouting, lactic acid fermentation (e.g., sourdough leavening), and roasting, activate endogenous plant enzymes called phytases. These enzymes hydrolyze the ester bonds of phytic acid, breaking down the hexakisphosphate structure into lower inositol phosphates (such as inositol triphosphate and tetraphosphate), which possess vastly diminished mineral-binding capacities. Unprocessed, high-phytate diets lacking these preparatory steps represent a major dietary block to magnesium assimilation.
Oxalic Acid (Oxalates)
Oxalates are organic acids found in high concentrations in spinach, Swiss chard, rhubarb, beet greens, cocoa, and certain nuts. Similar to phytates, oxalic acid features carboxyl groups that readily bind free divalent cations, forming stable, insoluble salts such as magnesium oxalate and calcium oxalate.
Precipitation Kinetics: Unlike phytates, which can sometimes be partially degraded by microbial phytase activity in the colon, oxalates are highly stable compounds. When magnesium encounters oxalic acid in the digestive tract, it forms a tight chelate that resists enzymatic breakdown.
Systemic vs. Luminal Impact: The formation of magnesium and calcium oxalates not only prevents the local intestinal absorption of magnesium but also plays a central role in renal pathophysiology, where excess unabsorbed oxalate complexes contribute directly to nephrolithiasis (kidney stone formation). Consequently, consuming raw, high-oxalate greens without adequate cooking or calcium pairing severely limits magnesium bioavailability from those sources.
3. Mineral-Mineral competitions and antagonistic interactions
Because intestinal transport mechanisms, particularly active transport channels and paracellular electrostatic selectivity filters, are shared among various divalent cations, a classic competitive inhibition dynamic occurs when multiple minerals vie for absorption sites.
Calcium-Magnesium Antagonism
Calcium and magnesium share similar physicochemical properties, atomic radii, and hydration energies. Consequently, they compete directly for identical transport pathways in the intestinal mucosa.
The Competitive Threshold: When the molar ratio of calcium to magnesium in a meal or supplement exceeds optimal thresholds (typically cited in clinical literature as greater than 2:1 or 2.5:1), high concentrations of luminal calcium saturate the paracellular tight junction channels and active transport carriers.
Clinical Implications: Excessive calcium supplementation, frequently prescribed for bone mineral density management, can inadvertently induce secondary magnesium malabsorption. The influx of calcium ions outcompetes magnesium for TRPM-family channel entry and claudin-mediated paracellular flux, shifting the net balance in favor of calcium retention while suppressing magnesium uptake.
High-Dose trace element interactions
Beyond calcium, heavy supplementation or high dietary concentrations of other transition metals, such as non-heme iron (Fe2+ ext{Fe}^{2+}Fe2+), zinc (Zn2+ ext{Zn}^{2+}Zn2+), and copper (Cu2+ ext{Cu}^{2+}Cu2+), can exert inhibitory effects on magnesium absorption.
While iron and zinc primarily utilize specialized apical carriers like divalent metal transporter 1 (DMT1) and ZIP4, respectively, supraphysiological boluses of these minerals administered simultaneously with magnesium can overwhelm mucosal absorptive capacity, alter electrostatic gradients across the brush border, and competitively suppress paracellular solvent drag.
4. Dietary Fiber: Dual roles and complex dynamics
The relationship between dietary fiber and magnesium absorption is nuanced, characterized by a delicate balance between chemical inhibition and physiological enhancement.
Insoluble vs. Soluble Fiber: Insoluble fibers (such as cellulose and hemicellulose found in wheat bran and coarse cereal husks) frequently contain high concentrations of associated phytic acid and lignin matrices. Lignin and crude fiber particles can physically entrap magnesium ions or provide active binding sites on their polymeric surfaces, hindering diffusion.
Fermentable Fibers as Enhancers: Conversely, soluble, fermentable fibers, such as pectin, inulin, and fructooligosaccharides (FOS), exhibit a radically different effect. When these prebiotic fibers reach the large intestine, resident colonic microbiota ferment them into short-chain fatty acids (SCFAs), particularly acetate, propionate, and butyrate.
This microbial fermentation lowers the luminal pH of the colon.
The resulting acidic environment increases the solubility and ionization of remaining magnesium, facilitating passive absorption across the colonic mucosa and upregulating electrogenic transport pathways.
Thus, while crude, unfermented insoluble fiber rich in phytates acts as a net block, fermentable soluble fiber actively enhances magnesium salvage in the lower GI tract.
5. Gastric acid status and Luminal ph dependencies
The chemical state of ingested magnesium dictates its solubility. Magnesium must be dissociated from its carrier compound and ionized into Mg2+ ext{Mg}^{2+}Mg2+ within the stomach and proximal duodenum to pass through the intestinal epithelium. This ionization process is fundamentally dependent upon adequate gastric acid (HCl ext{HCl}HCl) secretion.
Hypochlorhydria and Achlorhydria: Conditions characterized by low gastric acid output, whether induced by physiological aging (atrophic gastritis), autoimmune gastritis, or chronic pharmacological suppression, drastically elevate luminal pH.
The Solubility Barrier: At an elevated pH (neutral or weakly acidic), magnesium salts, particularly inorganic forms like magnesium oxide or magnesium carbonate, exhibit poor solubility. They remain in un-ionized, crystalline complexes that cannot interact effectively with mucosal transport proteins.
Pharmacological Blockade (PPIs): Proton Pump Inhibitors (PPIs) such as omeprazole, lansoprazole, and pantoprazole suppress gastric H+/K+ ext{H}^+/ ext{K}^+H+/K+-ATPase pumps. Chronic, long-term PPI use is clinically recognized to induce profound hypomagnesemia by establishing a persistent alkaline gastric microenvironment, shutting down the essential initial phase of magnesium liberation and downregulating intestinal enterocyte transport proteins.
6. Gastrointestinal pathologies disrupting absorption
Structural and functional integrity of the intestinal mucosa is an absolute prerequisite for mineral assimilation. When chronic inflammatory, autoimmune, or dysbiotic pathologies compromise the intestinal epithelium, magnesium absorption drops precipitously.
Celiac Disease and Gluten-Induced Enteropathy: Damage to the duodenal and jejunal mucosa results in villous atrophy, blunting the microvillar surface area available for nutrient exchange and destroying the enterocytes where TRPM6/TRPM7 channels are densely expressed.
Inflammatory Bowel Disease (Crohn’s Disease and Ulcerative Colitis): Active inflammation in the terminal ileum, the primary anatomic site for passive paracellular magnesium absorption, directly impairs claudin protein expression and tight junction sealing, leading to severe malabsorptive wasting.
Small Intestinal Bacterial Overgrowth (SIBO): Microbial dysbiosis within the proximal small intestine results in premature nutrient consumption by bacteria, intraluminal inflammation, and altered bile acid metabolism, all of which interfere with optimal mineral uptake kinetics.
7. Pharmacological and endocrine interferences
Beyond gastric acid suppressants, a wide array of prescription medications and systemic hormonal imbalances block magnesium homeostasis:
Loop and Thiazide Diuretics: Medications such as furosemide and hydrochlorothiazide inhibit sodium and chloride reabsorption in the renal tubules, which secondarily triggers profound renal magnesium wasting, often compounding systemic depletion even if intestinal absorption remains baseline.
Hormonal Regulators: Parathyroid hormone (PTH) and active vitamin D (1,25-dihydroxycholecalciferol ext{1,25-dihydroxycholecalciferol}1,25-dihydroxycholecalciferol) modulate systemic mineral homeostasis. While vitamin D deficiency indirectly impairs intestinal magnesium absorption (as TRPM6 expression is partly vitamin D-responsive), severe imbalances in thyroid hormones (hyperthyroidism) accelerate gastrointestinal transit times, drastically shortening the temporal window available for passive and active mineral absorption across the enterocyte membrane.
Conclusion of part I
As this comprehensive biochemical and physiological analysis demonstrates, the human body's ability to absorb magnesium is constantly challenged by competing minerals, chemical chelators like phytates and oxalates, altered gastric pH, and structural or pharmacological disruptions within the gastrointestinal tract.
Recognizing these multifaceted roadblocks is the first step toward optimizing magnesium status, guiding clinical intervention, and informing dietary choices to maximize true cellular bioavailability.
Beyond dietary interferences: Gastrointestinal barriers to Magnesium bioavailability
While the chemical binders present in food, such as phytates, oxalates, and tannins, represent the frontline obstacles to magnesium intake, the physiological state of the gastrointestinal tract itself plays an equally decisive role. Even a diet meticulously designed to minimize chelating agents will fail to yield optimal systemic magnesium levels if the internal environment of the gut is compromised.
The primary site of magnesium absorption is the small intestine, specifically the ileum and jejunum, though a secondary, passive absorption process also occurs in the colon. Absorption happens via two distinct pathways: passive paracellular transport (movement between cells, driven by electrochemical gradients) and active transcellular transport (movement through cells, mediated by specific carrier proteins like Transient Receptor Potential Melastatin type 6 and 7, commonly known as TRPM6 and TRPM7).
Any condition that alters the structural integrity of the intestinal mucosa, disrupts the electrochemical gradient, or downregulates these specialized carrier proteins will directly impede magnesium uptake, regardless of how much of the mineral is ingested.
Hypochlorhydria and low stomach acid
The journey of magnesium begins in the stomach, where gastric acid (hydrochloric acid, or HCl) is required to ionize mineral compounds, releasing free magnesium ions from the complex food matrix or supplement binders. Individuals suffering from hypochlorhydria (low stomach acid) or achlorhydria (complete absence of stomach acid) experience a significant bottleneck at this initial stage.
Without an adequately acidic environment, many inorganic magnesium forms remain bound and insoluble, rendering them incapable of being absorbed further down the digestive tract. This is a primary reason why aging, chronic atrophic gastritis, and the long-term use of acid-suppressing medications (such as proton pump inhibitors or H2-receptor antagonists) are heavily correlated with clinical and subclinical magnesium deficiency.
Intestinal inflammation and dysbiosis
The health of the gut microbiome and the integrity of the intestinal lining are profoundly intertwined with mineral absorption. Chronic inflammatory conditions of the gut, such as Crohn’s disease, ulcerative colitis, celiac disease, and even low-grade, diet-induced intestinal inflammation, damage the microvilli of the small intestine. This mucosal damage drastically reduces the surface area available for absorption and impairs the expression of TRPM6/TRPM7 transport channels.
An imbalanced gut microbiome (dysbiosis) can negatively influence mineral status. Beneficial bacteria ferment dietary fibers into short-chain fatty acids (SCFAs), which lower the pH of the colon. A more acidic colonic environment enhances the solubility of minerals like magnesium, facilitating passive colonic absorption. When dysbiosis dominates, SCFA production drops, intestinal pH rises, and magnesium retention declines.
Pharmaceutical and medical obstructions
In addition to intrinsic gastrointestinal factors, numerous common pharmaceutical interventions act as direct antagonists to magnesium homeostasis, either by blocking its absorption, accelerating its excretion, or altering its distribution within the body.
1. Proton Pump Inhibitors (PPIs)
As touched upon regarding stomach acid, medications like omeprazole, lansoprazole, and pantoprazole suppress gastric acid secretion. Over time, prolonged PPI use can induce severe hypomagnesemia (low blood magnesium levels). The FDA has issued explicit safety warnings regarding long-term PPI use and magnesium depletion, noting that the deficiency can persist even with oral supplementation unless the underlying acid suppression is addressed or specialized, acid-independent supplement forms are utilized.
2. Diuretics
Loop diuretics (such as furosemide) and thiazide diuretics (such as hydrochlorothiazide), commonly prescribed for hypertension and heart failure, work by forcing the kidneys to excrete excess sodium and water. Unfortunately, these medications are non-selective in their action on the renal tubules, frequently dragging magnesium and potassium along with the sodium into the urine. This creates a state of excessive renal wasting that dietary intake alone struggles to outpace.
3. Certain Antibiotics
Classes of antibiotics such as aminoglycosides and fluoroquinolones have been shown to induce renal magnesium wasting and inhibit cellular uptake mechanisms. Prolonged or frequent courses of these antibiotics can rapidly deplete total-body magnesium reserves.
Lifestyle triggers: Stress, exercise, and dietary excesses
Dietary composition and medical status aside, daily lifestyle habits exert a powerful modulating effect on how much magnesium your body retains or burns through.
Chronic psychological and physiological Stress
The human stress response, mediated by the hypothalamic-pituitary-adrenal (HPA) axis, has a notoriously high metabolic cost regarding minerals. When exposed to chronic psychological stress, physical trauma, or intense athletic overtraining, the body releases surges of catecholamines (adrenaline and noradrenaline) and cortisol.
This hormonal cascade triggers an intracellular shift of magnesium, moving it out of the cells and into the bloodstream, where it is subsequently filtered and excreted by the kidneys. This phenomenon, often termed "stress-induced magnesium wasting," creates a vicious cycle: stress depletes magnesium, and low magnesium heightens the nervous system's reactivity to future stressors, making the individual even more vulnerable to anxiety and burnout.
High-Intensity endurance training and heavy sweating
For athletes and active individuals, sweat is a notable route of magnesium loss. While the concentration of magnesium in sweat is relatively low compared to sodium or potassium, prolonged endurance exercise, such as marathons, ultra-running, or intense heat-acclimatized training, results in cumulative losses that can compromise performance and recovery. If fluid and electrolyte replacement strategies focus solely on sodium and water while ignoring intracellular minerals, a functional deficiency can develop over time.
Excessive consumption of refined sugars and caffeine
The metabolic processing of refined carbohydrates and simple sugars places a heavy demand on micronutrients. The body requires magnesium as a cofactor for enzymes involved in glycolysis (the breakdown of glucose for energy). Consequently, a diet high in processed sugars accelerates the utilization and subsequent renal excretion of magnesium.
Caffeine, on the other hand, acts as a mild diuretic and can briefly increase the urinary excretion of several minerals, including magnesium and calcium. While an occasional cup of coffee poses little risk to a well-nourished individual, heavy, all-day caffeine consumption combined with a nutrient-poor diet can significantly tilt the balance toward depletion.
Strategic countermeasures: Optimizing Magnesium status
Understanding what blocks magnesium absorption naturally points the way toward effective countermeasures. Overcoming these physiological and dietary barriers requires a multi-pronged approach tailored to modern nutritional science:
Implement Food Preparation Techniques: Reduce phytic acid content in grains, legumes, nuts, and seeds by utilizing traditional preparation methods such as soaking, sprouting, fermenting, or boiling. These processes activate endogenous phytase enzymes that break down phytic acid before it reaches your digestive tract.
Support Gastric Function: If low stomach acid is a suspected bottleneck, supporting digestion through apple cider vinegar, betaine HCl (under professional guidance), or bitter herbs can enhance the ionization of minerals in the upper GI tract.
Separate Mineral Supplements: Avoid taking calcium supplements, high-dose iron, or zinc concurrently with high-dose magnesium. Staggering mineral intake by a few hours prevents competitive saturation of shared intestinal transport pathways.
Choose Bioavailable Supplement Forms: If relying on supplements to bridge a nutritional gap, opt for forms with superior absorption profiles and minimal gastrointestinal side effects, such as magnesium glycinate, malate, or threonate, rather than poorly absorbed inorganic oxides.
Manage Stress and Recovery: Mitigate chronic HPA-axis activation through adequate sleep, mindfulness practices, and balanced training loads to minimize stress-induced renal wasting.
By systematically identifying and neutralizing the dietary chelators, digestive impediments, pharmacological roadblocks, and lifestyle stressors that block magnesium absorption, you can transform your nutritional intake from a game of chance into a reliable foundation for long-term health and cellular vitality.