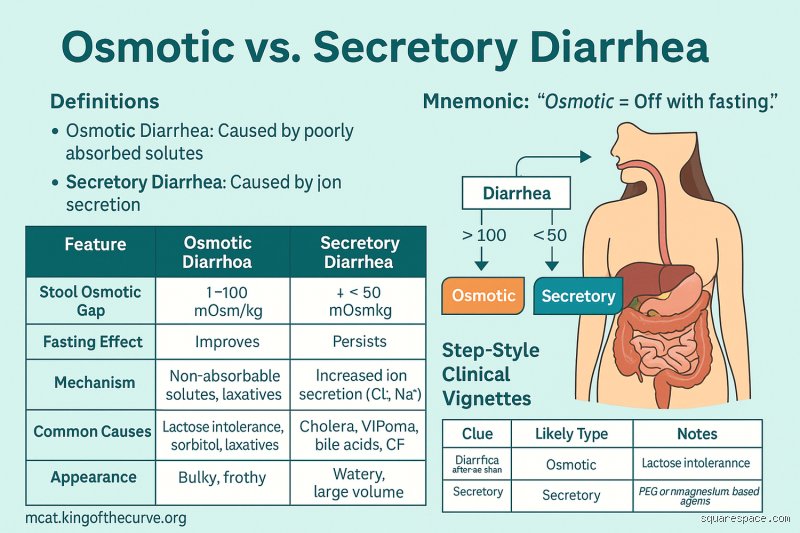
Introduction to Diarrheal Pathophysiology
Gastrointestinal disorders represent some of the most common encounters in clinical practice, yet deciphering their root causes requires a rigorous understanding of intestinal physiology. At its core, chronic or persistent diarrhea is rarely a random symptom; it is a manifestation of disrupted water and electrolyte homeostasis within the gastrointestinal tract. Under normal physiological conditions, the human gut processes roughly 9 liters of fluid daily—composed of dietary intake and endogenous secretions from salivary glands, the stomach, pancreas, and biliary system.
The small intestine and colon reabsorb over 99% of this volume, leaving less than 200 milliliters to be excreted in the stool daily. When this finely tuned balance of secretion and absorption fails, fluid volume overwhelms the colon’s absorptive capacity, resulting in diarrhea.
Among the myriad classifications of diarrhea, distinguishing between osmotic and secretory mechanisms remains a cornerstone of gastroenterological evaluation. While both types result in voluminous, watery stools, their underlying driving forces, biochemical profiles, and responses to clinical interventions are fundamentally distinct. Misdiagnosing one for the other can lead to inappropriate and potentially harmful diagnostic workups, delayed treatment, and persistent morbidity for the patient.
This first part of our comprehensive expert guide explores the foundational pathophysiology, cellular mechanisms, and initial clinical presentation required to differentiate osmotic from secretory diarrhea with clinical precision.
Part 1: Deep Dive into Osmotic Diarrhea
1.1 Pathophysiological Principles
Osmotic diarrhea occurs when poorly absorbable, osmotically active solutes are ingested or accumulate within the lumen of the small intestine. These molecules—whether unabsorbed carbohydrates, divalent ions, or synthetic sugar alcohols—create an osmotic gradient across the intestinal mucosa.
Because the intestinal mucosa acts as a semipermeable membrane, water is drawn out of the extracellular fluid compartments (plasma and interstitial spaces) and pulled down its concentration gradient into the gut lumen to equalize osmolalities.
The primary hallmark of osmotic diarrhea is its direct dependence on oral intake. When the patient fasts or ceases ingestion of the offending osmotic agent, the osmotic gradient collapses, fluid movement halts, and the diarrhea promptly resolves. This characteristic feature provides the clinician with an immediate, non-invasive diagnostic clue.
1.2 Common Etiologies and Clinical Triggers
Identifying osmotic diarrhea requires a thorough dietary and pharmacological history. The etiologies generally fall into several distinct categories:
Carbohydrate Malabsorption: The most prevalent cause of osmotic diarrhea in clinical practice is carbohydrate intolerance, most notably lactose intolerance. A deficiency in mucosal lactase prevents the hydrolysis of lactose into glucose and galactose, leaving the disaccharide unabsorbed in the lumen. Other examples include fructose malabsorption and sorbitol or mannitol ingestion, which are frequently found in sugar-free gums, candies, and dietetic products.
Iatrogenic and Accidental Ingestion of Laxatives: Patients—often intentionally in cases of eating disorders or factitious diarrhea, or accidentally through occupational exposure—frequently consume osmotic laxatives. These include magnesium-containing compounds (such as milk of magnesia or antacids), sodium phosphate, and polyethylene glycol.
Generalized Malabsorption Syndromes: Conditions that compromise the mucosal surface area or enzymatic machinery of the small intestine, such as celiac disease, pancreatic exocrine insufficiency, or surgical short-bowel syndrome, can leave complex nutrients unabsorbed, secondarily creating an osmotic load.
1.3 Biochemical Characteristics and the Stool Osmotic Gap
The biochemical signature of osmotic diarrhea is distinct and measurable through stool chemistry. When analyzing stool electrolytes, clinicians rely heavily on the stool osmotic gap (SOG).
The osmolality of stool is remarkably stable, typically matching that of plasma (roughly 290 mOsm/kg). This osmolality is primarily maintained by active electrolytes ( and ) and their accompanying anions. The formula for the stool osmotic gap is expressed as:
In osmotic diarrhea, because the unabsorbed solutes (like unabsorbed sugars or magnesium) account for a significant portion of the total luminal osmolality, the measured electrolytes contribute proportionally less. Consequently, the calculated stool osmotic gap is high, typically exceeding 100 mOsm/kg (often ranging from 125 to 250 mOsm/kg).
Furthermore, because organic acids (such as short-chain fatty acids produced when colonic bacteria ferment unabsorbed carbohydrates) accumulate, the stool pH frequently drops below 6.0.
Part 2: Deep Dive into Secretory Diarrhea
2.1 Pathophysiological Principles
In stark contrast to osmotic diarrhea, secretory diarrhea is driven by active, pathological ion transport across the enterocytes and colonocytes. Instead of a passive gradient pulling water into the lumen, enterocytes undergo a biochemical shift that stimulates active secretion of chloride and bicarbonate ions into the crypts, while simultaneously inhibiting the coupled absorption of sodium and chloride via the neutral sodium-chloride cotransporter system.
This massive efflux of electrolytes into the intestinal lumen creates a secondary osmotic gradient that pulls water along with it. Because this process is driven by intrinsic cellular signaling pathways, hormonal stimuli, or neuroendocrine peptides rather than unabsorbed luminal contents, secretory diarrhea persists even during a 24- to 48-hour fast. The patient continues to produce large volumes of watery stool regardless of nutritional intake, placing them at severe risk of rapid dehydration and electrolyte depletion.
2.2 Common Etiologies and Clinical Triggers
Secretory diarrheas are often more complex and potentially systemic than osmotic diarrheas. They are broadly categorized into infectious, hormonal, and structural etiologies:
Enterotoxigenic Infectious Agents: The classic archetype of secretory diarrhea is cholera, caused by Vibrio cholerae. The cholera toxin permanently activates adenylate cyclase, leading to an intracellular surge of cyclic AMP (cAMP), which opens cystic fibrosis transmembrane conductance regulator (CFTR) channels and forces massive chloride and water secretion. Other pathogens, such as enterotoxigenic Escherichia coli (ETEC), Salmonella, Shigella, and viral agents like Rotavirus, utilize similar enterotoxic or cytotoxic pathways.
Endocrine and Neuroendocrine Tumors: Several rare systemic tumors secrete humoral peptides that relentlessly stimulate intestinal crypt cells. Examples include carcinoid syndrome (serotonin and tachykinins), gastrinomas (Zollinger-Ellison syndrome, where gastric acid hypersecretion overwhelms pancreatic and intestinal buffering capacity), VIPomas (Verner-Morrison syndrome, characterized by vasoactive intestinal peptide hypersecretion causing watery diarrhea, hypokalemia, and achlorhydria—WDHA syndrome), and medullary thyroid carcinoma (calcitonin and prostaglandins).
Bile Acid Malabsorption: When terminal ileal disease or resection prevents the normal reabsorption of bile acids, these compounds spill into the colon. Once in the colon, they stimulate mucosal cAMP production and mucosal secretion, resulting in a distinct subtype known as bile acid diarrhea (Type 1 or Type 2).
Microscopic Colitises and Drugs: Certain medications (such as NSAIDs, chemotherapeutic agents, and microscopic colitis variants like collagenous or lymphocytic colitis) can induce low-grade mucosal inflammation that shifts the absorptive-secretory balance toward active secretion.
2.3 Biochemical Characteristics and the Stool Osmotic Gap
The electrolyte profile of secretory diarrhea reflects its active transport mechanisms. Because the diarrhea is driven by the active secretion of electrolytes, the measured sodium and potassium concentrations in the stool account for nearly all of the luminal osmolality.
Applying the same stool osmotic gap formula:
In secretory diarrhea, the stool osmotic gap is low, typically less than 50 mOsm/kg (often under 30 mOsm/kg). The stool osmolality is almost entirely accounted for by active electrolytes, meaning there are virtually no hidden, osmotically active unmeasured molecules. Stool pH is typically neutral or alkaline (greater than 6.0), and the daily stool volume is frequently massive, often exceeding 1 liter per day and persisting unabated during fasting conditions.
Comparative Summary Matrix
To synthesize the clinical and laboratory features discussed in this first part, the table below outlines the core diagnostic parameters distinguishing the two mechanisms:
This concludes the first part of our expert guide on differentiating osmotic from secretory diarrhea. In the subsequent sections, we will explore advanced diagnostic algorithms, specific provocative testing protocols, and targeted medical management strategies.
Pathophysiological Divergence: The Diagnostic Crossroads
Moving beyond the initial presentation and baseline classification, the clinician must pivot toward a rigorous mechanistic breakdown. The fundamental division between osmotic and secretory diarrhea lies in the integrity and function of the enterocyte brush border and the underlying transport proteins.
In osmotic diarrhea, the driving force is purely thermodynamic and solute-dependent. When non-absorbable, water-soluble molecules are ingested or fail to hydrolyze within the lumen, they create an effective osmotic gradient. Because the tight junctions of the small intestine remain relatively water-permeable in certain segments, water is drawn out of the extracellular fluid and enterocytes into the intestinal lumen to equilibrate the concentration. This means that the total volume of stool water is directly proportional to the osmotic load of the unabsorbed solute. Clinically, this gives rise to a cardinal feature: fasting cessation. When the patient stops oral intake of the offending substance, the osmotic gradient collapses, stool volume drops precipitously, and the condition resolves.
Conversely, secretory diarrhea operates independently of luminal osmolality gradients. Here, active ion transport mechanisms across the enterocyte or colonocyte membrane are dysregulated. Crypt cells go into overdrive, actively pumping chloride ions () and bicarbonate into the lumen via cAMP- or cGMP-mediated pathways (such as through cystic fibrosis transmembrane conductance regulator [CFTR] activation). Sodium () and water follow passively to maintain electrochemical and osmotic neutrality. Because the driving mechanism is active, continuous cellular secretion, fasting has virtually no impact on stool output. The gut continues to produce high volumes of isotonic fluid regardless of whether the patient is eating.
Diagnostic Workup: Step-by-Step Clinical Approach
Navigating the differential diagnosis requires a methodical, step-by-step investigative protocol. Below is a structured framework utilized in advanced gastroenterology practice to pinpoint the exact etiology.
1. The 48-Hour Fasting Trial
When hospitalized patients present with chronic, unexplained large-volume diarrhea, placing the patient on a medically supervised fast is often the most definitive initial discriminator.
Execution: All oral nutrition is withheld, and hydration is maintained exclusively via intravenous fluids. Stool output is meticulously collected and quantified every 24 hours.
Interpretation: If stool output plummets to baseline normal levels within 24 to 48 hours, the diagnosis heavily points toward an osmotic process, verifying that an exogenous, unabsorbed substrate was driving the fluid loss. If the stool output remains persistently elevated above 500 to 1,000 mL per day despite complete fasting, a secretory or structural malabsorptive etiology is confirmed.
2. Calculating the Fecal Osmotic Gap
The fecal osmotic gap (FOG) is a classic calculation designed to estimate the contribution of unmeasured, osmotically active solutes (such as unabsorbed carbohydrates or laxatives) to total stool osmolality.
The Formula:
(Note: Measured stool osmolality should ideally be measured directly via freezing-point depression rather than calculated estimation, as stored stool samples rapidly undergo bacterial fermentation, splitting carbohydrates into short-chain fatty acids and artificially inflating the measured osmolality).
Analytical Thresholds:
An osmotic gap greater than 50 mosm/kg (often reaching 100 to 150 mosm/kg) confirms osmotic diarrhea. The remaining osmolality is accounted for by unmeasured molecules like magnesium, sulfate, polyethylene glycol, or carbohydrates.
An osmotic gap less than 50 mosm/kg (often near zero) points directly to secretory diarrhea. This indicates that the stool electrolytes ( and ) account for virtually the entire osmolality of the fluid, reflecting active, isotonic electrolyte secretion by the crypt cells.
3. Advanced Laboratory Testing and Biomarkers
Once the broad category is secured, specific secondary tests refine the localization:
For Osmotic Suspicions: Check for stool magnesium levels (to rule out surreptitious laxative abuse with magnesium citrate, hydroxide, or sulfate), breath hydrogen tests for carbohydrate intolerances (lactose, fructose), and fecal sugar chromatography.
For Secretory Suspicions: Screen for neuroendocrine tumor markers if the diarrhea is chronic, watery, and voluminous (e.g., plasma vasoactive intestinal peptide [VIP], serum gastrin, calcitonin, and urinary 5-hydroxyindoleacetic acid [5-HIAA] for carcinoid syndrome). Furthermore, evaluate for microscopic colitis via lower endoscopy with biopsies, and check serum immunoglobulins or specific stool elastase if exocrine pancreatic insufficiency or immunodeficiency is suspected.
Management Strategies and Therapeutic Interventions
Differentiating between these two forms dictates divergent treatment paradigms. Misdiagnosing a secretory process as a dietary intolerance can delay life-saving interventions, while failing to recognize an osmotic trigger exposes patients to unnecessary, invasive diagnostic testing.
Clinical Pearl: Always maintain a high index of suspicion for factitious diarrhea or eating disorder behaviors in patients with unexplained osmotic diarrhea and high stool magnesium or laxative screens, especially among healthcare workers or individuals with a history of complex medical presentations.
Management of Osmotic Diarrhea
Dietary Elimination: Once the specific unabsorbed solute is identified—whether through a detailed dietary history or breath testing—the primary intervention is removal. For lactose intolerance, implement a lactose-restricted diet or supplement with exogenous lactase enzymes. For sugar alcohol sensitivity (sorbitol, mannitol, xylitol found in sugar-free gums and candies), eliminate artificial sweeteners.
Laxative Cessation: In cases of inadvertent or intentional surreptitious laxative abuse, psychological support alongside cessation of the offending agent resolves the condition completely.
Enzyme Replacement Therapy: For conditions involving pancreatic exocrine insufficiency, administer targeted pancreatic enzyme replacement therapy (PERT) with meals to ensure complete macromolecule hydrolysis.
Management of Secretory Diarrhea
Treating the Underlying Cause: Because secretory diarrhea stems from active pathological drivers, therapy must target the root cause. This includes resecting hormone-secreting neuroendocrine tumors (e.g., VIPomas, gastrinomas), initiating targeted anti-inflammatory regimens for inflammatory bowel diseases, or treating infectious agents where applicable.
Antisecretory Agents: Somatostatin analogues (such as octreotide) are highly effective in managing refractory secretory diarrheas, particularly those driven by neuroendocrine tumors or chemotherapy-induced enteritis, by inhibiting active intestinal peptide secretion.
Symptomatic Control: Loperamide or diphenoxylate/atropine can slow intestinal transit time, providing time for maximal residual absorption, though they must be used cautiously in acute inflammatory or infectious secretory states to avoid toxic megacolon.
Aggressive Volume and Electrolyte Resuscitation: Due to the massive, ongoing loss of isotonic fluids and electrolytes, aggressive oral rehydration therapy (ORT) containing precise ratios of sodium and glucose—utilizing the sodium-glucose cotransporter-1 (SGLT-1) pathway which remains functional in many secretory states—is critical to prevent hypovolemic shock and acute kidney injury.
Conclusion
Mastering the differentiation between osmotic and secretory diarrhea transforms a frustrating diagnostic puzzle into a systematic, solvable clinical case. By anchoring clinical reasoning in physiology—specifically evaluating the impact of fasting, calculating the fecal osmotic gap, and analyzing stool electrolyte profiles—clinicians can rapidly isolate the mechanism. This precise mechanistic clarity spares patients from prolonged suffering, optimizes healthcare resource utilization, and paves the way for targeted, curative interventions.
What specific diagnostic challenge or clinical case regarding chronic diarrhea are you currently managing in your practice?