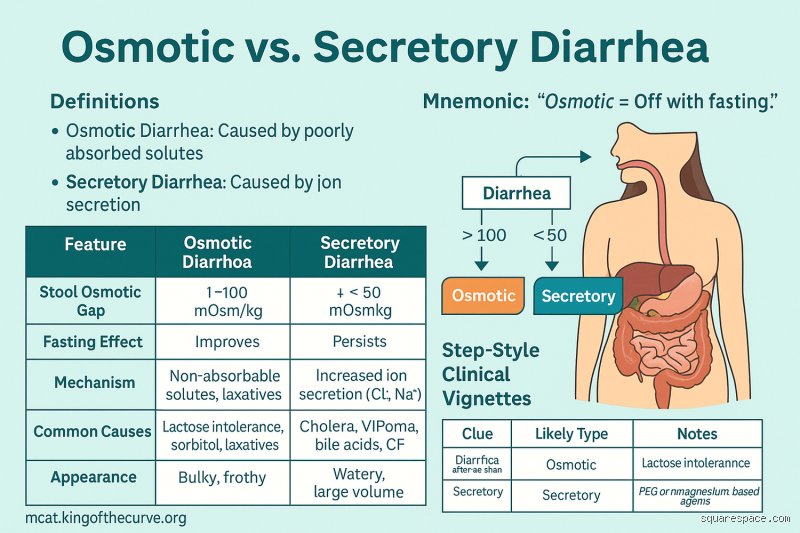
Introduction: The Physiology of Intestinal Water Balance
Diarrhea is one of the most common medical presentations worldwide, affecting individuals across all age groups and demographic backgrounds. While casual observation often reduces diarrhea to a single symptom—frequent, watery stools—gastroenterology and clinical pathophysiology recognize that this symptom represents the final common pathway of several vastly different underlying physiological disruptions. At its core, normal bowel function relies on a finely tuned, highly efficient balance between fluid and electrolyte absorption and secretion within the gastrointestinal tract.
The human gastrointestinal tract processes an astonishing volume of fluid daily. Under normal physiological conditions, an adult ingests approximately 1.5 to 2.0 liters of dietary fluids per day. However, this is combined with an immense volume of endogenous secretions produced by the salivary glands, stomach, pancreas, biliary system, and the intestine itself, totaling an additional 7.0 to 8.0 liters of fluid entering the gastrointestinal lumen daily. By the time this massive load—roughly 9 to 10 liters in total—reaches the terminal ileum and colon, the vast majority must be reclaimed. The small intestine absorbs roughly 7 to 8 liters, the colon reabsorbs an additional 1.0 to 1.5 liters, and a healthy human adult ultimately excretes less than 200 milliliters of water in their stool daily.
When this delicate equilibrium is disturbed, the result is diarrhea, clinically defined as an increase in daily stool weight (typically greater than 200 grams per day), decreased stool consistency, and an increased frequency of bowel movements. To diagnose, manage, and treat diarrhea effectively, clinicians must look past the macroscopic presentation and investigate the microscopic mechanisms driving fluid loss. Among the various classifications of acute and chronic diarrhea, two fundamental pathophysiological mechanisms stand apart: secretory diarrhea and osmotic diarrhea.
Understanding the distinct cellular mechanisms, clinical presentations, diagnostic markers, and underlying etiologies of secretory and osmotic diarrhea is crucial for medical professionals, researchers, and students alike. This first part of our comprehensive expert guide will establish a rigorous foundational framework, exploring the exact definitions, biophysical laws, cellular transporters, and clinical profiles of both conditions.
1. Defining the Spectrum: Overview of Pathophysiological Categories
Before diving deeply into secretory and osmotic diarrhea, it is helpful to contextualize them within the broader taxonomy of diarrheal diseases. Traditionally, gastroenterologists categorize chronic diarrhea into several major pathophysiological mechanisms:
Secretory Diarrhea: Driven by active, abnormal ion secretion or impaired ion absorption by intestinal epithelial cells (enterocytes and colonocytes), leading to massive fluid movement into the gut lumen that continues regardless of fasting.
Osmotic Diarrhea: Caused by the presence of poorly absorbable, osmotically active solutes within the intestinal lumen that draw water across the mucosa via osmotic pressure, which typically resolves or significantly improves with fasting.
Motility-Related Diarrhea: Resulting from rapid transit time, which leaves insufficient contact time for normal mucosal absorption (e.g., in irritable bowel syndrome or hyperthyroidism).
Inflammatory/Exudative Diarrhea: Characterized by mucosal destruction, ulceration, and exudation of plasma, mucus, and blood into the gut lumen, frequently accompanied by fever, abdominal pain, and bloody stools (e.g., inflammatory bowel disease, invasive bacterial infections).
Malabsorptive Diarrhea: Caused by structural or biochemical defects in nutrient digestion or mucosal uptake (e.g., celiac disease, pancreatic exocrine insufficiency), often featuring steatorrhea (fatty stools).
While these categories can sometimes overlap in complex clinical scenarios, secretory and osmotic diarrheas represent the two classic, textbook examples of water-electrolyte transport disorders in the absence of primary mucosal destruction or fat malabsorption. To differentiate them correctly, clinicians rely heavily on measurements such as the stool osmotic gap.
2. Deep Dive into Secretory Diarrhea
Cellular and Molecular Pathophysiology
Secretory diarrhea occurs when the normal net absorptive state of the intestinal mucosa is converted into a net secretory state. To understand how this happens, one must examine the transport mechanisms of the intestinal epithelium—specifically the enterocytes of the small intestine and colonocytes of the large intestine.
In a healthy intestine, sodium () and chloride () are actively absorbed, driving passive water reabsorption down an osmotic gradient. In secretory diarrhea, this process is dramatically reversed or overwhelmed by active, unregulated secretion of electrolytes—predominantly chloride () and bicarbonate ()—into the intestinal lumen.
The primary driver of many forms of secretory diarrhea is the intracellular second messenger system involving cyclic adenosine monophosphate (cAMP), cyclic guanosine monophosphate (cGMP), or intracellular calcium ().
Receptor Activation: Enterotoxins (such as cholera toxin) or endogenous hormones bind to specific receptors on the basolateral or apical membranes of enterocytes.
Second Messenger Cascade: This binding activates adenylate cyclase or guanylate cyclase, increasing intracellular cAMP or cGMP levels. Alternatively, certain neuroendocrine tumors release hormones that elevate intracellular calcium.
CFTR Channel Activation: These elevated second messengers activate protein kinase A (PKA) or protein kinase C (PKC), which in turn phosphorylate and open the Cystic Fibrosis Transmembrane Conductance Regulator (CFTR) chloride channels located on the apical membrane of the enterocyte.
Electrolyte and Water Flux: Chloride rushes out of the cell and into the lumen. This massive negative charge in the lumen draws sodium () paracellularly (between cells) to maintain electrical neutrality. The accumulation of sodium chloride in the lumen creates an osmotic gradient that pulls massive amounts of water out of the tissue and into the gut lumen, overwhelming the absorptive capacity of the colon.
Crucially, because secretory diarrhea is driven by active cellular transport mechanisms rather than unabsorbed food molecules, this fluid secretion does not stop when the patient fasts. Even if the patient consumes zero calories and zero oral fluids, the secretory engines within the enterocytes continue to pump electrolytes and water into the lumen.
Clinical Characteristics and Presentation
Secretory diarrhea possesses several hallmark clinical features that immediately alert an experienced clinician to its underlying mechanism:
Large Volume Stools: Patients often produce voluminous, watery stools—frequently exceeding 1 liter per day, and in severe cases like cholera, reaching 10 to 20 liters per day.
Painless or Mildly Crampy: Unlike inflammatory diarrheas that feature severe abdominal pain, tenesmus, and cramping, secretory diarrhea is classically painless or accompanied only by mild, diffuse discomfort.
No Fasting Improvement: Stool output remains high despite a 24- to 48-hour fasting test, distinguishing it sharply from osmotic diarrhea.
Isotonic Stool: The stool osmolality is roughly equal to the plasma osmolality. The electrolytes in the stool account for almost all of the osmotic activity, meaning the stool osmotic gap is very low (typically less than 50 mOsm/kg).
Major Etiologies and Causes
Secretory diarrhea can be triggered by a wide array of infectious, pharmacological, endocrine, and congenital factors:
Infectious Agents:
Vibrio cholerae: The classic paradigm of secretory diarrhea. Cholera toxin permanently activates G-proteins, causing massive, unceasing cAMP production and relentless fluid loss ("rice-water stools").
Enterotoxigenic Escherichia coli (ETEC): The primary cause of traveler's diarrhea, utilizing heat-labile and heat-stable enterotoxins that stimulate cAMP and cGMP.
Other bacterial and viral pathogens: Certain strains of Salmonella, Shigella, and viruses can induce secretory components alongside inflammatory pathways.
Endocrine Tumors (Neuroendocrine Neoplasms):
Carcinoid Syndrome: Caused by neuroendocrine tumors releasing serotonin, bradykinin, and prostaglandins.
VIPomas (Vasoactive Intestinal Peptide-secreting tumors): Also known as Verner-Morrison syndrome or "WDHA syndrome" (Watery Diarrhea, Hypokalemia, and Achlorhydria), characterized by massive secretion driven by VIP.
Gastrinomas (Zollinger-Ellison Syndrome): Excessive gastric acid inactivates pancreatic enzymes, leading to malabsorption, while hypersecretion of gastric acid and fluid contributes to watery output.
Medullary Carcinoma of the Thyroid: Associated with elevated calcitonin and prostaglandins.
Medications and Toxins:
Laxative abuse (specifically stimulant laxatives like bisacodyl, senna, or castor oil, which irritate the mucosa and stimulate active secretion).
Certain prescription drugs, herbal supplements, and heavy metal poisonings.
Congenital Defects:
Congenital Chloridorrhea: A rare autosomal recessive disorder caused by mutations in the SLC26A3 gene, resulting in defective chloride-bicarbonate exchange in the ileum and colon.
3. Deep Dive into Osmotic Diarrhea
Biophysical and Cellular Principles
In stark contrast to secretory diarrhea, osmotic diarrhea is fundamentally a problem of maldigestion or malabsorption of ingested solutes, governed by the laws of physical chemistry and osmosis.
The human small intestine is normally very permeable to water, allowing it to move freely across the epithelial barrier in response to osmotic gradients. When a person ingests substances that are poorly digested or poorly absorbed by the brush border enzymes and transport proteins of the small intestine, these molecules remain trapped within the lumen.
As these osmotically active, unabsorbed particles accumulate in the gut lumen, they increase the local osmolarity of the luminal contents. Because the luminal osmolarity significantly exceeds the osmolarity of the vascular and interstitial compartments of the intestinal mucosa, a powerful osmotic gradient is established. Water is pulled rapidly across the tight junctions and cellular membranes from the vascular and interstitial spaces into the intestinal lumen to dilute the high concentration of solutes.
This process continues down the length of the small and large intestines until osmotic equilibrium is reached. Consequently, the stool contains high concentrations of these unabsorbed solutes, alongside the dragged water.
The Diagnostic Gold Standard: The Stool Osmotic Gap
Because the fundamental mechanism of osmotic diarrhea involves unmeasured, osmotically active solutes, clinicians utilize a mathematical calculation known as the stool osmotic gap (SOG) to differentiate it from secretory diarrhea.
The total osmolality of stool is roughly equivalent to plasma osmolality (normally stable around 290 mOsm/kg). The measured electrolytes in stool are primarily sodium () and potassium (). Because these electrolytes are accompanied by counter-anions (like chloride and bicarbonate), their contribution to osmolality is doubled. The formula for the stool osmotic gap is:
In Osmotic Diarrhea: The unabsorbed, osmotically active molecules (such as magnesium, unabsorbed carbohydrates, or polyethylene glycol) account for a massive portion of the luminal osmolality, while sodium and potassium concentrations drop. This results in a high stool osmotic gap (typically greater than 100 to 125 mOsm/kg).
In Secretory Diarrhea: The stool osmolality is almost entirely accounted for by active secretion of sodium, potassium, and their anions. Therefore, the stool osmotic gap is very low (less than 50 mOsm/kg).
Clinical Characteristics and Presentation
Osmotic diarrhea displays distinct clinical features that set it apart from its secretory counterpart:
Fasting Cessation: This is the most crucial diagnostic differentiator. When the patient stops eating the offending food, medication, or solute (i.e., during a 24- to 48-hour fast), the luminal source of osmotic pressure disappears. Consequently, osmotic diarrhea stops or dramatically slows down during fasting.
Moderate Volume: Stool volume is generally less voluminous than in severe secretory diarrhea, typically ranging from 1 to 2 liters per day or less, depending on the quantity of the ingested solute.
Stool Characteristics: Stools may be frothy, acidic (if carbohydrate malabsorption leads to bacterial fermentation in the colon, producing short-chain fatty acids and gas), and associated with abdominal distension, bloating, and flatulence.
Major Etiologies and Causes
Osmotic diarrhea can stem from dietary indiscretions, congenital enzyme deficiencies, or ingestion of specific pharmacological agents:
Carbohydrate Malabsorption:
Lactase Deficiency: The most common enzymatic defect worldwide. A lack of the brush-border enzyme lactase prevents the breakdown of lactose into glucose and galactose. Unabsorbed lactose remains in the lumen, causing osmotic fluid influx and subsequent bacterial fermentation, leading to bloating, cramping, and osmotic diarrhea after dairy consumption.
Other Disaccharidase Deficiencies: Sucrase-isomaltase or trehalase deficiencies.
Ingestion of Poorly Absorbed Sugars/Sugar Alcohols: Artificial sweeteners such as sorbitol, mannitol, xylitol, and lactulose (often found in diet foods, sugar-free chewing gum, and laxatives). Because human enterocytes absorb these sugar alcohols poorly, they reliably induce osmotic diarrhea when consumed in large quantities.
Ingestion of Osmotically Active Mineral Laxatives:
Magnesium-containing laxatives (e.g., milk of magnesia, magnesium citrate).
Phosphate- or sulfate-containing laxatives (e.g., sodium phosphate bowel preparations).
Clinical Pearl: Patients suffering from clandestine laxative abuse may covertly ingest magnesium laxatives. Measuring stool magnesium levels can reveal sky-high concentrations, confirming osmotic diarrhea driven by exogenous mineral ingestion.
General Malabsorptive States (Secondary Osmotic Components):
Conditions like celiac disease, chronic pancreatitis, or small intestinal bacterial overgrowth (SIBO) can impair nutrient absorption to such a degree that unabsorbed nutrients act as osmotic agents in the lumen.
4. Interim Summary: Comparing the Core Mechanics
To solidify the foundational concepts covered in this first part, the table below highlights the primary physiological and clinical divergences between secretory and osmotic diarrhea:
End of Part 1. Continue to Part 2 for advanced diagnostic algorithms, clinical evaluation strategies, and targeted therapeutic management approaches for both secretory and osmotic diarrhea.
It looks like you provided the formatting and SEO guidelines, but you didn't include the topic or keyword!
What subject or keyword would you like this HTML-formatted synthesis to be about?