Understanding osmotic diarrhea: Duration, mechanics, and clinical trajectory
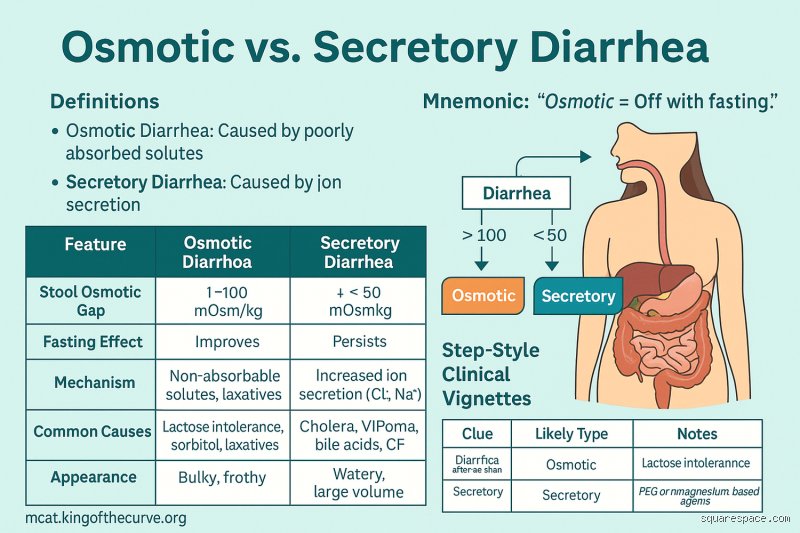
To accurately answer how long this condition typically lasts, one must first examine its underlying mechanics. Osmotic diarrhea occurs when osmotically active, poorly absorbed solutes accumulate within the intestinal tract. Because these molecules—ranging from specific sugars and artificial sweeteners to divalent ions and certain pharmaceutical agents—cannot readily cross the intestinal epithelium, they create a high osmotic pressure gradient. This gradient draws water from the body’s extracellular fluid compartments across the mucosa and directly into the intestinal lumen, overwhelming the normal reabsorptive capacity of the bowel.
The duration of osmotic diarrhea is inherently tied to the persistence of the offending trigger. Under standard circumstances, acute osmotic episodes are self-limiting and resolve rapidly, often within twenty-four to seventy-two hours, once the causative agent is identified and eliminated from the diet or medication regimen. For example, an individual who consumes an excess of sugar alcohols like sorbitol or mannitol, or experiences transient malabsorption following a heavy intake of lactose-containing dairy products, will typically notice symptoms abate entirely as soon as the substance passes through the digestive tract and intake ceases.
Key determinants of duration
While simple dietary indiscretions lead to short-lived episodes lasting only a couple of days, the timeline varies significantly based on several physiological and behavioral factors:
Nature of the Exposure: Ingestion of a single offending meal or acute laxative misuse results in transient diarrhea that disappears within hours to a few days. Conversely, continuous or repeated ingestion of hidden osmotically active agents, such as chronic consumption of diet foods containing sugar substitutes or habitual overuse of magnesium-based antacids, perpetuates symptoms indefinitely until the exposure stops.
Underlying Digestive Enzyme Deficiencies: Chronic enzyme insufficiencies, such as adult-onset hypolactasia (lactose intolerance) or exocrine pancreatic insufficiency, prevent the proper breakdown of macronutrients. If unmanaged, these enzymatic gaps cause recurring or persistent osmotic symptoms whenever the specific food group is consumed.
Mucosal Surface Area and Transit Time: Conditions that reduce the functional surface area of the small intestine, such as celiac disease, small intestinal bacterial overgrowth (SIBO), or short bowel syndrome, impair overall absorptive efficiency. In these clinical scenarios, osmotic loads that a healthy gut would handle easily can trigger prolonged or chronic bouts of loose, watery stools.
The diagnostic hallmark: Response to fasting
A definitive diagnostic feature that separates osmotic diarrhea from secretory diarrhea is its behavior during a fast. Because osmotic diarrhea relies entirely on the presence of unabsorbed luminal solutes drawing water outward, withholding food halts the introduction of new solutes. Consequently, true osmotic diarrhea typically resolves or drastically decreases during a twenty-four to forty-eight-hour fasting window, whereas secretory processes continue unabated regardless of oral intake.
Recognizing this temporal and physiological pattern allows healthcare providers to narrow down differential diagnoses quickly. When symptoms persist beyond a few days despite dietary modifications, or if they occur in the absence of obvious dietary triggers, further clinical evaluation becomes necessary to identify underlying malabsorption syndromes or chronic gastrointestinal disorders.
Dietary adjustments for faster recovery
Modifying daily food choices plays a direct role in how quickly osmotic symptoms resolve. Eliminating specific problematic items halts the active osmotic pull inside the intestinal lumen.
Replace regular dairy products with lactose-free alternatives if dairy sensitivity is the primary trigger.
Limit consumption of sugar-free gums, candies, and beverages containing sorbitol, mannitol, or xylitol.
Choose easily digestible, bland foods such as white rice, bananas, toast, and plain chicken during acute flare-ups.
The impact of fasting on symptom duration
Fasting serves as a major diagnostic and therapeutic tool unique to this specific form of digestive distress. Because unabsorbed solutes drive the condition, withholding food entirely stops the influx of osmotic agents.
Clinical observations show that symptoms typically cease or dramatically improve during periods of fasting. This distinct response helps healthcare providers differentiate osmotic processes from secretory variants, which persist even without food intake.
Managing chronic underlying conditions
When symptoms extend past several weeks, addressing the root medical diagnosis dictates the long-term outlook. Conditions like celiac disease or chronic enzyme deficiencies require structured medical management plans.
Implement strict gluten avoidance protocols if small bowel biopsy confirms celiac enteropathy.
Utilize prescribed enzyme replacement supplements to properly break down complex carbohydrates and sugars.
Work alongside a registered dietitian to ensure nutritional adequacy while eliminating trigger food groups.
Monitoring for potential complications
Prolonged fluid shifts within the gastrointestinal tract can lead to secondary health concerns if left unmanaged. Frequent watery stools deplete essential bodily fluids and critical electrolytes.
Maintaining adequate hydration via water and oral rehydration solutions prevents severe complications during recovery. Professional medical evaluation becomes necessary if signs of significant dehydration, persistent abdominal pain, or unintended weight loss develop.