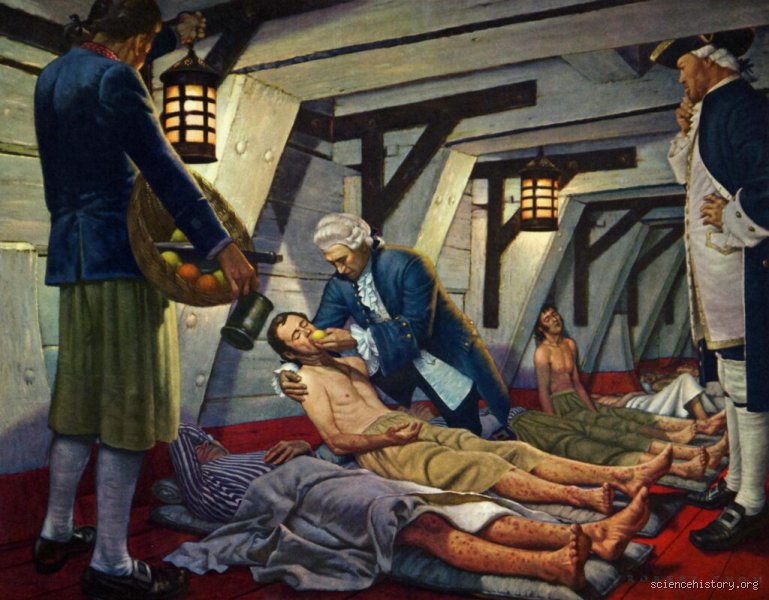
The ancient scourge of the high seas
While modern medicine understands dysentery as a treatable intestinal infection, historical sailors knew it only as a merciless affliction that turned long voyages into floating hospitals and mass graves. To comprehend why seafaring life was so uniquely conducive to this disease, one must examine the intersection of 17th- and 18th-century naval technology, rudimentary food science, primitive sanitation, and human physiology. This article explores the root causes of dysentery in sailors, tracing the microbiological, environmental, and logistical factors that made the open ocean a breeding ground for this devastating gastrointestinal scourge.
Defining the enemy: What is Dysentery?
To understand how sailors fell victim to dysentery, it is first necessary to distinguish it from ordinary traveler's diarrhea or mild food poisoning. Clinically, dysentery is an inflammatory disorder of the intestine—specifically the colon—that results in severe diarrhea containing blood and mucus, often accompanied by excruciating abdominal cramps (tenesmus), fever, and profound systemic dehydration.
Historically, naval surgeons and journals referred to dysentery under various grim synonyms, including "the bloody flux," "scouring," or "camp dysentery" (when troops were embarked on troopships). In the confined, unhygienic floating micro-societies of sailing ships, dysentery was rarely an isolated medical incident; it regularly erupted into shipwide epidemics that could incapacitate eighty percent of a crew within a matter of weeks.
The primary culprits behind dysentery are categorized into two main forms based on their causative agents:
Bacterial (Bacillary) Dysentery: Caused most frequently by bacteria of the genus Shigella. It is characterized by rapid onset, high fever, and extreme toxicity due to the potent shiga toxin. Transmission occurs via the fecal-oral route through contaminated water, food, or direct contact.
Parasitic (Amoebic) Dysentery: Caused by the protozoan parasite Entamoeba histolytica. This form typically has a more insidious onset, leading to chronic infection, ulceration of the intestinal wall, and potential dissemination to the liver or other organs if left untreated.
In the sailing era, neither captains nor surgeons possessed microscopes, germ theory, or effective pharmacotherapy. They fought an invisible enemy blindfolded, relying on bloodletting, heavy metals like mercury, and herbal astringents, treatments that frequently accelerated a patient’s demise rather than halting the infection.
The logistical nightmare: Food and water storage at sea
The single greatest driver of dysentery outbreaks aboard historical sailing ships was the profound difficulty of preserving safe food and potable water over weeks or months at sea. Without refrigeration, canning, or chemical preservation, naval provisioning relied on medieval techniques that invariably broke down under tropical heat, humidity, and dampness.
1. The water cask dilemma
Fresh water was the lifeblood of any vessel, yet storing it safely in wooden casks (butts or puncheons) was an engineering impossibility for long voyages.
Bacterial Growth: Wooden casks previously used for storage or constructed with green timber quickly became contaminated with organic matter. Within days of filling casks from rivers, estuaries, or communal dockside wells, often polluted with human sewage, the water stagnated. Algae, bacteria, and protozoa bloomed in the dark, warm interior of the hold.
Rationing and Putrefaction: As water putrefied, it turned green, thick, and foul-smelling. Sailors were frequently forced to "chew" their water or strain it through dirty canvas neckerchiefs just to remove solid matter and wriggling insect larvae before drinking. This putrid fluid served as a primary vector for Shigella and other enteric pathogens.
2. Spoiled rations and the ship’s pantry
Naval rations, consisting primarily of salt beef, salt pork, hardtack (ship's biscuit), dried peas, and cheese, were notoriously susceptible to environmental degradation.
Infestation: Hardtack biscuit was routinely infested with weevils, maggots, and beetle larvae (Tenebrio molitor). While sailors often joked about "meat in their bread," the biological waste left behind by these pests compromised the food's integrity.
Mould and Rot: Dampness in the ship's hold caused salt meats to spoil, turn slimy, or become infested with blowfly maggots. In tropical climates, meat rotted rapidly once exposed to the air. Ingesting spoiled or microbially compromised provisions introduced massive bacterial loads directly into the digestive tracts of already weakened men, triggering acute gastrointestinal inflammation.
Cramped quarters and personal hygiene challenges
Beyond contaminated provisions, the physical architecture of a sailing warship or merchant vessel created an environment where infectious diseases could spread with terrifying velocity.
Overcrowding and close contact
A British Royal Navy Third-Rate ship of the line, for example, typically carried a complement of roughly 500 to 650 men crammed into the lower decks. Sailors slept in swinging hammocks hung shoulder-to-shoulder, often with less than fourteen inches of lateral space per man.
If a single sailor contracted bacillary dysentery ashore and brought it aboard, the close proximity guaranteed rapid transmission.
Airborne droplets, shared utensils, crowded mess tables, and inadequate washing facilities transformed the berth deck into an epidemiological amplifier.
The Sanitation Void
Sanitation facilities aboard historical ships were primitive to non-existent by modern standards:
The "Head": The crew's latrines, known as the "heads", were located right at the bow of the ship on the grating just above the cutwater. Accessing them in rough seas was perilous, dangerous, and sometimes fatal, particularly at night or during storms when waves washed violently over the bow.
Alternative Practices: Because using the head during heavy weather was hazardous, many sailors resorted to relieving themselves in buckets, bilges, or unventilated corners below decks.
The Fly Factor: Flies and other vermin swarmed the lower decks, breeding in accumulated filth, food scraps, and stagnant bilge water. These insects acted as mechanical vectors, landing on human waste and subsequently walking over the crew's rations, mess gear, and drinking cups, directly transferring pathogens from the latrine to the dinner table.
Physiological vulnerability: Scurvy, fatigue, and immunity
Dysentery does not strike in a vacuum. The human body possesses natural mucosal defenses and immune barriers within the gastrointestinal tract that can often suppress minor pathogen loads. However, the unique lifestyle of a sailor systematically dismantled these physiological defenses.
Nutritional Deficiencies (Scurvy): Months at sea without fresh fruits or vegetables resulted in severe Vitamin C deficiency, or scurvy. Beyond causing bleeding gums and loose teeth, scurvy degrades the integrity of connective tissues throughout the body, including the epithelial linings of the gastrointestinal tract. A compromised intestinal lining offers vastly reduced resistance to bacterial invasion and ulceration, turning what might have been mild gastroenteritis into full-blown, hemorrhagic dysentery.
Physical Exhaustion: Sailors worked grueling shifts, often operating on the watch system of four hours on, four hours off, exposed to freezing spray, driving rain, and tropical heat without adequate dry clothing or rest. Physical exhaustion suppresses the immune system, leaving the body unable to mount an effective defense against opportunistic enteric infections.
Salt-Heavy Diets and Dehydration: The heavy reliance on salted meats led to chronic mild dehydration and electrolyte imbalances, which impaired normal renal and gastrointestinal function, exacerbating the physiological shock of sudden fluid loss caused by diarrheal disease.
The crucible of contagion: Bacterial and Parasitic culprits of maritime Dysentery
To fully understand the scourge of dysentery that historically decimated ship crews, one must look beyond the generic label of "flux" or "bloody flux" and examine the specific pathogens that thrived in the unique microclimate of a sailing vessel. While viral agents like rotavirus or norovirus certainly swept through cramped quarters, the hallmark of true dysentery, characterized by severe, bloody, and mucus-laden diarrhea accompanied by agonizing abdominal cramps and fever, was principally driven by bacterial and parasitic organisms.
In the wooden-hulled floating communities of the Age of Sail, several primary microbial agents reigned supreme, turning ordinary voyages into floating pest houses.
1. Shigella species: The tyrant of the tropics and transits
Among bacterial pathogens, Shigella species (particularly Shigella dysenteriae) stand out as perhaps the most lethal historical driver of epidemic dysentery among sailors. Shigella is characterized by its extraordinarily low infectious dose; swallowing fewer than 100 bacterial cells can be enough to trigger a full-blown infection. On a ship, where personal hygiene was severely compromised by water rationing and salt-water washing, the fecal-oral route was virtually impossible to break once the bacteria entered the ship's ecosystem.
Shigella dysenteriae type 1 produces the potent Shiga toxin, which damages the mucosal lining of the large intestine, leading to the characteristic ulceration, bleeding, and severe inflammation. In sailors, whose baseline health was often undermined by scurvy, malnutrition, and exhaustion, shigellosis frequently escalated rapidly into systemic toxicity, severe dehydration, and death. Outbreaks could sweep an entire warship or merchantman within days of leaving a tropical port where fresh, contaminated provisions or water had been loaded.
2. Entamoeba histolytica: The insidious invader
While bacterial dysentery struck with explosive, acute fury, amoebic dysentery, caused by the protozoan parasite Entamoeba histolytica, waged a more insidious, prolonged war on maritime health. Unlike bacteria that multiplied extracellularly, E. histolytica exists in two forms: the hardy, infectious cyst capable of surviving weeks in damp, cool shipboard environments (such as on unwashed utensils or in bilge-contaminated water casks), and the active trophozoite that burrowed into the colonic mucosa.
Sailors operating in tropical and subtropical waters (such as the Caribbean, the Indian Ocean, or the East Indies trade routes) were prime targets. The parasite formed characteristic "flask-shaped" ulcers in the intestinal wall. Left unchecked, and with the rudimentary medical treatments available in centuries past, such as chalk, opium boluses, or lead acetate, which did nothing to eradicate the parasite, amoebic dysentery often became chronic. It led to debilitating cycles of relapse, severe weight loss ("consumption" of a different kind), and terrifying complications such as amoebic liver abscesses, where the parasite traveled via the bloodstream to the liver, creating massive pus-filled cavities that frequently proved fatal at sea.
3. Salmonella enterica and invasive enterics
While often associated with standard food poisoning, specific strains of Salmonella, notably Salmonella typhi (the causative agent of typhoid fever) and non-typhoidal Salmonella species, frequently blurred the lines with dysenteric illness on long voyages. Cramped galley conditions, rat-infested hold storage, and rotting provisions meant that salted meats, moldy biscuits, and weevil-ridden grains routinely served as vectors for salmonellosis.
When food stores spoiled in the humid, unventilated lower decks, massive bacterial loads were ingested by the crew. While typhoid presented primarily with sustained high fevers, delirium, and "rose spots," severe gastrointestinal involvement often produced bloody stools, mimicking or compounding dysenteric outbreaks. The inability to properly refrigerate or cook food fresh at sea transformed the ship's galley into an incubation chamber for these enteropathogens.
Environmental and societal amplifiers aboard ship
Microbes alone did not create the maritime disaster of dysentery; they merely acted as the executioners for a complex web of environmental, logistical, and socio-economic factors unique to life on the high seas.
Water casks and the liquid vector
The single most critical lifeline on any sailing vessel was fresh water. However, storing water for hundreds of men over months at sea in wooden casks (puncheons or butt casks) was a biological hazard. Stagnant water in wooden barrels rapidly fostered the growth of biofilms, algae, and pathogenic bacteria. As ships rolled on the waves, organic sediment at the bottom of the casks was stirred up, turning clear water into a brackish, foul-smelling, and microbe-dense slurry.
Sailors were forced to drink this water, often rationing it tightly during doldrums or prolonged chases. Even when rum, wine, or small beer was substituted to mitigate spoilage, the baseline water used for cooking stews (skouse or lobscouse) and grog frequently served as the primary vehicle for introducing Shigella or amoebic cysts to the entire ship's company simultaneously.
Sanitation, Vermin, and the "Head"
Sanitary infrastructure on historical sailing ships was primitive to non-existent by modern standards. The crew's latrines, known as the "heads", were typically located right at the bow of the ship (the beakhead), exposed to crashing waves and spray. For sailors weakened by illness, sea-sickness, or severe weather, crawling out to the bow was treacherous and physically exhausting, leading many to resort to unhygienic alternatives below decks or failing to wash their hands afterward.
Wooden sailing vessels were swarming with vermin: rats, mice, cockroaches, and flies. These pests moved freely between the bilge water, the cargo holds (storing food, hides, and sugar), and the berths where men slept hammocks-to-hammocks. Houseflies and blowflies acted as mechanical vectors, landing on human waste and subsequently swarming over exposed shipboard rations, spreading pathogens with terrifying efficiency.
Dietary Deficiencies and immune collapse
A sailor’s diet on a long voyage was notoriously deficient in fresh vitamins, minerals, and proteins. Scurvy (Vitamin C deficiency) caused widespread degradation of connective tissue, compromised mucosal barriers throughout the gastrointestinal tract, and shattered immune defenses. When a scorbutic crew member ingested contaminated food or water, their compromised intestinal lining offered virtually no resistance to invasive pathogens like Shigella or E. histolytica. Malnutrition thus converted what might have been a mild gastrointestinal upset in a healthy landlubber into a fulminant, systemic catastrophe for a mariner.
Medical missteps and historical therapeutics
Compounding the misery of dysentery was the state of naval medicine. For centuries, physicians and surgeons operating aboard warships and merchant vessels possessed no concept of germ theory. Treatments were rooted in humoral medicine, attempting to balance bodily fluids through drastic and often counterproductive interventions.
Common treatments prescribed by ship surgeons included:
Astringents and Opiates: Laudanum (a tincture of opium) was widely used to slow intestinal motility and ease the agonizing cramps. While it provided symptomatic relief, it did nothing to clear the underlying bacterial or parasitic infection and could sometimes prolong the retention of toxins in the gut.
Mercurial Calomel: Mercurous chloride was frequently administered as a purgative. In high doses, mercury toxicity added chemical poisoning to infectious colitis, severely worsening the patient's condition and accelerating renal failure or systemic collapse.
Bloodletting: Believed to reduce "inflammation" and fever, bleeding a patient already suffering from acute fluid loss, bloody diarrhea, and severe dehydration often pushed them directly into hypovolemic shock and hastened their demise.
Surgeons operated in cramped, poorly lit cockpit spaces beneath the waterline, surrounded by the stench of sickness and unwashed bodies, where cross-contamination between patients was virtually guaranteed.
The Turning of the Tide
The scourge of dysentery among sailors did not abate through minor medical tweaks, but through a profound revolution in maritime hygiene, food preservation, and medical science. The introduction of iron water tanks in the 19th century replaced porous, bacteria-harboring wooden casks. The invention of canning (initially by Nicolas Appert and perfected for naval use) and later refrigeration allowed crews to consume fresh, uncontaminated provisions rather than maggot-infested hardtack and putrid salt beef.
The adoption of strict quarantine protocols, mandatory handwashing regimens, improved ventilation below decks, and the eventual discovery of specific antibiotics and anti-parasitic medications transformed seafaring. While dysentery once claimed more British and European sailors than enemy cannon fire, understanding its multi-faceted biological and environmental causes allowed naval powers to finally conquer the bloody flux, turning the open ocean from a floating graveyard into a navigable highway for global exploration and commerce.