Throughout the annals of human history, few afflictions have shaped the outcomes of wars, decimated populations, and humbled monarchs quite like dysentery. Often overshadowed in popular historical consciousness by dramatic plagues or sweeping viral outbreaks, dysentery was a relentless, silent killer. It struck armies in their tents, sailors on long maritime voyages, and urban populations huddled in unsanitary medieval cities. To understand this disease is to understand a fundamental barrier to human expansion, military strategy, and medical development.
This first part of our exploration delves into the nature of dysentery, its historical impact as a primary engine of mortality, and the foundational medical frameworks—spanning ancient humoral theory to early empirical observations—that physicians used to conceptualize and attempt to treat this devastating gastrointestinal crisis.
Defining the Enemy: What Is Dysentery?
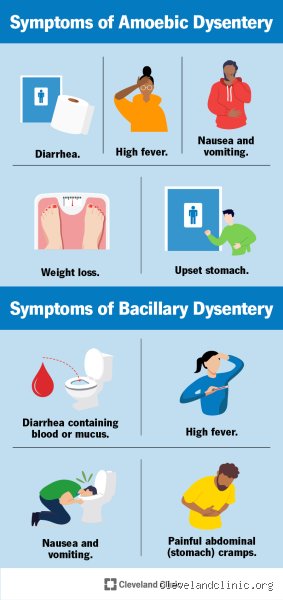
Before examining how historical healers attempted to cure the affliction, it is essential to understand what dysentery actually is. Historically, the term "dysentery"—derived from the Greek dysenteria, meaning "affliction of the intestines"—was used as an umbrella diagnosis for any severe gastrointestinal disorder characterized by severe abdominal cramps, frequent and painful bowel movements, and the presence of blood and mucus in the stool.
In modern medical terms, dysentery typically manifests in two primary forms:
Bacterial (Shigellosis): Caused by Shigella species, this form is highly contagious and spreads rapidly through contaminated food and water, particularly in crowded, unsanitary conditions.
Amoebic: Caused by the parasite Entamoeba histolytica, this variety is more prevalent in tropical and subtropical regions and can lead to chronic infections and liver abscesses if left untreated.
Unlike simple traveler's diarrhea, true dysentery causes inflammation of the intestinal lining (particularly the colon), leading to ulceration, bleeding, and severe fluid loss. In eras lacking intravenous rehydration, electrolyte balancing, and modern antibiotics, acute dysentery frequently resulted in death from dehydration, systemic shock, or secondary infections.
The Historical Shadow: Battles Lost to the Bowels
To fully grasp why historical physicians were so desperate to find a cure, one must look at the immense scale of human suffering caused by the disease. For centuries, military historians have noted that more soldiers died from disease than from enemy weapons, and dysentery was chief among these killers.
1. Classical Antiquity and the Ancient World
Ancient texts from Mesopotamia, Egypt, and Greece frequently describe symptoms matching dysentery. In the campaigns of Alexander the Great and the Roman legions, maintaining sanitary water supplies for thousands of men and animals was a logistical nightmare. Armies encamped in one location for too long inevitably fouled their local water sources, turning their own encampments into breeding grounds for Shigella and other pathogens.
2. The Middle Ages and Early Modern Warfare
During the medieval Crusades, dysentery swept through Christian and Muslim camps alike. The siege of Antioch in 1098 saw thousands succumb to pestilence and bowel fluxes, severely compromising military efficacy. Centuries later, the Duke of Wellington’s campaigns during the Napoleonic Wars were similarly plagued. Dysentery did not care about rank or tactical brilliance; it incapacitated common foot soldiers and generals with equal indifference.
3. Maritime Exploration
During the Age of Sail, long voyages across the Atlantic and Pacific oceans exposed crews to spoiled rations, rancid water, and poor hygiene. Ships became floating incubators. Sailors suffering from severe dysentery were often too weak to manage the rigging, leading to shipwreck or the failure of entire expeditions.
The Ancient and Medieval Framework: The Humoral Theory of Disease
To comprehend how historical healers attempted to cure dysentery, we must step inside their worldview. For over two millennia, Western medicine was dominated by the Humoral Theory, originally formulated by ancient Greek physicians like Hippocrates and later expanded by Galen in the Roman era.
According to this doctrine, the human body was composed of four primary fluids, or humors:
Blood
Phlegm
Yellow Bile
Black Bile
Health depended on maintaining a delicate balance among these fluids. Disease, conversely, was viewed as an imbalance or corruption of the humors. Dysentery was understood not as a microscopic bacterial infection, but as a severe disturbance—a "flux"—of the lower digestive tract, where corrupt humors were violently expelled by nature in an attempt to restore balance.
The Diagnostic Approach
Ancient and medieval practitioners diagnosed dysentery by closely observing the frequency of evacuations, the color and consistency of the stool, and the patient's accompanying fevers or pulse rates. Because the primary symptom was an excessive discharge (the flux), the overarching therapeutic philosophy was centered on two main goals:
Astringency: Binding the bowels to stop the loss of vital fluids and substance.
Evacuation and Purification: Initially, many physicians believed that if harmful humors were trapped within the body, mild purgatives or bloodletting were necessary to cleanse the system before applying binding agents, a practice that frequently worsened dehydration with lethal consequences.
Early Herbalism and Pharmacopeia
Lacking synthetic pharmaceuticals, historical healers turned to the natural world—particularly plants, minerals, and animal products—to construct remedies. Over centuries of trial, error, and observation, healers compiled vast pharmacopeias. Many of these remedies contained active compounds that modern science recognizes as having mild astringent, anti-inflammatory, or antimicrobial properties, even if the practitioners understood them through the lens of humoral qualities (such as "hot" and "dry").
Key Botanical Remedies in Antiquity and the Middle Ages
Oak Bark and Gallnuts: Rich in natural tannins, oak bark was pulverized into powders or brewed into strong teas. Tannins act as powerful astringents, precipitating proteins in the gut lining to create a protective barrier against irritation and reduce fluid secretion.
Pomegranate Rind: The peel of the pomegranate, particularly when dried and ground, was widely utilized across the Mediterranean and Middle East. Like oak bark, it possesses a high concentration of tannins, making it a staple anti-diarrheal treatment in Greco-Roman and Islamic medicine.
Acacia and Tragacanth Gums: Plant resins were used to soothe inflamed mucosal membranes in the digestive tract, offering a protective coating effect.
Portulaca (Purslane): Recommended by ancient herbalists, purslane was consumed as a vegetable or medicinal herb. Modern research shows it contains high levels of omega-3 fatty acids and antioxidants, though its historical use was largely driven by its perceived cooling and soothing humoral properties.
Islamic Golden Age Contributions
During the medieval Islamic Golden Age, scholar-physicians such as Avicenna (Ibn Sina) refined the management of gastrointestinal diseases. In his monumental work, The Canon of Medicine, Avicenna categorized various types of fluxes and prescribed precise dietary regimens alongside herbal compounds. Islamic medicine emphasized gentle dietary control—such as rice water, barley water, and lean broths—which unintentionally provided crucial hydration and easily digestible nutrients to weakened patients, far outperforming the harsher purges common in Western Europe at the time.
The Dilemma of Early Therapeutics
Despite the presence of helpful astringents and soothing broths, treating dysentery before the advent of modern microbiology remained a desperate guessing game. Healers operated in the dark, unable to distinguish between viral, bacterial, and parasitic causes. A remedy that might temporarily bind the bowels of a patient with mild irritation could prove fatal to someone suffering from severe invasive bacterial dysentery, where trapping the pathogen inside the body could exacerbate systemic infection and fever.
As European medicine transitioned into the Renaissance and early modern periods, trade routes expanded, bringing new botanical treasures—and new medical theories—from the Americas and Asia into European apothecaries. Yet, the fundamental question remained: Was there truly a cure?
In the next part of this exploration, we will examine the introduction of revolutionary global remedies (such as ipecacuanha and cinchona bark), the grueling medical interventions of the 18th and 19th centuries, and the ultimate scientific breakthrough that finally unlocked the biological secrets of dysentery.
What specific historical period or remedy would you like to explore further as we transition into the global trade era of dysentery treatments in Part II?
The Paradigm Shift: From Humors to Microbes
For centuries, medical practitioners groped in the dark, treating the violent symptoms of dysentery with therapies that often accelerated the patient's demise. The foundational belief system of Western medicine—humoral pathology—dictated that diseases arose from an imbalance of bodily fluids.
This meant that a person already suffering from severe fluid loss due to relentless diarrhea was routinely subjected to:
Bloodletting: Draining precious blood to "reduce inflammation" and purge bad humors.
Emetics and Purges: Administering mercury-based compounds like calomel, along with antimony and powerful laxatives, to force vomiting and bowel movements.
Blistering Agents: Applying chemical irritants to the skin to raise painful blisters, under the false theory that drawing fluid to the surface would relieve internal congestion.
Instead of curing the infection, these practices deepened dehydration, introduced heavy metal toxicity, and left already exhausted bodies defenseless. While traditional remedies occasionally featured botanical concoctions that offered marginal relief—such as ipecac root or opium to dull intestinal spasms—these substances masked symptoms rather than neutralizing the underlying pathogen. There was no true cure because the medical world fundamentally misunderstood the enemy.
The Breakthrough: Bacteriology and Modern Pharmacology
The landscape of human health transformed utterly in the late 19th and early 20th centuries with the advent of the germ theory of disease. Scientists finally identified the micro-organisms responsible for the scourge: Shigella species (responsible for bacillary dysentery) and Entamoeba histolytica (responsible for amoebic dysentery).
Knowing the microbial culprit changed everything. For the first time, "curing" dysentery shifted from speculative philosophy to targeted scientific intervention:
The Modern Definition of a Cure: A true cure requires halting the pathogen's replication, repairing cellular damage, and—most critically—reversing the fatal dehydration caused by fluid loss.
Rehydration Therapy: Before antibiotics, the development of Oral Rehydration Therapy (ORT) and intravenous saline solutions saved millions. Because dysentery kills primarily by rapid fluid and electrolyte depletion, simply keeping the patient hydrated allows the body's immune system time to fight off the infection.
Antimicrobial and Antiparasitic Agents: The discovery of sulfonamides in the 1930s, followed by modern broad-spectrum antibiotics and specific anti-amoebic medications (like metronidazole), provided targeted weaponry to eradicate the bacteria or parasites directly.
Conclusion: Did History Find Its Cure?
So, was there a cure for dysentery? Historically speaking, for thousands of years, the answer was a tragic no. Millions of soldiers, travelers, and children succumbed to the "bloody flux" not just because of the virulence of the pathogens, but because the prevailing medical treatments actively worsened their condition.
Today, however, dysentery is a fully manageable and curable condition in regions with access to clean water, sanitation, modern diagnostics, and pharmaceuticals. While drug-resistant strains continue to pose clinical challenges in developing areas, medical science has definitively turned a death sentence into a treatable infection.
What aspect of medical history or historical disease management would you like to explore next?