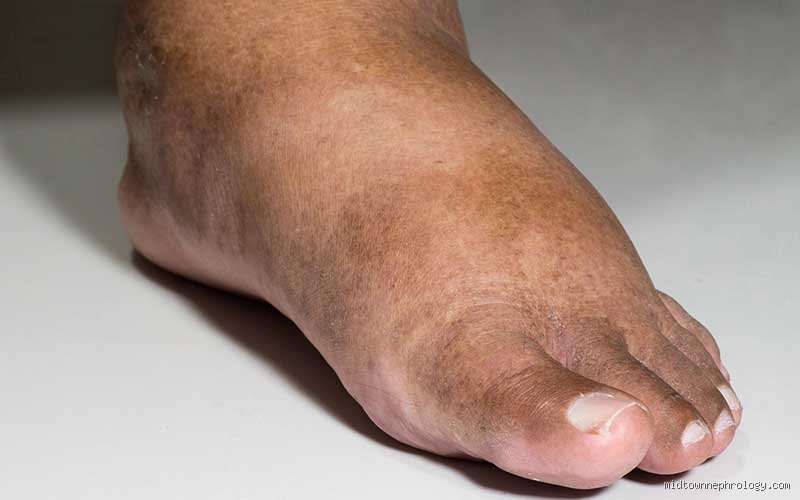
However, when swelling in the lower extremities becomes a regular occurrence, lingers persistently, or worsens over time, it naturally triggers a deeper wave of concern. One of the most common and pressing questions people ask when they notice persistent puffiness is: Does this mean something is wrong with my kidneys?
The short answer is: It is entirely possible, but swollen feet do not automatically point to kidney disease. While the kidneys play a master regulatory role in managing the body's fluid balance, swelling in the feet, ankles, and legs can stem from a wide array of physiological mechanisms, ranging from simple lifestyle factors and localized circulation issues to complex systemic conditions involving the heart, liver, and vascular network.
To truly understand whether your swollen feet could be signaling a kidney issue, we must dive deep into the intricate plumbing and biochemistry of the human body. This first part of our comprehensive expert guide will explore how fluid regulation works, the distinct mechanisms by which kidney dysfunction leads to edema, and how to distinguish kidney-related fluid retention from other common culprits.
1. Demystifying Edema: What is swelling and why does it happen?
To grasp why kidney problems can manifest as swollen feet, we first need to define what edema actually is at a microscopic level. The human body is roughly 60% water, but this water is meticulously partitioned. Most of it is held safely inside our cells (intracellular fluid) or circulating within our blood vessels and lymphatic channels (intravascular fluid). A smaller, highly dynamic portion resides in the interstitial space, the microscopic matrix of connective tissue that surrounds cells.
Edema occurs when an abnormal volume of fluid leaks out of the bloodstream and accumulates within this interstitial space. Because of gravity, this excess fluid naturally migrates downward, pulling toward the lowest points of the body. For anyone walking, standing, or sitting upright throughout the day, those lowest points are invariably the feet and ankles.
The movement of fluid across the walls of tiny blood vessels called capillaries is governed by a precise biophysical equation known as Starling forces. These forces balance two competing pressures:
Hydrostatic Pressure: The physical pressure exerted by the blood pumping against the inside walls of the capillaries, which tends to push fluid out into the tissues.
Oncotic (Colloid Osmotic) Pressure: The osmotic suction pressure exerted by large proteins (most notably albumin) dissolved in the blood plasma, which acts like a sponge, pulling fluid back into the blood vessels.
When these forces fall out of equilibrium, either because hydrostatic pressure becomes too high, capillary walls become overly permeable, or blood protein levels drop too low, fluid escapes into the tissue spaces faster than the lymphatic system can drain it away. The result is visible, palpable swelling.
2. The magnificent filtering machine: How healthy kidneys regulate fluid and sodium balance
The kidneys are biological masterpieces. Though small, each roughly the size of a fist and shaped like a kidney bean, they receive about 20 to 25 percent of the body's total cardiac output. Inside each kidney are over a million microscopic functional units called nephrons, which act as advanced filtration and recycling centers.
Every single minute, your kidneys filter roughly 120 to 140 milliliters of blood through a specialized cluster of microscopic blood vessels called the glomerulus. As blood surges through the glomerulus, water, small molecules, electrolytes, and waste products are filtered out, while larger components like red blood cells and vital proteins are retained in the bloodstream.
As this ultrafiltrate travels down the winding tubules of the nephron, the kidneys engage in an extraordinary balancing act. They selectively reabsorb precisely the right amount of water, sodium, potassium, and chloride needed to maintain systemic homeostasis, while excreting excess waste products, toxins, and surplus water as urine.
When it comes to fluid retention and swelling, sodium handling is the single most critical variable. Water follows sodium wherever it goes through osmotic pressure. Healthy kidneys maintain strict control over sodium excretion; if you eat a salty meal, they quickly ramp up sodium and water excretion to keep your total blood volume and blood pressure stable. If you are dehydrated, they conserve water.
However, when kidney function becomes impaired, this delicate feedback loop begins to break down.
3. The sodium and Water trap: How Kidney Disease drives fluid overload
When a person develops Chronic Kidney Disease (CKD) or experiences Acute Kidney Injury (AKI), the structural integrity and filtering efficiency of the nephrons decline. As the overall Glomerular Filtration Rate (GFR) drops, the kidneys lose their acute ability to filter and excrete excess sodium and water effectively.
Instead of being eliminated in the urine, surplus sodium and water are retained within the bloodstream. As the total volume of fluid circulating inside the blood vessels increases (a state known as hypervolemia or expanded plasma volume), the hydrostatic pressure within the capillaries rises.
This elevated hydrostatic pressure forces excess fluid outward across the capillary walls and directly into the surrounding interstitial tissues. Because of gravity, this extra fluid pools predominantly in the lower legs, ankles, and feet.
As the kidneys struggle to maintain electrolyte balance, they activate hormonal compensation pathways, most notably the Renin-Angiotensin-Aldosterone System (RAAS). While the RAAS is designed to protect the body against severe blood loss or dehydration by holding onto salt and water, in the context of failing kidneys, it backfires. It continually signals the body to retain even more sodium, compounding the fluid overload and worsening the peripheral edema.
4. The protein puzzle: Nephrotic Syndrome and its distinct role in swelling
While generalized fluid retention from failing filtration is a primary hallmark of advanced kidney disease, there is a completely separate, highly specific renal mechanism that causes dramatic swelling: Nephrotic Syndrome.
To understand nephrotic syndrome, we must look closer at the glomerular filter. The microscopic filters in healthy kidneys feature a complex barrier lined with specialized cells called podocytes, which act like a fine sieve. This sieve allows tiny waste molecules to pass into the urine while locking essential blood proteins, specifically a major protein called albumin, securely inside the bloodstream.
In nephrotic syndrome, various diseases or immune-mediated inflammatory processes damage this delicate filtering membrane. As a result, massive amounts of albumin leak out of the blood and into the urine (a condition called heavy proteinuria or albuminuria).
When blood albumin levels plummet (hypoalbuminemia), the oncotic pressure inside the capillaries drops precipitously. Remember, albumin acts like an osmotic sponge holding fluid inside the blood vessels. Without enough albumin, that "suction" force is lost. Consequently, fluid freely slips out of the capillaries and floods the interstitial spaces throughout the entire body.
The swelling caused by nephrotic syndrome can be profound and generalized. While it frequently appears in the feet, ankles, and lower legs due to gravity, it is also classically associated with prominent puffiness around the eyes (periorbital edema), particularly noticeable in the morning after waking up, as well as fluid accumulation in the abdominal cavity (ascites).
5. Chronic Kidney Disease vs. Acute Kidney Injury: Timing and presentation
When evaluating whether swollen feet indicate a kidney problem, physicians also examine the timeline and context of the symptom's onset. Kidney-related edema typically manifests in two distinct clinical patterns:
Chronic Kidney Disease (CKD) Progression: CKD is characterized by a gradual, progressive loss of kidney function over months or years. In the earlier stages of CKD, the remaining functional nephrons compensate exceptionally well, and edema is rare. However, as the disease advances into later stages (typically Stage 3 through Stage 5), compensatory mechanisms max out. Swelling in the feet and ankles tends to develop slowly, creeping up insidiously over weeks. Patients often notice that their socks leave deep ridges or that their footwear feels progressively tighter by evening.
Acute Kidney Injury (AKI): In contrast, AKI represents a rapid, sudden decline in kidney function, often occurring over hours or a few days, triggered by factors such as severe dehydration, toxic drug exposures, sudden blood pressure drops, or acute infections. Because the kidneys abruptly stop filtering, fluid retention can happen with startling speed. Swelling in the feet, hands, and face may emerge rapidly alongside sudden, unexplained weight gain and a sharp reduction in daily urine output.
Diagnostic pathways: How physicians unravel Edema
When a patient presents with persistent lower-extremity edema, a clinician’s primary objective is to differentiate between nephrogenic fluid retention and alternative etiologies such as chronic venous insufficiency, congestive heart failure, or hepatic dysfunction. Because the physiological origins of swelling vary widely, a structured diagnostic protocol is deployed to evaluate renal integrity safely and accurately.
Initial clinical assessment and history
The evaluation begins with a meticulous medical history and physical examination. Clinicians pay close attention to the temporal patterns of the swelling:
Onset and progression: Rapid, acute swelling often points toward acute kidney injury (AKI), medication side effects, or deep vein thrombosis (DVT), whereas insidious, gradually worsening edema frequently correlates with chronic kidney disease (CKD) or heart failure.
Distribution and symmetry: Kidney-related edema is typically bilateral, affecting both feet and ankles symmetrically, and may be accompanied by facial puffiness or periorbital edema (especially upon waking). Unilateral swelling frequently signals a localized vascular or musculoskeletal issue, such as a venous clot.
Associated red-flag symptoms: Healthcare providers routinely screen for concurrent signs of systemic distress, including shortness of breath, orthopnea, foamy urine (a hallmark of proteinuria), gross hematuria, fatigue, and sudden, unexplained weight fluctuations.
Laboratory Investigations
If renal involvement is suspected, targeted laboratory testing provides objective data regarding filtration efficiency and systemic protein balance:
Serum Creatinine and eGFR: Blood tests measure waste products filtered by the kidneys. An elevated serum creatinine level coupled with a reduced estimated glomerular filtration rate (eGFR) indicates impaired renal clearance.
Urinalysis and Proteinuria Quantification: A routine dipstick test or a more precise urine albumin-to-creatinine ratio (uACR) test determines whether large molecules like albumin are leaking across damaged glomerular membranes. Persistent proteinuria is a primary marker for conditions like nephrotic syndrome or advanced diabetic nephropathy.
Comprehensive Metabolic Panel (CMP): Evaluates serum albumin and total protein levels. Hypoalbuminemia (low blood protein) strongly supports a diagnosis of nephrotic-range protein loss or hepatic synthetic dysfunction. Electrolyte levels are also reviewed to assess overall fluid and mineral homeostasis.
Differential diagnosis: Beyond the kidneys
While kidney disease remains a critical consideration, assuming that all pedal edema originates in the renal system can delay appropriate care for other serious conditions. A comprehensive expert review must weigh alternative origins:
Congestive Heart Failure (CHF): When the heart muscle struggles to pump efficiently, blood backs up in the venous circulation, raising hydrostatic pressure and forcing fluid into dependent tissues. CHF-related edema is frequently accompanied by exertional dyspnoea, orthopnea, and fatigue.
Chronic Venous Insufficiency (CVI): Valves within the lower-extremity veins weaken, causing blood to pool in the lower legs. This swelling is often accompanied by skin discoloration, varicose veins, and a dull ache that worsens with prolonged standing.
Medication-Induced Edema: A wide array of commonly prescribed drugs can disrupt fluid balance. Dihydropyridine calcium channel blockers (frequently used for hypertension), nonsteroidal anti-inflammatory drugs (NSAIDs), and certain hormonal therapies or steroids are notorious for causing peripheral fluid retention.
Hepatic Dysfunction: Cirrhosis or severe liver scarring impairs the production of vital proteins like albumin, decreasing oncotic pressure and encouraging fluid to shift into interstitial spaces, often presenting with ascites alongside lower-limb swelling.
Clinical management and interventions
Addressing edema rooted in kidney dysfunction requires a multifaceted strategy tailored to the underlying pathology, ranging from lifestyle modifications to advanced medical interventions.
Dietary modifications and sodium restriction
Because failing kidneys struggle to excrete excess sodium, dietary sodium restriction is a cornerstone of edema management. Limiting sodium intake reduces osmotic pressure within the extracellular matrix, helping to blunt the volume of fluid retained in the tissues. In certain advanced stages of renal disease, fluid restriction may also be recommended, though patients are explicitly advised never to restrict fluids without direct medical supervision, as unwarranted dehydration can further compromise renal perfusion.
Pharmacological Therapy
When lifestyle adjustments prove insufficient, physicians may introduce targeted pharmacotherapy:
Diuretics ("Water Pills"): Loop diuretics or thiazide-type diuretics are frequently prescribed to stimulate urinary sodium and water excretion, helping to relieve tissue congestion and lower intravascular volume.
Blood Pressure and Proteinuria Regulators: Angiotensin-converting enzyme (ACE) inhibitors or angiotensin II receptor blockers (ARBs) are often utilized to reduce intraglomerular pressure, slowing the progression of protein leakage and protecting long-term kidney architecture.
When to seek immediate medical attention
While mild, intermittent swelling of the feet can occasionally stem from benign causes like prolonged standing or mild heat exposure, certain presentations demand prompt clinical evaluation:
Sudden, painful swelling confined strictly to a single leg
Unexplained shortness of breath, chest pain, or respiratory distress
Rapid, marked weight gain over a period of several days
Noticeably reduced urine output or visibly foamy urine
Conclusion
Swollen feet can indeed serve as an outward warning sign of underlying kidney pathology, acting as a visible indicator of disrupted fluid regulation or glomerular protein loss. However, because edema is a shared symptom across numerous physiological systems, it should never be interpreted in isolation. Recognizing early patterns, monitoring accompanying shifts in urination or energy levels, and partnering with healthcare professionals for comprehensive diagnostic testing ensure that potential renal issues are identified and managed with precision.