The silent guardians of the body
These organs, each roughly the size of a fist, perform tasks so essential to everyday survival that life cannot be sustained without them or an artificial substitute like dialysis. Every single minute, approximately 20% of the body’s total blood supply pumps directly through them. Within this vascular network, an astonishing microscopic machinery filters waste products, regulates blood pressure, balances electrolyte levels, stimulates red blood cell production, and ensures the chemical composition of bodily fluids remains within a narrow, life-sustaining range.
Despite their monumental responsibilities, these organs are remarkably quiet workers. They can endure significant physiological stress and structural damage long before they broadcast distress signals to the rest of the body. This characteristic silence makes understanding the earliest phases of renal impairment a matter of paramount importance.
When people speak colloquially about "kidney failure," they are often referring to the end-stage spectrum of chronic kidney disease (CKD). However, clinical reality is far more nuanced. Renal decline does not happen overnight in the vast majority of cases; rather, it progresses along a continuous timeline divided into distinct stages.
The beginning of this journey, often termed Stage 1 chronic kidney disease, is a critical window of opportunity. It represents a period where damage may be present, but overall filtering capacity remains deceptively high. Recognizing, diagnosing, and acting upon the indicators of this initial stage can alter the trajectory of health, preventing progression toward advanced disease and preserving a high quality of life.
Defining the baseline: What do healthy Kidneys actually do?
To truly grasp what happens when the kidneys experience their earliest structural or functional disruptions, one must first appreciate the staggering complexity of normal renal physiology.
At the microscopic level, each kidney contains roughly one million tiny functional units called nephrons. A nephron is a marvel of biological engineering, consisting of a microscopic filtering cluster known as a glomerulus, which is attached to a long, winding tubule.
The Filtration and reabsorption process
Initial Filtration: As blood surges into the glomerulus under carefully regulated pressure, fluid and small molecules are forced through a specialized semi-permeable membrane. Larger structures, such as red blood cells, white blood cells, and vital plasma proteins, are retained within the bloodstream.
Tubular Processing: The filtered fluid, now called glomerular filtrate, enters the renal tubule. Here, the body performs a delicate balancing act. As the fluid travels through the tubule's various segments (including the proximal convoluted tubule, the loop of Henle, and the distal convoluted tubule), the tubular cells selectively reabsorb essential water, glucose, sodium, potassium, and amino acids back into the surrounding capillaries.
Secretion and Excretion: Simultaneously, the tubule actively secretes excess hydrogen ions, metabolic waste products, and foreign substances (such as certain medications) into the forming urine.
Beyond Filtration: Endocrine and Metabolic roles
While cleaning the blood is the most famous job of these organs, their endocrine functions are equally critical for daily well-being:
Blood Pressure Regulation: Through the production of an enzyme called renin, the kidneys help regulate blood volume and systemic vascular resistance via the renin-angiotensin-aldosterone system (RAAS).
Erythropoiesis (Red Blood Cell Production): When sensing low oxygen levels in the blood, specialized interstitial cells release erythropoietin (EPO), a hormone that signals the bone marrow to manufacture red blood cells.
Bone Health and Mineral Balance: The kidneys are responsible for activating vitamin D into its biologically active form (calcitriol), which in turn enables the intestines to absorb dietary calcium and phosphorus for strong, healthy bones.
When the kidneys enter Stage 1 impairment, these complex mechanical and chemical operations begin to face their first hurdles, even if the outward appearance of health remains undisturbed.
The classification framework: Understanding CKD stages
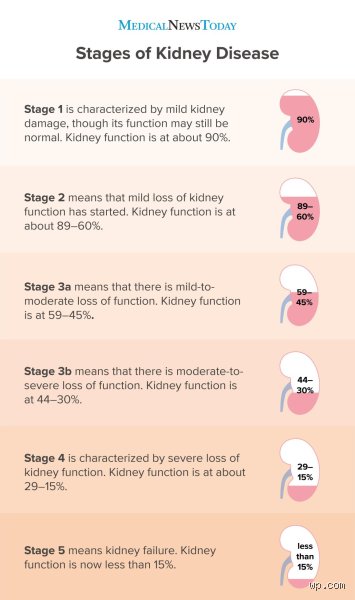
Before zooming in exclusively on the first stage, it is essential to understand how medical professionals map out the progression of renal decline. The National Kidney Foundation (NKF), alongside international nephrology bodies, utilizes the Kidney Disease: Improving Global Outcomes (KDIGO) guidelines to categorize chronic kidney disease into five distinct stages.
This staging system is primarily based on the Glomerular Filtration Rate (GFR), which is an estimate of how much blood passes through the glomeruli each minute, adjusted for body surface area. The standard unit of measurement for GFR is milliliters per minute per 1.73 m21.73 ext{ m}^21.73 m2 (mL/min/1.73m2mL/min/1.73 m^2mL/min/1.73m2).
| Stage | Description | GFR Range (mL/min/1.73m2) | Clinical Significance |
|---|---|---|---|
| Stage 1 | Normal or high GFR with structural or chemical damage | 90 or higher | Filtration rate is preserved, but markers of kidney damage (like protein in urine) are present. |
| Stage 2 | Mildly decreased GFR with damage | 60–89 | Slight drop in filtration efficiency accompanied by ongoing signs of injury. |
| Stage 3a / 3b | Moderately decreased GFR | 30–59 | Noticeable decline; risk of complications like anemia and mineral disorders begins to rise. |
| Stage 4 | Severely decreased GFR | 15–29 | Advanced decline; preparations for renal replacement therapy (dialysis or transplant) become critical. |
| Stage 5 | Kidney failure (End-Stage Renal Disease) | Less than 15 | Kidneys can no longer sustain life independently; dialysis or transplantation is required. |
As this table illustrates, Stage 1 occupies a unique and somewhat counterintuitive position: the GFR is technically within the "normal" range (90 or higher), yet the condition is classified as chronic kidney disease. Why? Because GFR alone does not tell the whole story. Kidney disease is defined not only by how much fluid is being filtered, but what is escaping through the filter that shouldn't be there.
Anatomy of Stage 1: High function, hidden vulnerability
Stage 1 chronic kidney disease is characterized by a paradox: the kidneys are still working at 90% to 100% (or even higher) of their estimated filtering capacity, yet structural, functional, or biochemical abnormalities have been detected.
To understand why this happens, we must look at how the kidneys compensate for early injury.
The Phenomenon of Hyperfiltration
When a subset of nephrons sustains damage, whether due to chronic high blood pressure, inflammation, or metabolic stress, the remaining healthy nephrons step up to pick up the slack. They undergo a process called hyperfiltration, expanding in size and increasing their workload to maintain the body's overall GFR.
While this adaptive mechanism is brilliant in the short term, it creates a dangerous long-term trap. The overworked, hyperfiltering nephrons are subjected to intense mechanical strain and elevated internal pressure. Over months and years, this relentless overwork damages the very nephrons keeping the GFR afloat, eventually causing them to burn out and scar. This initiates a slow, progressive domino effect where the burden shifts to fewer and fewer remaining nephrons, driving the transition from Stage 1 into subsequent stages.
Persistent albuminuria: The Red flag
Because the overall GFR in Stage 1 is often completely normal, clinicians rely heavily on another diagnostic marker to identify early injury: albuminuria (or proteinuria).
Albumin is a major blood plasma protein responsible for maintaining oncotic pressure (keeping fluid inside the blood vessels rather than leaking into surrounding tissues). In a healthy kidney, the filtration barrier's electrical charge and physical pore size prevent albumin from slipping out of the blood and into the urine.
However, when early injury occurs, often triggered by endothelial dysfunction, oxidative stress, or inflammation, the delicate architecture of the glomerular basement membrane is compromised. Tiny amounts of albumin begin to leak into the urine. This condition is clinically referred to as microalbuminuria or persistent albuminuria. Finding protein in the urine when GFR is normal is akin to finding soot coming out of a chimney; it tells an investigator that something inside is burning, even if the house appears fine from the outside.
Etiology: What triggers Stage 1 Renal impairment?
Chronic kidney disease rarely develops in a vacuum. Stage 1 is almost always the downstream consequence of systemic conditions that exert chronic stress on the delicate microvasculature of the kidneys. Understanding these underlying triggers is vital for anyone seeking to prevent or manage early renal decline.
1. Diabetes mellitus (type 1 and type 2)
Diabetes is the single leading cause of chronic kidney disease and kidney failure worldwide, accounting for nearly half of all new cases.
The Mechanism: Chronically elevated blood glucose levels (hyperglycemia) cause chemical alterations in blood vessel walls. Glucose molecules bind to proteins in a process called non-enzymatic glycation, forming advanced glycation end-products (AGEs). These compounds stiffen and damage the glomerular capillaries, altering their permeability and leading to diabetic nephropathy.
Stage 1 Connection: In the early phases of diabetic kidney disease, patients frequently exhibit hyperfiltration alongside microalbuminuria, placing them squarely in Stage 1 CKD.
2. Hypertension (chronic high Blood Pressure)
High blood pressure is both a primary cause and a frequent complication of kidney disease, creating a vicious cycle.
The Mechanism: The kidneys rely on a tightly regulated internal blood pressure to perform filtration. When systemic blood pressure remains chronically high, it transmits excessive pressure directly into the delicate glomerular capillary beds. This mechanical trauma thickens the arterial walls, reduces blood flow, and starves the surrounding kidney tissue of oxygen (ischemia).
Stage 1 Connection: Hypertensive nephrosclerosis often begins subtly, with mild vascular changes and subtle urinary protein leakage while the overall filtration rate remains normal.
3. Glomerulonephritis and autoimmune disorders
A diverse group of conditions characterized by direct inflammation of the glomeruli can initiate Stage 1 kidney disease.
The Mechanism: Conditions such as IgA nephropathy, lupus nephritis, or post-infectious glomerulonephritis involve the immune system attacking or depositing immune complexes within the renal tissue. This triggers an inflammatory cascade that damages the filtration barrier.
Stage 1 Connection: Because these inflammatory processes often start focally, they may preserve overall GFR initially while causing marked structural injury and hematuria (blood in the urine) or albuminuria.
4. Structural, genetic, and Congenital factors
Not all kidney disease stems from lifestyle or systemic metabolic disorders.
Polycyctic Kidney Disease (PKD): A genetic disorder characterized by the growth of numerous fluid-filled cysts in the kidneys. In its earliest phases, structural imaging may reveal these cysts long before overall filtration declines.
Congenital Anomalies: Anatomical abnormalities of the urinary tract, such as blockages or vesicoureteral reflux (where urine flows backward from the bladder toward the kidneys), can cause chronic back-pressure and recurrent infections, initiating early renal scarring.
The symptom paradox: Why Stage 1 goes unnoticed
One of the most challenging aspects of Stage 1 chronic kidney disease is the near-total absence of symptoms. Human biology is exceptionally resilient, and the body possesses vast physiological reserves.
Because the GFR is still 90 or higher, the kidneys are successfully performing their primary task: clearing metabolic waste products like urea and creatinine from the bloodstream. Consequently, routine blood tests measuring serum creatinine and Blood Urea Nitrogen (BUN) will often return results labeled as "normal."
Patients in Stage 1 almost never experience the classic warning signs associated with advanced kidney failure, such as:
Severe fluid retention (edema) in the legs, ankles, or face
Profound fatigue driven by uremic toxins and anemia
Persistent nausea, vomiting, or loss of appetite
Metallic taste in the mouth or ammonia-like breath
Severe bone pain or electrolyte imbalances
This silent nature means that Stage 1 kidney disease is rarely discovered through subjective physical discomfort. Instead, it is almost exclusively uncovered incidentally during routine medical evaluations, or through targeted screening in high-risk populations (such as individuals with longstanding diabetes or hypertension).
This reality underscores the vital importance of routine preventive healthcare. A simple annual wellness exam that includes a blood pressure check, a basic metabolic blood panel, and, crucially, a simple urine test to check for albumin can catch Stage 1 disease when it is most manageable.
Diagnostic pathways: How clinicians identify Stage 1
Because symptoms do not sound the alarm, modern medicine relies on specific diagnostic modalities to detect Stage 1 chronic kidney disease. A comprehensive evaluation by a primary care physician or a nephrologist involves a combination of laboratory tests and imaging studies.
Laboratory Markers
Urinalysis and Urine Albumin-to-Creatinine Ratio (UACR): This is the cornerstone of Stage 1 detection. A spot urine sample is analyzed to measure the exact amount of albumin relative to creatinine. A UACR of 30 mg/g30 ext{ mg/g}30 mg/g or higher, persisting over three months, confirms the presence of albuminuria and satisfies the diagnostic criteria for CKD, even if GFR is normal.
Serum Creatinine and Estimated GFR (eGFR): Creatinine is a natural byproduct of normal muscle breakdown that the kidneys filter out. Laboratories use serum creatinine levels, along with patient age, sex, and sometimes race, in mathematical formulas (such as the CKD-EPI equation) to calculate the eGFR. In Stage 1, this value will be ≥90 mL/min/1.73 m2\ge 90 ext{ mL/min}/1.73 ext{ m}^2≥90 mL/min/1.73 m2.
Hemoglobin A1c (HbA1c): Used to assess average blood glucose levels over the preceding three months, helping identify underlying diabetes as the root cause.
Comprehensive Metabolic Panel (CMP): Measures electrolytes (sodium, potassium, bicarbonate, chloride), calcium, phosphorus, and proteins to ensure systemic balance is maintained.
Imaging and Advanced diagnostics
Renal Ultrasound: A non-invasive imaging technique that allows clinicians to visualize the size, shape, and structure of the kidneys. In early-stage disease, the kidneys often appear normal in size, though structural anomalies, cysts, or signs of scarring can sometimes be identified.
Renal Biopsy: In cases where the exact underlying cause of Stage 1 disease is unclear, particularly when autoimmune glomerulonephritis is suspected, a nephrologist may perform a minimally invasive tissue biopsy. Examining a tiny core of kidney tissue under a microscope provides definitive insight into cellular damage and guides targeted treatment strategies.
The psychological and Lifestyle impact of an early diagnosis
Receiving a diagnosis of "chronic kidney disease" while still feeling completely healthy can be a jarring, emotionally complex experience for any individual. The word "chronic" carries weight, and the association between kidney failure and severe illness can trigger anxiety, confusion, and fear about the future.
However, reframing this diagnosis is essential for emotional well-being and proactive health management. Discovering kidney impairment at Stage 1 is not a sentence of inevitable decline; rather, it is a powerful early warning system.
Think of Stage 1 CKD much like discovering a dashboard warning light illuminating in an automobile. The car is still running smoothly, driving at highway speeds, and showing no mechanical failure. However, the light indicates that an internal component requires attention. Ignoring the light and continuing to drive without maintenance will eventually lead to a breakdown. Addressing the issue early, however, ensures the vehicle continues running reliably for hundreds of thousands of miles.
By confronting Stage 1 disease proactively, individuals gain a unique window of time during which lifestyle modifications, dietary adjustments, and precise medical management can halt, stabilize, or even partially reverse the underlying mechanisms of injury.
Forward look: The Foundation of early intervention
As we transition from understanding the baseline definition and diagnostic landscape of Stage 1 kidney failure into the actionable strategies required for its management, one central theme remains clear: proactive control is the ultimate protective shield.
The earliest phase of renal impairment is characterized by a delicate balance between cellular injury and compensatory mechanisms. Because the kidneys retain their filtering strength during this stage, interventions implemented now yield exponentially greater benefits than those initiated when nephrons are permanently lost.
In the subsequent sections of this clinical exploration, we will dig into the specific therapeutic approaches, dietary adjustments, blood pressure protocols, and emerging medical therapies designed to protect renal architecture, optimize systemic health, and ensure that the body's vital internal filtration plant continues operating smoothly for a lifetime.
Recognizing the invisible signs: Diagnostic pathways for Stage 1
Because Stage 1 kidney disease, medically classified as chronic kidney disease (CKD) with normal or high filtration function (an estimated glomerular filtration rate, or eGFR, of 90 mL/min/1.73 m2m^2m2 or higher), presents almost no physical symptoms, discovery usually relies on incidental findings during routine medical evaluations. Patients rarely feel sick, tired, or swollen, meaning the condition operates silently in the background.
Healthcare providers generally identify Stage 1 renal abnormalities through two primary screening tools:
Urine Albumin-to-Creatinine Ratio (uACR): This test measures the presence of albumin, a type of protein, leaking into the urine. Even if filtration rates are normal, persistent albuminuria (an ACR of 30 mg/g or higher) serves as a primary red flag indicating that the delicate filtering barriers (glomeruli) within the kidneys have sustained microscopic damage.
Imaging and Structural Analysis: Renal ultrasounds, CT scans, or MRIs can reveal structural defects, such as polycystic kidney disease, scarring, or anatomical blockages, confirming chronic damage despite normal filtration numbers.
Proactive Management and therapeutic interventions
Finding chronic kidney disease at its absolute earliest stage changes the long-term prognosis dramatically. Because the kidneys still possess vast functional reserves, timely interventions can halt, or even reverse, the progression toward advanced kidney failure.
+-------------------------------------------------------------+
| CORE STRATEGIES FOR STAGE 1 CKD |
+------------------------------+------------------------------+
| Medical Optimization | Lifestyle Adjustments |
+------------------------------+------------------------------+
| • Strict Blood Pressure Ctrl | • Sodium & Protein Moderation|
| • Glycemic Control (Diabetes)| • Regular Physical Activity |
| • Nephroprotective Meds | • Elimination of NSAIDs |
+------------------------------+------------------------------+
1. Controlling underlying drivers
The two most common precursors to chronic kidney disease are diabetes mellitus and hypertension (high blood pressure). Managing these conditions is paramount:
Blood Pressure Targets: Keeping blood pressure tightly controlled, typically below standard clinical thresholds such as 130/80 mmHg, reduces the hydrodynamic pressure forced against the tiny filtering units of the kidneys. Physicians often prescribe ACE inhibitors (angiotensin-converting enzyme inhibitors) or ARBs (angiotensin II receptor blockers), which uniquely lower pressure inside the kidney glomeruli and decrease protein leakage.
Blood Sugar Regulation: For individuals living with diabetes, maintaining strict glycemic control protects the microvascular networks feeding the renal tissues, preventing further scarring.
2. Dietary and Lifestyle modifications
Sodium Reduction: Restricting dietary salt intake helps manage systemic blood pressure and lessens fluid retention.
Protein Management: While high-protein diets are popular for fitness, excessive protein intake forces the kidneys to work harder via hyperfiltration. Moderating protein consumption under the guidance of a clinical dietitian relieves unnecessary renal stress.
Avoiding Nephrotoxic Agents: Routine or prolonged use of nonsteroidal anti-inflammatory drugs (NSAIDs) like ibuprofen, naproxen, or high-dose OTC painkillers can severely constrict blood flow to the kidneys. Stage 1 patients must seek safer alternative pain management strategies approved by their physician.
Long-Term outlook and prognosis
The term "kidney failure" often invokes immediate fear, but a diagnosis of Stage 1 CKD represents a critical window of opportunity rather than an inevitable descent into dialysis. Because overall filtration capacity remains robust, adhering to a proactive medical regimen allows many individuals to maintain stable kidney function across their entire lifespan.
Understanding Stage 1 emphasizes the importance of routine preventive health screenings, especially for individuals with risk factors like a family history of renal disease, hypertension, or diabetes. By respecting these early warning markers and partnering closely with healthcare providers, patients can preserve their renal health, protect cardiovascular function, and secure long-term vitality.