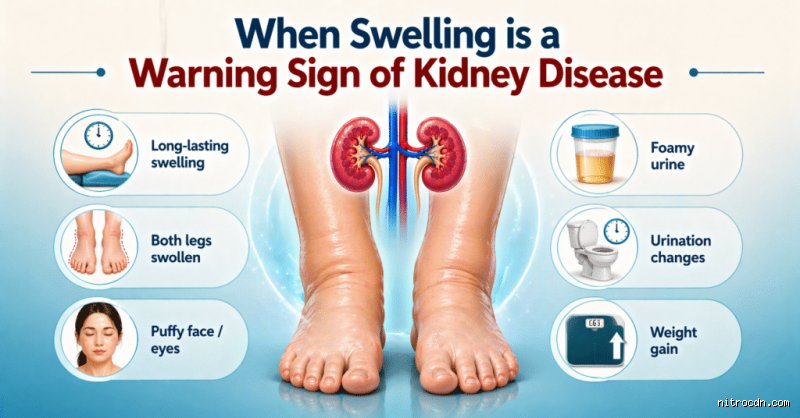
The renal connection: Why kidney disease causes foot swelling
To understand why compromised kidneys lead to swollen feet, one must first look at the fundamental role the kidneys play in maintaining homeostasis. Healthy kidneys act as sophisticated biological filters, processing approximately 200 quarts of blood daily to sift out waste products, excess minerals, and superfluous water. This waste and fluid are then converted into urine and excreted from the body.
When kidney disease sets in, whether due to diabetic nephropathy, chronic glomerulonephritis, hypertension, or other pathologies, the filtering units (nephrons) become damaged. This systemic disruption alters fluid and electrolyte handling in two primary ways:
Sodium and Water Retention: As the glomerular filtration rate (GFR) declines, the kidneys lose their efficiency in excreting dietary sodium and water. The body, sensing a relative deficit in effective circulating arterial volume, activates compensatory neurohormonal pathways such as the renin-angiotensin-aldosterone system (RAAS). This activation commands the kidneys to reabsorb even more sodium and water, expanding total body fluid volume and increasing hydrostatic pressure within the capillaries.
Proteinuria and Oncotic Pressure Disruption: Many forms of kidney disease damage the glomeruli's delicate basement membranes, causing large amounts of serum proteins, specifically albumin, to leak into the urine. Albumin acts like a sponge, holding fluid inside the blood vessels through a force called oncotic pressure (or colloid osmotic pressure). When blood albumin levels plummet (hypoalbuminemia), this crucial retaining force is lost. Fluid escapes the vascular space and leaks freely into the surrounding interstitial tissues, obeying gravity by pooling in the lowest points of the body: the feet and ankles.
Recognizing the signs: What kidney Edema looks and feels like
Not all swelling is created equal. Edema stemming from chronic kidney disease (CKD) or nephrotic syndrome exhibits distinct clinical characteristics that help differentiate it from venous insufficiency, lymphedema, or injury-related inflammation:
Bilateral Presentation: Unlike a sprained ankle or local trauma, kidney-related swelling typically affects both feet and ankles simultaneously, though gravity can cause one side to appear slightly more pronounced depending on posture.
Pitting Edema: A hallmark sign of fluid overload is "pitting." When you press your thumb firmly into the swollen skin for several seconds and release it, an indentation or "pit" remains visible for a brief period before the tissue slowly bounces back.
Taut, Shiny Skin: As fluid accumulates in the interstitial spaces, the overlying skin stretches, becoming tight, shiny, or cool to the touch.
Associated Symptoms: Because kidney disease is a systemic condition, peripheral edema rarely occurs in isolation. It is frequently accompanied by generalized fatigue, periorbital edema (puffiness around the eyes, especially noticeable in the morning), elevated blood pressure, and changes in urinary frequency or urine appearance (such as foamy urine caused by protein loss).
The diagnostic imperative: Evaluating the root cause
Before any intervention can safely or effectively target swollen feet, a thorough medical evaluation is non-negotiable. Self-treating swelling without knowing its origin can be dangerous, for instance, taking potent over-the-counter diuretics or drastically altering fluid intake without clinical guidance can precipitate acute kidney injury or electrolyte imbalances.
A comprehensive clinical workup typically involves:
Laboratory Testing: Serum creatinine and blood urea nitrogen (BUN) tests, coupled with estimated glomerular filtration rate (eGFR) calculations, to assess baseline renal function.
Urinalysis: Screening for proteinuria, microalbuminuria, and hematuria to detect glomerular damage.
Biomarker and Metabolic Panels: Checking serum albumin levels, electrolyte balances, and lipid profiles.
Imaging Studies: Renal ultrasounds to visualize kidney size, structure, and rule out structural obstructions.
Managing fluid Retention and swelling in advanced stages
When kidney disease progresses, the body's delicate internal equilibrium becomes disrupted, making the management of peripheral edema, commonly known as swollen feet and ankles, a daily clinical focus. As the filtration units of the kidneys (glomeruli) lose their structural integrity and functional mass, the body's ability to excrete excess sodium and water diminishes rapidly.
Understanding how to navigate this phase requires a comprehensive approach that combines medical interventions, rigorous dietary modifications, lifestyle adjustments, and continuous monitoring.
Pharmacological strategies and medical Management
Medical therapy is the cornerstone of controlling fluid overload resulting from renal impairment. When lifestyle modifications are no longer sufficient to manage swelling, nephrologists typically introduce specific pharmacological agents tailored to the patient's remaining kidney function and cardiovascular status.
1. Loop Diuretics and thiazides
Diuretics, commonly referred to as water pills, are prescribed to help the kidneys rid the body of excess sodium and water.
Loop Diuretics: Medications such as furosemide, bumetanide, and torsemide act on the ascending limb of the loop of Henle in the nephron. They are exceptionally potent and are typically the first-line treatment for moderate-to-severe edema associated with chronic kidney disease (CKD).
Thiazide Diuretics: Drugs like chlorthalidone or hydrochlorothiazide work further along the nephron in the distal convoluted tubule. In some cases, physicians may combine a loop diuretic with a thiazide diuretic to create "sequential nephron blockade," overcoming diuretic resistance when the kidneys are severely compromised.
2. Managing blood Pressure and Renin-Angiotensin-Aldosterone system (RAAS) inhibitors
Hypertension is both a cause and a consequence of kidney disease. Medications such as ACE inhibitors (angiotensin-converting enzyme inhibitors) or ARBs (angiotensin II receptor blockers) are frequently prescribed to protect the remaining nephrons by lowering pressure within the glomeruli. While these drugs are vital for long-term renal preservation, they can temporarily alter kidney function markers, requiring close monitoring by a healthcare professional.
Clinical Note: Never adjust, start, or stop diuretic or blood pressure medications without direct supervision from a nephrologist. Over-diuresis can lead to a sharp decline in residual kidney function and electrolyte imbalances.
Advanced dietary modifications
Dietary sodium and fluid restriction are powerful non-pharmacological tools for mitigating swollen feet. Because water naturally follows sodium in the body, consuming high amounts of salt triggers the retention of fluids, worsening peripheral edema.
Sodium Restriction
The Goal: Most nephrologists recommend limiting daily sodium intake to less than 2,000 milligrams (mg) per day, often lower depending on the severity of the edema and blood pressure readings.
Hidden The vast majority of dietary sodium does not come from the salt shaker, but from processed foods, canned soups, deli meats, restaurant meals, and condiments. Reading nutrition labels to identify sodium content is a critical daily habit.
Fluid Management
When kidney function drops significantly, the body cannot process large volumes of liquid.
Tracking Intake: Patients with advanced CKD or those on dialysis are often prescribed a specific daily fluid allowance. This limit includes all liquids consumed, as well as foods that turn to liquid at room temperature, such as gelatin, ice cream, and soups.
Thirst Management: To cope with fluid restrictions without feeling perpetually parched, patients can try sucking on ice chips (measuring the melted volume), chewing sugar-free gum, or rinsing the mouth with water without swallowing.
Practical physical therapies and home care
In addition to medical and dietary controls, physical strategies can help manage the daily discomfort of swollen feet and improve localized circulation.
1. Elevation Techniques
Gravity plays a significant role in fluid accumulation in the lower extremities.
Elevating the feet above the level of the heart for 15 to 30 minutes several times a day uses gravity to help drain accumulated interstitial fluid back toward the circulatory system.
Prop pillows underneath the calves and heels while resting or sleeping to ensure proper alignment and effective drainage.
2. Compression therapy (with medical caution)
Compression stockings or wraps apply gentle, graduated pressure to the lower legs, preventing fluid from pooling in the ankles and feet.
Crucial Warning: Compression therapy should never be used without explicit clearance from a physician or nephrologist. If the swelling is caused by severe heart failure alongside kidney disease, or if there is peripheral arterial disease, compression can be dangerous.
3. Gentle movement and exercise
Inactivity can exacerbate fluid pooling. Engaging in low-impact physical activities approved by a physician, such as swimming, stationary cycling, or gentle walking, activates the calf muscle pump, which naturally assists veins and lymphatic vessels in pushing fluid back upward against gravity.
Monitoring and recognizing Warning signs
Living with kidney-related edema requires vigilance. Daily habits can prevent minor swelling from escalating into a dangerous medical emergency.
| Monitoring Parameter | Recommended Action | What to Watch For |
|---|---|---|
| Daily Weight | Weigh yourself at the same time every morning using the same scale, wearing similar clothing. | A sudden gain of 2 to 3 pounds (or more) over 1 to 2 days often indicates rapid fluid retention rather than actual tissue growth. |
| Pitting Edema Check | Press a finger gently against the swollen skin of the shin or ankle for 5 seconds. | Observe if an indentation (pit) remains after releasing the finger. Deeper or longer-lasting pits suggest worsening fluid overload. |
| Symptom Tracking | Keep a daily log of swelling levels, fluid intake, and medication adherence. | Note any new symptoms like shortness of breath, chest pain, or rapid fatigue. |
When to seek immediate emergency care
While chronic swelling is a standard aspect of managed kidney disease, certain symptoms indicate acute complications, such as pulmonary edema (fluid in the lungs) or acute kidney injury, that require immediate emergency medical attention:
Sudden, severe shortness of breath or difficulty breathing, especially when lying flat.
Chest pain, pressure, or irregular heart rhythms.
Rapid, unexplained weight gain accompanied by swelling that extends up into the thighs, abdomen, or face.
Confusion, extreme lethargy, or altered mental state, which can signal severe electrolyte imbalances or uremic buildup.
Managing swollen feet from kidney disease is an ongoing partnership between the patient, nephrologist, dietitian, and care team. By combining precise medication adherence, strict sodium and fluid awareness, and proactive daily monitoring, individuals can significantly improve their comfort, protect their cardiovascular health, and maintain a higher quality of life.