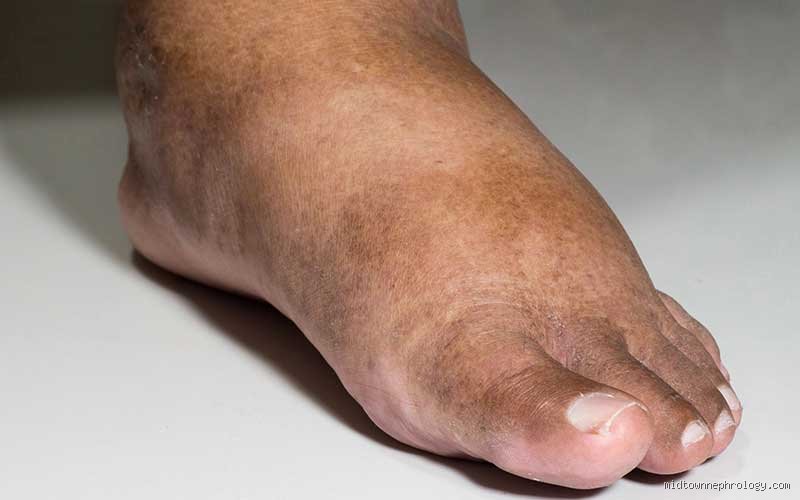
Astonishingly, some of the earliest and most telling indicators of renal dysfunction manifest far away from the lower back, appearing instead in the body’s most distant extremities: the feet and ankles. Because gravity naturally pulls fluid downward and poor circulation compounds systemic inflammation, the feet act as an early warning system for failing internal homeostasis.
Understanding these podiatric warning signs is crucial for early detection, potentially halting or slowing the progression of chronic kidney disease (CKD) before it reaches irreversible stages. Below is an in-depth, expert exploration of the primary symptoms of kidney disease that present in the feet, the physiological mechanisms driving them, and why paying attention to your feet could ultimately save your life.
1. Peripheral Edema: The hallmark Fluid retention
The most common and visually recognizable foot symptom associated with kidney disease is peripheral edema, a medical term for swelling caused by a buildup of fluid in the tissues of the lower extremities.
The Physiological Mechanism
Healthy kidneys act as precision filters, processing roughly 120 to 150 quarts of blood daily to sift out about 1 to 2 quarts of waste products and excess water, which are then expelled as urine. When kidney function declines due to conditions like diabetic nephropathy, hypertension, or glomerulonephritis, the kidneys lose their efficiency.
As filtration slows down, sodium and water begin to accumulate in the bloodstream. As protein leaks into the urine (a condition known as proteinuria, discussed in detail later), the oncotic pressure within the blood vessels drops. This causes fluid to escape from the capillaries and seep into the surrounding interstitial tissues. Because of gravity, this excess fluid pools primarily in the lowest points of the body: the feet, ankles, and lower calves.
What it looks and feels like
Pitting Edema: When you press a finger firmly into the swollen skin of your foot or ankle for a few seconds and release it, an indentation (or "pit") remains for a noticeable amount of time before the skin springs back.
Tight, Shiny Skin: The skin over the top of the foot and around the ankle may appear stretched, glossy, or taut due to the internal pressure of the trapped fluid.
Footwear Difficulty: Shoes that previously fit comfortably may suddenly feel tight, restrictive, or painful by midday, making it difficult to lace up sneakers or slip into dress shoes.
Asymmetry or Symmetry: While swelling can sometimes affect one foot more than true injury-related swelling, kidney-related edema typically presents bilaterally, affecting both feet and ankles equally.
2. Proteinuria-Induced hypoalbuminemia and lower extremity swelling
While general fluid retention is linked to overall salt and water balance, a specific subtype of kidney damage directly accelerates swelling through blood chemistry alterations.
The Role of Albumin
Albumin is a major protein manufactured by the liver that circulates in the blood. One of its primary jobs is to act like a sponge, holding fluid inside the blood vessels so it does not leak into body tissues. Healthy kidneys have microscopic filters called glomeruli that contain tiny blood vessels; these filters let waste products and excess fluid pass into the urine while keeping vital components like protein (albumin) in the bloodstream.
When these glomeruli become damaged or scarred, they develop microscopic gaps, allowing large amounts of albumin to leak out into the urine. This condition is called proteinuria or albuminuria.
The Cascade to the Feet
As albumin levels in the blood plummet (a state called hypoalbuminemia), the blood loses its capacity to draw fluid back into the circulatory system from the tissues. Consequently, gravity pulls the uncontained fluid down into the lower body. For individuals experiencing unexplained, persistent foot swelling, a simple routine urinalysis to check for albumin-to-creatinine ratio (ACR) is often the diagnostic key that uncovers hidden glomerular damage.
3. Peripheral neuropathy: Numbness, tingling, and burning soles
Kidney disease does not just affect fluid balance; it also profoundly impacts the nervous system. As renal function deteriorates, metabolic wastes that the kidneys should have filtered out build up in the bloodstream, a toxic state known as uremia.
Uremic Neuropathy
Uremic toxins can damage peripheral nerves throughout the body, most commonly targeting the longest nerves first. Because the nerves traveling from the spinal cord down to the toes are the longest in the human body, the feet are often the first place nerve damage (neuropathy) manifests.
Symptoms in the Feet
Numbness and Loss of Sensation: Patients may describe a "pins and needles" sensation, or a feeling as though they are perpetually wearing thick, invisible socks even when barefoot.
Burning or Stabbing Pain: Particularly prevalent at night or during periods of rest, uremic neuropathy can cause intense burning sensations, sharp shooting pains, or deep aches in the soles of the feet and toes.
Loss of Proprioception: Advanced nerve damage can impair the foot's ability to sense position, vibration, or temperature, which dramatically increases the risk of accidental injuries, cuts, or burns going unnoticed.
4. Pruritus: Severe, unrelenting itching of the Feet and ankles
Itching is a surprisingly common yet frequently misunderstood symptom of advanced chronic kidney disease. Known medically as uremic pruritus or chronic kidney disease-associated pruritus (CKD-aP), this is not a simple dry skin issue that can be solved with standard lotion.
Why It Happens
When the kidneys fail, they can no longer maintain proper mineral homeostasis, particularly regarding phosphorus and calcium. High blood levels of phosphorus (hyperphosphatemia) lead to secondary hyperparathyroidism, where the parathyroid glands work overtime to balance minerals, often pulling calcium out of the bones.
The excess calcium and phosphorus complexes circulate in the bloodstream and deposit in various tissues, including the skin and small nerve endings in the feet. Histamine release and immune system dysregulation in uremic states amplify the sensation of itchiness.
Manifestation in the lower extremities
While uremic pruritus can affect the entire body, patients frequently report intense, deep-seated itching concentrated on the lower legs, ankles, and the soles of the feet. The urge to scratch can be so severe that it leads to skin breakdown, excoriation marks, and secondary bacterial infections, complicating foot health further, especially in diabetic patients.
5. Peripheral Arterial Disease (PAD) and Vascular calcification
Kidney disease and cardiovascular health are deeply intertwined through a bidirectional relationship known as the cardiorenal syndrome. Patients with CKD experience accelerated vascular aging, arterial stiffening, and calcification.
The calciphylaxis and PAD connection
Abnormal mineral metabolism (high calcium-phosphate product) causes calcium deposits to build up not only in the heart valves and major arteries but also in the peripheral blood vessels supplying the lower legs and feet.
This contributes to Peripheral Arterial Disease (PAD), where narrowed arteries restrict blood flow to the lower extremities.
Foot symptoms of compromised circulation
Cold Feet: Chronically cold toes and feet, regardless of ambient room temperature or warm socks, due to inadequate arterial perfusion.
Intermittent Claudication: Cramping, aching, or fatigue in the feet and calves that occurs during walking or physical exertion and subsides with rest.
Skin and Nail Changes: Thin, shiny, hairless skin on the feet and toes, coupled with slow-growing, thickened, or brittle toenails.
Delayed Healing: Minor cuts, blisters, or scratches on the feet taking weeks or months to heal, which significantly elevates the risk of ulceration and infection.
6. Uremic fetor and Changes in Foot odor
While less common as a primary podiatric complaint, metabolic shifts in advanced kidney disease can alter bodily secretions, including sweat. Uremia causes urea and other nitrogenous wastes to be excreted through sweat glands and saliva.
Some patients note a strange, pungent, or ammonia-like odor emanating from their feet even shortly after washing. While this is primarily an indicator of systemic uremia rather than a localized foot pathology, it serves as an olfactory red flag for profound metabolic distress.
7. Muscle Cramps and Restless Legs in the lower extremities
Electrolyte imbalances are an inevitable consequence of failing kidneys. The kidneys are responsible for fine-tuning levels of sodium, potassium, calcium, and magnesium.
The Electrolyte-Cramp Connection
When renal clearance drops, electrolyte dysregulation occurs. Low calcium, abnormal magnesium levels, and fluctuating potassium can make nerve endings hyper-excitable and trigger painful, involuntary muscle spasms.
Nocturnal Foot and Toe Cramps: Sudden, violent contractions of the muscles in the arch of the foot or toes, frequently waking patients up in the middle of the night.
Restless Legs Syndrome (RLS): An overwhelming, uncomfortable urge to move the legs and feet, often accompanied by crawling, creeping, or pulling sensations that worsen during periods of rest or inactivity in the evening. RLS is exponentially more common in individuals with end-stage renal disease (ESRD).
Summary and diagnostic imperatives
The feet serve as an intricate biological dashboard, often flashing early warning lights when internal organs begin to falter. From pitting edema and relentless itching to neuropathic numbness and circulation deficits, the symptoms of kidney disease in the feet span multiple physiological systems.
Because many of these signs overlap with other common conditions, such as simple fatigue, normal aging, peripheral neuropathy from diabetes, or venous insufficiency, they are frequently dismissed until kidney damage has advanced significantly.
Recognizing these symptoms early empowers patients and healthcare providers to perform targeted diagnostic testing, such as a serum creatinine blood test (to calculate estimated glomerular filtration rate, or eGFR) and a spot urine test (to check for albuminuria). Catching kidney disease in its formative stages allows for timely dietary modifications, blood pressure management, glycemic control, and pharmaceutical interventions that can protect remaining renal function and preserve overall health.
Understanding Peripheral neuropathy: When toxins disrupt nerve function
While fluid retention and visible swelling (edema) represent the most recognizable hemodynamic manifestations of declining renal function, chronic kidney disease (CKD) exerts an equally profound, albeit less visible, toll on the peripheral nervous system. As the glomerular filtration rate (GFR) drops and uremic toxins accumulate in the systemic circulation, they begin to exert direct neurotoxic effects. This condition, frequently referred to as uremic neuropathy, affects a significant percentage of patients with advanced CKD or end-stage renal disease (ESRD).
The symptoms in the feet typically manifest symmetrically, starting in the distal toes and gradually ascending. Patients frequently report:
Paresthesias: Abnormal sensations such as persistent "pins and needles," crawling, or electrical tingling.
Dysesthesia: Unpleasant, distorted sensations, including a paradoxical heat sensation where cool surfaces feel burning hot, or vice-versa.
Deep Muscular Aching and Restless Legs: Chronic cramping and nocturnal discomfort that severely disrupts restorative sleep, compounding the fatigue inherent to renal failure.
Loss of Protective Sensation: Perhaps the most perilous consequence of chronic nerve damage is the gradual blunting of pain, temperature, and vibration perception. When a patient loses protective sensation, they may step on sharp objects, develop friction blisters from ill-fitting shoes, or experience thermal burns without feeling acute pain. This absence of warning signals creates a pathway for silent injuries to progress into severe, chronic wounds.
Many individuals with CKD also suffer from diabetic nephropathy, the leading cause of renal failure worldwide. When diabetes coexists with chronic kidney disease, the risk of multi-factorial peripheral neuropathy multiplies exponentially, accelerating the degradation of nerve fibers and increasing vulnerability to foot complications.
Vascular compromise and ischaemia in the lower extremities
Beyond fluid overload and neurotoxicity, kidney disease is deeply intertwined with systemic vascular pathology. Chronic renal impairment promotes accelerated atherosclerosis, arterial stiffening, and endothelial dysfunction. This vascular degradation severely compromises macrocirculation and microcirculation in the lower limbs, leading to peripheral arterial disease (PAD), or renal-associated ischaemia.
When blood flow to the feet is restricted, the tissues are starved of oxygen and vital nutrients necessary for normal cellular maintenance and repair. Clinical indicators of vascular compromise in the feet include:
Reduced Skin Temperature: Feet that feel persistently cold to the touch, independent of ambient room temperature.
Trophic Changes: Thin, shiny, or hairless skin on the dorsum of the foot and toes, accompanied by thickened, brittle toenails that grow slowly.
Claudication and Pain at Rest: Cramping, aching, or fatigue in the feet and calves during physical exertion (intermittent claudication) that resolves with rest, or in advanced cases, persistent rest pain that worsens when lying flat at night.
Prolonged Capillary Refill Time: Delayed return of color to the nail beds after gentle pressure is applied, indicating sluggish superficial blood flow.
Ischaemia radically alters the body's capacity to heal. Even minor abrasions or pressure spots require a robust blood supply to deliver white blood cells, nutrients, and building blocks for tissue regeneration. In the presence of CKD-induced vascular disease, these repair mechanisms fail, transforming minor surface trauma into chronic, non-healing ulcers.
Cascading risks: Ulceration, infection, and Charcot arthropathy
The convergence of peripheral neuropathy (loss of sensation) and ischaemia (poor blood supply) creates a clinical triad, often compounded by impaired immune function due to uremia, that places the feet of kidney disease patients at extreme risk.
1. Chronic Foot ulceration
Because patients cannot feel localized pressure points, friction, or minor cuts, injuries go unnoticed. Weight-bearing forces continuously press against these vulnerable areas, leading to tissue breakdown and open ulcers, which frequently develop beneath hard calluses or areas of hyperkeratosis.
2. Deep tissue infection and osteomyelitis
Compromised immune responses in CKD mean that bacterial invaders encounter little resistance. What begins as a superficial skin break can rapidly spread into deep fascial planes, tendon sheaths, and underlying bone (osteomyelitis). Because systemic signs of infection like fever may be blunted in uremic patients, localized red flags, such as subtle warmth, localized swelling, foul odor, or purulent discharge, must be treated as absolute medical emergencies.
3. Charcot Neuroarthropathy
A less common but devastating complication in neuropathic feet is Charcot foot. This degenerative condition involves progressive destruction of the bones and joints of the foot, typically triggered by minor trauma that the patient fails to notice due to sensory loss. The foot becomes acutely warm, swollen, and erythematous, and without immediate immobilization, the structural architecture collapses, resulting in permanent rocker-bottom deformities that drastically elevate amputation risks.
Comprehensive diagnostic workup: Evaluating Foot symptoms in Renal patients
When a patient presents with foot symptoms in the context of known or suspected kidney disease, a coordinated diagnostic approach is essential. Clinicians must differentiate between primary dermatological or orthopedic issues and those driven by systemic renal pathology.
Laboratory Assessment: Evaluation begins with a comprehensive metabolic panel to check serum creatinine, blood urea nitrogen (BUN), and estimated glomerular filtration rate (eGFR). Urine testing, specifically the urine protein-to-creatinine ratio (UPCR) or albumin-to-creatinine ratio (ACR), helps identify protein-leaking nephropathies like nephrotic syndrome. Electrolyte panels assess calcium, phosphorus, and potassium balance, which directly influence muscle cramping and nerve excitability.
Vascular Studies: Non-invasive vascular testing, including ankle-brachial indices (ABIs), toe-brachial indices (TBIs), and Doppler ultrasound imaging, maps arterial blood flow and quantifies the severity of lower extremity ischaemia.
Neurological Examination: Monofilament testing, tuning fork vibration tests, and nerve conduction studies evaluate the integrity of sensory pathways and quantify peripheral nerve damage.
Imaging for Bone and Joint Integrity: Plain radiography, MRI, or bone scans are deployed when osteomyelitis, stress fractures, or early Charcot arthropathy are suspected beneath swollen or ulcerated tissue.
Proactive Management and specialized Foot care protocols
Preventing catastrophic foot outcomes in chronic kidney disease requires a proactive, multidisciplinary strategy involving nephrologists, primary care physicians, certified podiatrists, and vascular specialists.
Daily Self-Care and inspection routine
Visual and Tactile Checks: Inspect the feet daily, including the soles and the spaces between the toes, looking for cuts, bruises, blisters, discoloration, or temperature disparities. Patients with visual impairments should enlist a family member or caregiver for assistance.
Gentle Cleansing and Moisture Regulation: Wash feet daily in lukewarm water (tested safely with an elbow to avoid thermal burns if sensation is compromised) and dry thoroughly. Apply a hydrating cream to dry skin to prevent cracking, but strictly avoid applying lotion between the toes, as excess moisture promotes fungal infections and skin maceration.
Protective Footwear: Never walking barefoot, even indoors, eliminates the risk of accidental punctures. Shoes must be professionally measured and fitted to accommodate foot shape changes, featuring seamless interiors and adequate depth to prevent pressure points.
Medical and interventional strategies
Optimizing Metabolic Control: Rigorous management of blood pressure, glycemic control (for diabetic patients), and lipid profiles slows the progression of vascular damage.
Renal Diet and Fluid Management: Adhering to nephrology-guided sodium, fluid, and mineral restrictions minimizes systemic edema and controls electrolyte imbalances that provoke painful muscle cramps.
Regular Podiatric Screening: Patients with CKD stages 3 through 5 should undergo regular clinical foot assessments by a podiatrist every one to two months to manage calluses professionally, evaluate neuropathy scores, and detect early vascular compromise before ulcers develop.
Conclusion
Foot symptoms associated with kidney disease, ranging from the deceptively simple discomfort of evening ankle swelling to severe peripheral neuropathy, vascular ischaemia, and non-healing ulcers, serve as vital windows into systemic health. Because renal decline compromises fluid homeostasis, nerve integrity, and vascular perfusion, the lower extremities often act as early warning indicators of advanced systemic stress. Through vigilant daily self-care, rigorous management of underlying metabolic and renal parameters, and prompt multidisciplinary intervention at the first sign of structural or circulatory changes, patients can successfully safeguard mobility, preserve tissue integrity, and significantly mitigate long-term complications.