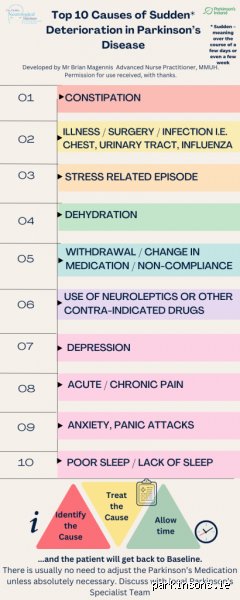
Understanding the trajectory: Can Parkinson’s symptoms worsen suddenly?
Yet, clinical reality frequently challenges this expectation. It is startlingly common for a person with Parkinson’s to experience a sharp, dramatic, and seemingly overnight intensification of their symptoms. A patient who was walking independently and managing daily tasks with relative ease last week might suddenly find themselves bedbound, struggling intensely with speech, facing severe rigidity, or exhibiting acute confusion. This abrupt shift can trigger immense anxiety, often leading families to fear that the underlying disease has suddenly accelerated into its final stages.
The essential clinical truth, however, is far more nuanced: while the neurodegenerative progression of Parkinson’s remains inherently gradual, acute, sudden worsening is almost always driven by a secondary, external trigger or a distinct physiological disruption. Recognizing that these sharp declines are typically reactive, and frequently reversible, transforms how patients, caregivers, and medical professionals approach crisis management.
The illusion of Rapid Progression: Differentiating Disease evolution from Acute exacerbations
To understand why Parkinson’s symptoms can plummet overnight, one must first separate the chronic trajectory of the disease from acute motor exacerbations. Chronic progression involves the permanent loss of neural circuitry and the brain’s diminishing capacity to compensate for depleted dopamine levels. This process manifests over months and years.
Conversely, an acute exacerbation represents a temporary or sudden functional drop caused by a systemic stressor acting upon an already vulnerable neurological system. Think of the baseline Parkinson’s brain as operating on a narrow margin of physiological stability. Because the brain's neurochemical reserves are already compromised, it has a reduced buffer to handle additional systemic shocks. When a secondary event occurs, such as a mild infection, a severe lack of sleep, or a disruption in medication timing, the system tips over, resulting in a sudden explosion of severe motor and cognitive symptoms.
Crucially, studies and clinical observations indicate that a vast majority of these sudden downturns are treatable. When the underlying trigger is correctly identified and aggressively managed, many patients return entirely or very close to their previous baseline. Mistaking a temporary, reactive crisis for permanent disease progression can lead to misplaced despair and inappropriate long-term care adjustments, making the identification of acute triggers an urgent clinical priority.
Physiological culprits: Infections, Inflammation, and the immune response
Among the most common catalysts for a sudden, dramatic worsening of Parkinson’s symptoms is an intercurrent infection. Even a minor infection that might cause only mild fatigue in a healthy individual can wreak havoc on a patient with Parkinson’s.
Urinary Tract Infections (UTIs) and Respiratory illnesses
Urinary tract infections and chest infections (such as mild bronchitis or pneumonia) are infamous for triggering acute neurological decline in older adults, particularly those with neurodegenerative conditions. When the body mounts an immune response against an infection, it releases inflammatory signaling molecules known as cytokines. These systemic inflammatory chemicals cross the blood-brain barrier, triggering neuroinflammation.
In a Parkinson’s patient, this inflammatory surge disrupts delicate neurotransmitter balances, leading directly to:
Severe Motor Fluctuations: Sudden increases in tremors, profound muscle stiffness, and an inability to initiate movement (freezing episodes).
Acute Confusion and Delirium: A rapid onset of disorientation, hallucinations, or paranoid delusions that can mimic severe psychiatric episodes or advanced dementia.
Caregivers often notice that a sudden change in mental state or movement ability precedes any traditional physical signs of a UTI, making a medical evaluation and urine screen the first essential step when an abrupt decline occurs.
Pharmacological pitfalls: Medication timing, Interactions, and "off" periods
Because Parkinson’s management relies heavily on exogenous dopamine replacement therapies (such as levodopa), the central nervous system is exceptionally sensitive to alterations in how these drugs are processed, absorbed, or timed. Pharmacological disruptions are a leading cause of sudden, alarming symptom spikes.
The perils of Medication timing and consistency
The brain of a person with advanced or even moderate Parkinson’s loses its ability to store dopamine effectively. It relies on a steady, rhythmic supply of medication to maintain smooth motor function.
Delayed Doses: Missing a dose by even 30 to 60 minutes, or taking medications irregularly, can plunge a patient into a severe "off" period, where mobility vanishes and rigidity takes over.
Gastrointestinal Absorption Issues: Levodopa is absorbed primarily in the small intestine. If a patient suffers from delayed gastric emptying or severe constipation, both extremely common non-motor symptoms of Parkinson’s, the medication may sit in the stomach instead of reaching the bloodstream, rendering the dose completely ineffective and causing an unexpected, sudden crash in mobility.
Dangerous Drug Interactions
The introduction of new medications prescribed for other health issues can also trigger a catastrophic clash with Parkinson’s treatments. For instance, certain anti-nausea drugs (dopamine blockers like metoclopramide), typical and atypical antipsychotics, and specific muscle relaxants can directly counteract levodopa, precipitating an acute and dangerous worsening of motor symptoms.
Metabolic, environmental, and Psychological stressors
Beyond infections and medication errors, a wide array of everyday physical and emotional stressors can rapidly destabilize a Parkinson’s patient.
Dehydration: Inadequate fluid intake reduces blood volume and impairs systemic circulation. In Parkinson’s, where autonomic nervous system dysfunction is already present, dehydration frequently leads to orthostatic hypotension (sudden drops in blood pressure upon standing), causing dizziness, severe fatigue, and an increased risk of falls that can compound functional decline.
Severe Psychological Stress and Anxiety: Emotional trauma, panic, prolonged anxiety, or even sudden changes in environment (such as moving to a new room or hospital admission) trigger a surge of stress hormones like cortisol and adrenaline. This neurochemical flood dramatically exacerbates motor symptoms, particularly tremors and rigidity.
Sleep Deprivation: Chronic or acute lack of restorative sleep, often driven by nocturnal motor symptoms, vivid dreams, or frequent nighttime urination, lowers the brain's threshold for handling physical stress, manifesting as a sharp drop in daytime functional capacity.
Navigating Acute shifts: Managing and Mitigating Sudden Parkinsonian deterioration
While Parkinson's disease (PD) is classically understood as a slowly evolving, chronic neurodegenerative condition, the daily reality for patients and caregivers often involves sudden, alarming fluctuations. Witnessing a loved one, or experiencing firsthand, a rapid, overnight intensification of stiffness, tremors, cognitive fog, or mobility failure can be profoundly distressing. Understanding that these sudden drops in function are frequently reversible requires looking beyond the underlying neurodegeneration to identify acute external triggers.
The intersection of systemic health and brain function
The brain of an individual with Parkinson’s operates with a reduced physiological reserve due to depleted dopamine pathways. Consequently, minor systemic stressors that a healthy nervous system easily absorbs can severely compromise a compromised dopaminergic network.
1. The hidden impact of Infections
An occult infection, most commonly a urinary tract infection (UTI) or a mild respiratory bug, is one of the most frequent culprits behind a sudden functional decline. The body mounts an inflammatory immune response, releasing cytokines that cross the blood-brain barrier. In a Parkinsonian brain, this systemic inflammation disrupts neurotransmitter signaling, instantly magnifying motor symptoms, inducing profound fatigue, and frequently triggering acute confusion or delirium.
2. Pharmacological disruption and contraindications
Medication timing, absorption, and interactions dictate day-to-day stability.
The Gut-Brain Connection: Levodopa relies heavily on efficient gastric emptying and intestinal absorption. Conditions like severe constipation can physically block or delay medication uptake, rendering standard doses ineffective and precipitating prolonged, severe "off" periods.
Adverse Drug Interactions: The inadvertent introduction of dopamine-blocking agents, such as certain anti-nausea medications (e.g., metoclopramide) or typical antipsychotics, can provoke a dramatic, dangerous intensification of rigidity and immobility that mimics rapid disease progression.
3. Metabolic and environmental stressors
Dehydration, profound sleep deprivation, acute psychological stress, and sudden environmental temperature shifts severely challenge autonomic and motor control. Dehydration thickens blood, alters electrolyte balances, and impairs the cellular distribution of remaining therapeutics, leading to orthostatic drops and sudden weakness.
Diagnostic evaluation: Distinguishing Fluctuation from Progression
When an acute setback occurs, neurologists and movement disorder specialists look for specific clinical indicators to determine whether the change is a temporary, treatable setback or a true milestone in disease advancement.
| Clinical Feature | Acute Fluctuation / Transient Setback | True Disease Progression |
|---|---|---|
| Onset | Abrupt (hours to days) | Gradual (months to years) |
| Primary Triggers | Infection, constipation, missed medication, stress | Underlying neuronal loss, natural evolution of pathology |
| Reversibility | Highly reversible upon treating the root cause | Permanent baseline shift requiring long-term adjustment |
| Cognitive Component | Often presents as fluctuating delirium or acute confusion | Stable or progressively declining chronic cognitive impairment |
Proactive strategies for caregivers and patients
Mitigating the risk of sudden neurological crashes involves establishing resilient daily routines and monitoring systems:
Strict Medication Adherence: Maintain rigid adherence to prescribed dosing schedules. Even a 30-minute deviation can trigger breakthrough symptoms in sensitive individuals. Always administer oral treatments with adequate water to optimize dissolution and gastrointestinal transit.
Bowel and Hydration Tracking: Because gastrointestinal motility is universally sluggish in PD, aggressively managing hydration and fiber## Acute Worsening vs. Disease Progression: Navigating Sudden Changes in Parkinson’s
While Parkinson’s disease (PD) is fundamentally characterized by a gradual, progressive decline over years, patients, caregivers, and clinicians frequently encounter moments where symptoms seem to accelerate overnight. Understanding the critical distinction between long-term neurodegeneration and acute symptom exacerbation is essential for effective clinical management, preventing unnecessary emergency department visits, and safeguarding quality of life.
Precipitating factors: Unraveling the causes of Sudden deterioration
When a person with Parkinson's experiences an abrupt and sharp worsening of motor or non-motor symptoms, it is rarely a sign that the underlying disease has suddenly advanced by several years. Instead, acute fluctuations are almost always triggered by external stressors, physiological disruptions, or medication misalignments. Identifying these triggers requires a systematic clinical investigation.
1. Systemic Infections and illnesses
Even mild infections can have a profound impact on the central nervous system of an individual with Parkinson's.
Urinary Tract Infections (UTIs): UTIs are perhaps the most common culprit behind sudden cognitive decline, severe confusion (delirium), and abrupt motor deterioration in older adults with PD.
Respiratory Infections: Pneumonia, bronchitis, or even common viral infections place physiological stress on the body, frequently resulting in profound fatigue, increased rigidity, and a temporary loss of mobility.
Fever and Inflammation: Elevated body temperature alters metabolic rates and can interfere with the brain's delicate neurotransmitter balance, temporarily rendering standard dopaminergic therapies less effective.
2. Medication management errors and timing
The brain of a person with Parkinson's relies on a steady, predictable supply of dopamine replacement therapy (most commonly carbidopa-levodopa). Disruptions to this schedule can provoke dramatic shifts:
Missed or Delayed Doses: A delay of even one to two hours can precipitate an abrupt "off" period, where mobility freezes and severe stiffness returns.
Generic Substitutions: Switching between brand-name medications and different generic formulations, or between various generic manufacturers, can sometimes lead to discrepancies in bioavailability and absorption rates, destabilizing control.
Drug Interactions: The introduction of new medications, such as certain anti-nausea drugs, typical antipsychotics, or specific blood pressure medications, can directly antagonize dopamine receptors, causing acute parkinsonism.
3. Metabolic and environmental stressors
Dehydration and Electrolyte Imbalances: Inadequate fluid intake impairs cellular function and can quickly worsen orthostatic hypotension (sudden drops in blood pressure upon standing), dizziness, and cognitive fog.
Sleep Deprivation: Severe lack of sleep exacerbates both motor symptoms (like tremors and dyskinesia) and non-motor symptoms (such as anxiety, hallucinations, and executive dysfunction).
Major Psychological Stress: Acute emotional trauma, grief, or severe anxiety triggers a surge of stress hormones like cortisol, which can significantly worsen tremors and overall motor control.
Red flags: Recognizing medical emergencies
While many acute fluctuations can be managed by adjusting schedules or treating underlying infections, certain sudden changes signal serious medical emergencies requiring immediate intervention.
| Emergency Sign | Potential Underlying Cause | Immediate Action Required |
|---|---|---|
| Sudden, severe rigidity with high fever and altered mental status | Neuroleptic Malignant Syndrome (NMS) or severe dopamine withdrawal | Emergency medical evaluation (ED) |
| Acute onset of weakness on one side of the body, slurred speech, or facial drooping | Cerebrovascular Accident (Stroke) or Transient Ischemic Attack (TIA) | Call emergency services immediately (911 / local equivalent) |
| Abrupt, severe confusion, hallucinations, or paranoid delusions accompanied by physical distress | Severe delirium secondary to infection, hypoxia, or toxic metabolic encephalopathy | Urgent medical assessment by a physician or emergency room |
| Sudden inability to swallow accompanied by aspiration risk or severe respiratory distress | Acute respiratory infection, aspiration pneumonia, or severe bulbar failure | Immediate emergency medical care |
Diagnostic approach: Clinical evaluation of Acute Changes
When an individual presents with a sudden worsening of Parkinson's symptoms, neurologists and primary care providers follow a structured diagnostic pathway to isolate the root cause:
Comprehensive Medication Review: The physician evaluates the exact timing, dosage, and formulation of all current medications, checking for recent changes, missed doses, or the introduction of interacting drugs.
Infection Screening: Standard protocols include urinalysis and urine culture to rule out asymptomatic or symptomatic UTIs, chest X-rays for pulmonary infections, and blood panels to check white blood cell counts and inflammatory markers.
Metabolic and Toxicological Panels: Blood tests assess kidney function, liver enzymes, glucose levels, and electrolyte balances, as well as screen for hypoxia or medication toxicity.
Neurological and Functional Assessment: The clinician compares current motor scores against baseline baselines using standardized scales (such as the MDS-UPDRS) to determine whether the deterioration is primarily motor, cognitive, or psychiatric in nature.
Management and reversal strategies
Addressing sudden symptom worsening focuses on swift identification and targeted treatment of the underlying trigger rather than permanently increasing baseline dopaminergic medication dosages.
Treating Underlying Triggers: Prompt antibiotic therapy for UTIs or respiratory infections frequently restores the patient to their pre-episode baseline within days. Correcting dehydration and electrolyte imbalances yields similarly rapid improvements.
Optimizing Dopaminergic Therapy: If the deterioration stems from medication timing or absorption issues, neurologists may adjust dosing intervals, recommend formulations with more consistent absorption profiles, or address dietary factors (such as spacing protein intake away from levodopa doses).
Supportive Care and Monitoring: Maintaining adequate hydration, ensuring safe nutritional intake, and providing a calm, orienting environment help manage acute confusion and prevent secondary complications like falls or pressure injuries.
Long-Term perspective and proactive prevention
Distinguishing between natural disease progression and acute, reversible fluctuations empowers patients and caregivers to respond effectively without unnecessary alarm. While Parkinson's is a progressive condition, sudden crises are almost always secondary events superimposed upon the baseline disease.
To minimize the risk of acute episodes:
Maintain Strict Medication Schedules: Utilize pill organizers, smartphone reminders, and caregiver oversight to ensure medications are taken precisely on time.
Prioritize Hydration and Nutrition: Encourage consistent fluid intake throughout the day, especially during warm weather or minor illnesses.
Establish Rapid Communication Channels: Keep open lines of communication with a movement disorder specialist or primary care team so that minor changes can be evaluated before they escalate into medical emergencies.
By maintaining vigilance over these secondary triggers, individuals living with Parkinson's and their care partners can navigate unexpected clinical changes with confidence, ensuring optimal safety and stability over the long course of the condition.