Understanding Aneurysm Pain: Anatomy, manifestations, and regional localizations
One of the most complex and critical aspects of understanding aneurysms is recognizing how and where they manifest pain. By definition, a quiet, unruptured aneurysm often grows silently over years without causing any physical discomfort. Because blood vessels lack primary pain receptors inside their walls, the mere presence of a small bulge rarely triggers symptoms on its own. Pain typically arises only when the expanding arterial wall begins to press aggressively against surrounding nerve pathways, compresses adjacent organs and structures, or, most dangerously, when the vessel wall tears or ruptures, causing internal bleeding.
Consequently, the physical location of aneurysm pain serves as a critical diagnostic roadmap for medical professionals, directly mirroring the anatomical site of the affected blood vessel. Whether the pain manifests as an excruciating, sudden headache, a deep, tearing sensation in the back or abdomen, or a sharp ache in the chest, understanding these pain topographies is vital for medical awareness.
Cerebral Aneurysms: Head, face, and eye Pain localizations
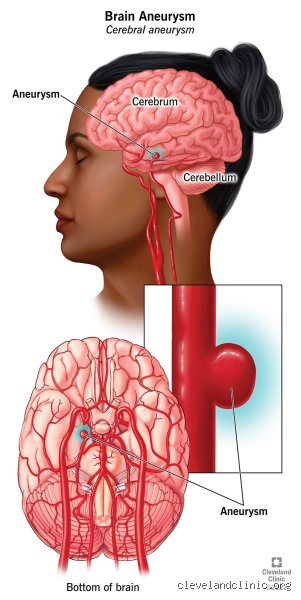
When an aneurysm develops within the intracranial blood vessels supplying the brain, most frequently forming along the complex branching network at the base of the brain known as the Circle of Willis, the pain characteristics depend entirely on whether the vessel remains intact or has suffered a compromise.
Unruptured cerebral Aneurysms
An unruptured brain aneurysm can remain entirely asymptomatic for a person's entire life. However, if the saccular (berry) or fusiform bulge expands significantly, it begins to exert localized mass effect on surrounding cranial nerves and brain tissue. This manifests as distinct, localized warning signs:
Retro-Orbital Pain: A persistent, piercing, or dull ache located directly behind or above one eye. This occurs because the expanding sac often compresses the third cranial nerve (oculomotor nerve) or branches of the trigeminal nerve.
Focal Cranial Neuropathy: Accompanying the localized eye or temple pain, individuals may notice structural nerve compression signs, such as a dilated pupil on the affected side, a drooping eyelid (ptosis), or sudden double vision (diplopia).
Facial Numbness: Pressure on sensory branches supplying the face can cause localized numbness or a tingling sensation restricted to one side of the face.
Ruptured cerebral Aneurysms (subarachnoid hemorrhage)
When a cerebral aneurysm tears or bursts, blood spills rapidly into the subarachnoid space surrounding the brain, sharply elevating intracranial pressure. This triggers one of the most distinct medical emergencies known to medicine:
The "Thunderclap" Headache: Patients universally describe this as the most severe, excruciating headache of their lives. Unlike tension headaches or standard migraines that build gradually over hours, an aneurysm rupture headache hits maximum peak intensity almost instantaneously, within seconds, feeling like an abrupt physical blow to the head.
Meningeal Irritation Pain: As extravasated blood irritates the delicate meningeal linings of the brain and spinal cord, pain radiates downward, resulting in severe neck stiffness and rigidity, often accompanied by photophobia (extreme sensitivity to light), projectile nausea, and vomiting.
Thoracic aortic Aneurysms: Chest, Back, and Throat Pain localizations
The aorta is the body’s principal systemic artery, extending upward from the left ventricle of the heart, arching through the chest cavity (thoracic aorta), and descending down through the diaphragm into the abdomen (abdominal aorta).
When a weakness forms in the section of the aorta passing through the chest, it is classified as a thoracic aortic aneurysm (TAA). Because the thoracic cavity houses rigid skeletal structures (the sternum, ribs, and thoracic spine) and vital cardiopulmonary organs, pain from a TAA typically presents in specific regions depending on which direction the vessel expands:
Substernal and Anterior Chest Pain: A deep, aching, or heavy discomfort located directly behind the breastbone. Because this pain can mimic cardiac conditions like angina or a myocardial infarction (heart attack), differentiating it requires advanced clinical imaging.
Interscapular and Upper Back Pain: As the descending thoracic aorta enlarges, it can press backward against the spinal column, ribs, and intercostal nerve roots. This generates a deep, gnawing, or tearing pain felt squarely between the shoulder blades or in the upper back.
Neck, Jaw, and Hoarse Throat Pain: If the aneurysm balloons outward along the aortic arch, it can irritate adjacent structures such as the recurrent laryngeal nerve or the trachea. This irritation can manifest as referred pain radiating upward into the jaw, neck, or left shoulder, frequently accompanied by an unexplained raspy voice or persistent coughing due to nerve compression.
Unruptured versus ruptured presentations: Decoding the discrepancies in Pain Localization
When clinical investigations focus on the question of where aneurysm pain is located, medical professionals must immediately divide the diagnostic landscape into two distinct clinical categories: unruptured aneurysms and ruptured aneurysms. The physiological mechanisms causing pain in these two scenarios are entirely different, meaning the resulting geographic distribution and sensory quality of the discomfort vary wildly.
An unruptured aneurysm typically causes pain through a localized "mass effect". As the blood vessel wall weakens and balloons outward, the expanding sac begins to physically compress adjacent anatomical structures. Depending on the vessel involved, this compression targets sensitive cranial nerves, dural linings, or surrounding soft tissues. Consequently, the pain of an unruptured aneurysm is usually focal, steady, and persistently localized to the specific region experiencing mechanical pressure.
Conversely, a ruptured aneurysm unleashes a sudden, catastrophic chemical and mechanical insult. When blood breaches the vessel wall and floods the subarachnoid space or surrounding cavities, it triggers an acute spike in intracranial or cavity pressure and severely irritates pain-sensitive membranes (such as the meninges in the central nervous system or the retroperitoneal lining in the abdomen). This type of pain does not stay neatly confined to a small, predictable spot; instead, it tends to present as a generalized, explosive shockwave of agony that radiates across entire regions of the body.
Cerebral Aneurysms: Pinpointing Cranial and Facial Discomfort
Intracranial or cerebral aneurysms, often referred to colloquially as brain aneurysms, frequently develop along the complex network of arteries residing at the base of the brain (the Circle of Willis). Because these vascular structures are densely intertwined with cranial nerves, the localized pain patterns of unruptured cerebral aneurysms serve as critical diagnostic roadmaps for neurologists and neurosurgeons.
1. Pain above and behind one eye
The single most common localized pain symptom of an unruptured brain aneurysm is a deep, steady, aching pain situated directly behind or precisely above one eye. This phenomenon occurs most frequently when an aneurysm forms on the internal carotid artery or the posterior communicating artery. As the sac expands, it exerts direct pressure on the third cranial nerve (the oculomotor nerve) and the ophthalmic branch of the trigeminal nerve. Patients frequently report that this retro-orbital ache feels distinct from a standard tension headache or migraine because of its unyielding focality and its association with ipsilateral (same-side) warning signs, such as a dilated pupil or a drooping eyelid (ptosis).
2. Temporal and Facial Numbness
When aneurysms affect branches extending toward the lateral aspects of the brain or near the skull base, the resulting pressure can impact the broader sensory fibers of the trigeminal nerve. This manifests as localized aching, tenderness, or intermittent numbness distributed across one side of the face, the jawline, or the temple region. Clinicians treat any newly developed, persistent facial asymmetry or localized cranial ache with high suspicion, utilizing magnetic resonance angiography (MRA) or computed tomography angiography (CTA) to rule out vascular pathology.
3. The "Thunderclap" explosion: Ruptured cerebral Pain
When a cerebral aneurysm ruptures, the localization paradigm shifts entirely. Patients do not report a localized, manageable spot of discomfort; rather, they experience what is universally documented as a "thunderclap headache". This is a hyper-acute, blindingly intense pain that reaches peak intensity within seconds to a single minute. While victims often clutch their heads or describe it as "the worst headache of my life", the pain rapidly diffuses across the entire cranium due to the instantaneous spread of blood across the subarachnoid space. This generalized head pain is almost universally accompanied by secondary somatic distress signals, including acute neck stiffness (meningismus) caused by blood irritation of the meninges, projectile vomiting, photophobia (extreme sensitivity to light), and sudden alterations in consciousness.
Aortic Aneurysms: Tracing Discomfort through the Chest, abdomen, and Back
Moving away from the central nervous system, aneurysms affecting the body's primary arterial trunk, the aorta, generate pain locations dictated by whether the pathology resides in the chest cavity (thoracic aortic aneurysm) or the lower torso (abdominal aortic aneurysm).
+------------------------------------+---------------------------------------------------+
| Aneurysm Location | Primary Pain Localization Zone |
+------------------------------------+---------------------------------------------------+
| Thoracic Aorta (Ascending/Arch) | Center of chest, radiating to jaw, neck, or throat|
+------------------------------------+---------------------------------------------------+
| Thoracic Aorta (Descending) | Deep between the shoulder blades (upper back) |
+------------------------------------+---------------------------------------------------+
| Abdominal Aorta (AAA) | Deep, dull ache in the mid-to-lower back or flank |
+------------------------------------+---------------------------------------------------+
Thoracic aortic Pain
The thoracic aorta courses upward from the heart, loops through the aortic arch, and descends through the chest. Because the thoracic cavity shares neural pathways with surrounding visceral structures, the pain location of a thoracic aneurysm can easily mimic other critical conditions, such as myocardial infarctions (heart attacks) or musculoskeletal strains:
Ascending Aorta and Arch Aneurysms: Pain is typically localized deeply behind the sternum (breastbone) in the central chest, frequently radiating upward into the neck, throat, jaw, or down the left arm.
Descending Thoracic Aneurysms: As the vessel moves downward, expansion or minor tearing presses against the posterior chest wall and spinal nerves, causing pain that patients precisely localize deep between their shoulder blades in the upper back.
Abdominal aortic Aneurysms (AAAs)
Abdominal aortic aneurysms represent one of the most common systemic vascular dilations, typically occurring below the renal arteries. Unruptured AAAs are frequently asymptomatic ("silent killers"), discovered incidentally during routine imaging. However, when an abdominal aneurysm expands rapidly or begins to leak, it signals an immediate medical emergency.
The pain location for an abdominal aortic aneurysm is remarkably specific:
The Mid-to-Lower Back and Flanks: Patients describe a constant, gnawing, deep-seated ache in the lumbar region or flanks. This occurs because the expanding aorta presses directly forward against the lumbar vertebrae and surrounding retroperitoneal nerve plexuses.
Periumbilical and Deep Abdominal Discomfort: A throbbing, pulsating sensation or deep, heavy ache may be felt directly in the abdomen, sometimes accompanied by a noticeable, palpable pulsating mass just beneath the navel.
Radiation to the Groin and Thighs: As blood tracks along retroperitoneal tissue planes during a symptomatic leak or impending rupture, pain can sharply radiate downward into the groin, pelvis, or upper thighs, frequently tricking patients into believing they are suffering from severe musculoskeletal injury or renal colic (kidney stones).
Peripheral and Visceral Aneurysms: Localized extremity Pain
While cerebral and aortic variants command significant medical attention due to their immediate lethality, aneurysms can also form in peripheral arteries outside the primary core, such as the popliteal artery behind the knee, the femoral artery in the groin, or visceral arteries supplying abdominal organs (like the splenic or renal arteries).
Popliteal and Femoral Aneurysms: Pain in these peripheral vessels is rarely isolated to a simple dull ache. Because these aneurysms frequently cause downstream micro-embolization (where small blood clots break off and travel down the limb) or acute vessel occlusion, the pain location corresponds to the deprived tissue. Patients experience cramping, ischemic pain, coolness, and numbness in the lower calf, foot, or toes, accompanied locally by a prominent, pulsing mass directly behind the knee joint or within the inguinal crease of the groin.
Visceral Aneurysms: Splenic or renal artery aneurysms typically remain completely silent until they expand or rupture. When symptomatic, they project a sharp, localized pain into the upper left quadrant of the abdomen (for splenic variants) or the flanks and lower back (for renal variants), frequently mimicking acute pancreatitis or severe renal dysfunction.
Red flag symptoms: When localized Pain becomes a medical emergency
Understanding where aneurysm pain is located is a crucial first step toward risk awareness, but recognizing the temporal evolution of that pain is what saves lives. Any chronic, stable, or mild localized pain, whether behind the eye, in the lower back, or across the chest, warrants systematic medical evaluation through diagnostic imaging such as ultrasound, CT scans, or MRIs.
However, certain clinical features transform localized pain into a Tier-1 medical emergency requiring immediate activation of emergency services (such as dialing 911):
The Onset Velocity: Pain that transitions from nonexistent to maximum agony within seconds (the classic thunderclap headache or a sudden tearing back/chest pain).
Hemodynamic Instability: Discomfort coupled with sudden dizziness, lightheadedness, cold sweats, rapid drop in blood pressure, or fainting (syncope).
Focal Neurological Deficits: Pain accompanied by sudden slurred speech, facial drooping, unilateral numbness, acute vision loss, or confusion.
While## The Critical Distinction: Burst vs. Unruptured Aneurysm Pain
Recognizing the "Thunderclap" of a ruptured Aneurysm
When an aneurysm ruptures, the landscape of pain changes dramatically and instantaneously. This medical emergency, most commonly a subarachnoid hemorrhage, presents with what neurologists and emergency physicians universally refer to as a "thunderclap headache."
Unlike the dull, persistent ache of an unruptured or expanding vessel, a rupture feels like a sudden, blinding strike to the head, frequently described by survivors as "the worst headache of my life."
The location of this pain often correlates with the exact site of the vascular rupture, though the rapid filling of the subarachnoid space with blood quickly irritates the meninges (the protective membranes surrounding the brain and spinal cord), causing the pain to rapidly diffuse across the entire cranium and radiate down the neck.
If the aneurysm is located in the anterior circulation (such as the anterior communicating artery), the severe pain is often concentrated squarely behind the eyes or across the forehead. Conversely, ruptures within the posterior circulation or the vertebrobasilar system may manifest with acute, violent pain radiating sharply into the base of the skull, the suboccipital region, and down the upper cervical spine.
Accompanying this catastrophic pain are critical neurological red flags that mandate immediate emergency intervention. These include:
Sudden, profound nausea and projectile vomiting
A stiff neck (nuchal rigidity) due to meningeal irritation
Acute photophobia (extreme sensitivity to light)
Brief or prolonged loss of consciousness
Focal neurological deficits, such as sudden weakness on one side of the body, slurred speech, or acute double vision
Recognizing these signs instantly can mean the difference between full recovery and permanent neurological disability or mortality.
Understanding sentinel headaches (warning leaks)
A vital concept in vascular neurology is the "sentinel headache" or warning leak. In a significant percentage of patients who experience a major aneurysmal rupture, there is a history of a sudden, unusual headache occurring days to weeks prior to the major event.
This minor sentinel bleed occurs when the aneurysm wall develops a small micro-tear or minor leakage before failing catastrophically. The pain is typically localized to the region overlying the affected vessel, mimicking a severe migraine or tension headache but distinguished by its abrupt onset ("out of nowhere") and unusual severity.
Clinicians emphasize that any acute, severe headache that breaks a patient's normal headache pattern warrants urgent neuroimaging, as identifying an unruptured or leaking aneurysm at this stage allows for elective endovascular or surgical treatment before a devastating subarachnoid hemorrhage occurs.
Peripheral Aneurysms: Abdominal and Thoracic Pain patterns
While intracranial aneurysms command significant attention due to their neurological implications, aneurysms can also develop along the body’s largest artery, the aorta, as it courses through the chest (thoracic aortic aneurysm) and the abdomen (abdominal aortic aneurysm, or AAA). The pain associated with these vascular dilations reflects their anatomical location and the structures they impinge upon as they expand.
Abdominal aortic Aneurysms (AAAs)
Most abdominal aortic aneurysms develop silently and are discovered incidentally during imaging for unrelated conditions. However, as an AAA enlarges, it exerts pressure on the retroperitoneal space, the spine, and adjacent nerve roots.
When pain does manifest, it is typically characterized as:
Deep, boring abdominal discomfort: Patients often describe a constant, gnawing sensation deep within the abdomen, occasionally accompanied by a palpable, pulsatile mass just beneath the navel.
Back and flank radiation: Because the abdominal aorta lies directly anterior to the lumbar spine, expansion or localized inflammation frequently causes deep, dull pain in the lower back or flanks. This back pain is unique because it is typically non-mechanical, meaning it does not change with twisting, bending, or physical positioning.
The threat of rupture: When an abdominal aneurysm begins to leak or rupture, the pain escalates rapidly into severe, excruciating tearing or ripping sensations radiating from the abdomen straight through to the back or lower pelvis. This is accompanied by profound hemodynamic instability, lightheadedness, and syncope, representing a surgical emergency with a high mortality rate if not treated immediately.
Thoracic aortic Aneurysms (TAAs)
Aneurysms occurring in the chest, either in the ascending aorta, the aortic arch, or the descending thoracic aorta, produce pain patterns dictated by the rigid boundaries of the thoracic cavity and the vital structures housed within it.
Chest and substernal pain: Patients may experience a persistent, heavy ache behind the sternum, often misdiagnosed initially as cardiac ischemia (angina) or musculoskeletal chest wall pain.
Referred pain to the jaw, neck, and shoulders: Due to shared autonomic innervation pathways, pain from a thoracic aneurysm can radiate upward into the neck, jaw, left shoulder, or between the scapulae.
Compression symptoms: As a TAA expands, it can compress surrounding structures, leading to secondary pain or functional changes:
Compression of the recurrent laryngeal nerve can cause hoarseness of the voice.
Compression of the trachea or bronchi can result in a chronic, dry cough, wheezing, or difficulty breathing.
Compression of the esophagus can cause dysphagia (difficulty swallowing).
Diagnostic evaluation and the role of neuroimaging
Given the overlap between aneurysm pain and more common, benign conditions such as tension headaches, migraines, or musculoskeletal back strain, accurate diagnosis relies heavily on advanced imaging modalities.
When a patient presents with "red flag" pain characteristics, such as a thunderclap onset, a sentinel headache, or unexplained, non-mechanical back and abdominal pain, clinicians utilize specific diagnostic tools to visualize the vascular tree:
Computed Tomography (CT) and CT Angiography (CTA): Non-contrast head CT is the gold standard for rapidly detecting acute blood in the subarachnoid space following a rupture. CTA utilizes intravenous contrast material to create detailed, three-dimensional images of the cerebral or systemic arteries, allowing physicians to pinpoint the exact location, size, and morphology of an unruptured or ruptured aneurysm.
Magnetic Resonance Imaging (MRI) and MR Angiography (MRA): MRA provides high-resolution images of blood vessels without the use of ionizing radiation. It is particularly valuable for screening individuals with a strong family history of aneurysms or specific genetic connective tissue disorders (such as Marfan syndrome or Ehlers-Danlos syndrome).
Digital Subtraction Angiography (DSA): Considered the definitive diagnostic standard, DSA involves the catheterization of femoral or radial arteries to inject contrast directly into the arterial supply of the brain or body. This invasive procedure provides real-time, high-definition visualization of vascular anatomy and is frequently performed concurrently with endovascular treatment planning.
Summary and clinical takeaways
Understanding where aneurysm pain is located requires looking past simple generalizations and examining the specific vascular bed involved.
Intracranial aneurysms generate pain localized to specific cranial nerve pathways or manifest as the sudden, global "thunderclap" headache of a rupture.
Abdominal aortic aneurysms signal their presence through deep, constant abdominal and non-mechanical lower back pain.
Thoracic aortic aneurysms present with substernal discomfort and symptoms related to the compression of neighboring thoracic structures.
Because the pain profiles of aneurysms can mimic everyday ailments, public awareness and low thresholds for clinical investigation remain paramount. Any sudden, severe, or uncharacteristic pain, particularly when described as the "worst ever" or accompanied by neurological or hemodynamic warning signs, demands immediate medical evaluation and advanced vascular imaging. Early detection transforms a life-threatening emergency into a manageable condition, preserving neurological and cardiovascular health.