The navigation mechanism of monarch butterflies
Environmental triggers and overwintering survival
The onset of autumn initiates physiological changes driven by shifting daylight hours and declining ambient temperatures. Rather than maturing into reproductive adults, the final autumn generation enters a state of suspended reproductive development known as reproductive diapause. This specific metabolic shift dramatically increases longevity, enabling individual butterflies to survive up to eight months, a stark contrast to the standard two-to-six-week lifespan of summer generations. Upon reaching designated microclimates within high-altitude fir forests, millions cluster densely together on specific tree branches to conserve heat and moisture until warming spring conditions trigger the northward return journey.
Cognitive and emotional manifestations of Parkinson's disease
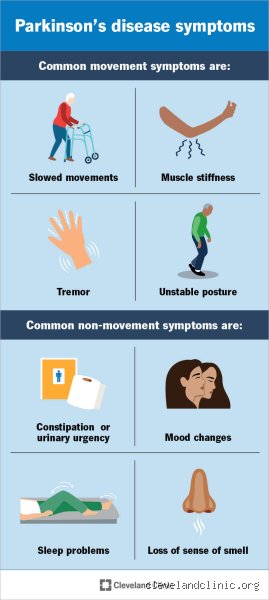
Beyond the visible physical alterations, Parkinson's disease profoundly impacts cognitive function and emotional regulation. These internal shifts frequently emerge gradually, intertwining with motor symptoms to shape daily interactions and individual behavior.
Executive function and processing speed
Changes in executive functioning represent a primary cognitive domain affected by the condition. Individuals often experience difficulties with planning, organizing, multitasking, and problem-solving. A person might find it increasingly challenging to manage household finances, follow complex multi-step cooking recipes, or transition smoothly from one task to another.
Processing speed also tends to slow down. Conversations requiring rapid banter or quick decision-making can become fatiguing. While core intelligence and long-term memory typically remain intact during the early and moderate stages, the operational speed of retrieving information and executing goal-directed tasks diminishes. This slowing is directly linked to the degeneration of dopamine pathways connecting subcortical structures to the frontal lobes, which govern cognitive control and mental agility.
Apathy and motivational shifts
Apathy is among the most prevalent yet frequently misunderstood behavioral changes in Parkinson's disease. Unlike clinical depression, which involves feelings of sadness or hopelessness, apathy is characterized by a profound reduction in goal-directed behavior and emotional initiative.
A person with high levels of apathy may sit for hours without engaging in hobbies, fail to initiate conversations, or display a lack of interest in social outings. Family members often misinterpret this as laziness or stubbornness. In reality, the brain's internal reward and motivation circuitry is disrupted, making the mental effort required to start an activity feel overwhelmingly burdensome, even if the person enjoys the activity once it begins.
Depression and anxiety profiles
Mood disturbances frequently accompany the neurodegenerative process. Clinical depression affects a significant percentage of diagnosed individuals, stemming both from the psychological adjustment to a chronic, progressive condition and from the direct biochemical changes within the brain. Serotonin and norepinephrine pathways are often altered alongside dopamine pathways, contributing directly to depressive symptoms.
Anxiety is equally common, manifesting as generalized worry, social apprehension, or specific phobias related to physical instability. Fear of falling in public spaces can lead to hypervigilance or avoidance behaviors, causing individuals to withdraw from social settings. This withdrawal is rarely a reflection of personal preference; rather, it serves as a coping mechanism for managing unpredictable physical symptoms in uncontrolled environments.
Social dynamics and interpersonal communication
The behavioral profile of Parkinson's disease inevitably influences relationships and social engagement. Communication involves much more than spoken words; it relies heavily on facial expressions, vocal inflection, and body language—all of which are targeted by the condition.
Hypophonia and prosody alterations
Speech and voice production undergo distinct shifts. Hypophonia, or a reduction in speech volume, is extremely common. Individuals may perceive their voice as normal while sounding subdued or whispering to listeners.
Prosody—the rhythmic and intonational contour of speech, is often flattened, resulting in a monotone delivery. Because emotional tone is conveyed largely through vocal inflection, a flat voice can make a person sound indifferent, bored, or detached, regardless of their actual feelings. Listeners must learn to look past these acoustic alterations and rely on explicit verbal statements rather than vocal cues to gauge emotional states.
Masked facies and social misunderstandings
The muscles responsible for facial expression are controlled by cranial nerves and subcortical structures affected by dopamine depletion. This leads to hypomimia, commonly referred to as masked facies. The face may exhibit reduced spontaneous movement, maintaining a fixed or neutral expression even during moments of amusement, surprise, or distress.
This physical manifestation creates a significant barrier in social communication. Friends, colleagues, and strangers may misinterpret the lack of facial feedback as unfriendliness, disinterest, or cognitive decline. Navigating social environments requires deliberate effort from both the individual and their communication partners to bridge this gap, ensuring that internal emotional richness is not obscured by physical immobility.
Behavioral adaptations and coping mechanisms
As physical and cognitive changes accumulate, individuals develop various strategies to maintain independence and social connection. Some rely heavily on structured daily routines to compensate for executive dysfunction, using calendars, alarms, and visual cues to manage medication schedules and daily activities.
Others adopt pacing strategies, intentionally breaking complex tasks into smaller segments to conserve energy and manage fatigue. Socially, some individuals become more selective about their engagements, prioritizing meaningful one-on-one interactions over large, overwhelming gatherings where background noise and rapid movement complicate communication and physical stability.
Behavioral fluctuations and medication effects
A defining characteristic of Parkinson's behavior is its variability over time. Symptoms are rarely static throughout the day; instead, they fluctuate in response to medication cycles, physical exertion, stress, and fatigue.
The On-Off Phenomenon
As the disease progresses and medical management evolves, many individuals experience motor and non-motor fluctuations. The term "on" period describes times when medication is effectively controlling symptoms, allowing for relatively smooth movement, clear speech, and stable mood.
Conversely, an "off" period occurs when medication efficacy wanes before the next scheduled dose. During an "off" state, not only do motor symptoms like tremors and rigidity worsen, but non-motor symptoms also intensify. A person may experience a sudden surge of severe anxiety, cognitive slowing, profound fatigue, or depressive thoughts. These rapid shifts require immense psychological resilience, as the individual's behavioral and emotional state can change drastically within the span of an hour.
Impulse control disorders
Paradoxically, certain behavioral changes are driven not by the disease itself, but by dopaminergic medications used for treatment. Dopamine agonist medications can alter reward pathways in susceptible individuals, leading to impulse control disorders.
Manifestations include compulsive behaviors such as pathological gambling, compulsive shopping, binge eating, or hypersexuality. Some individuals develop intense, repetitive hobbies pursued to the exclusion of all other responsibilities, or a compulsive interest in creative or mechanical projects. Recognizing these behaviors requires close collaboration between neurologists, patients, and caregivers, as adjusting medication dosages can often resolve these challenging psychological side effects while maintaining motor function.
Caregiver dynamics and behavioral support
The behavioral landscape of Parkinson's disease places unique demands on care partners and family members. Managing unpredictable fluctuations, interpreting flat vocal tones, and navigating cognitive shifts require education, patience, and emotional endurance.
Support strategies often focus on establishing predictable environments, practicing clear and direct communication, and encouraging safe autonomy. Professional counseling, support groups, and respite care play vital roles in sustaining the well-being of both the individual with Parkinson's and their caregivers, ensuring that the behavioral complexities of the condition are managed with empathy and practical insight.