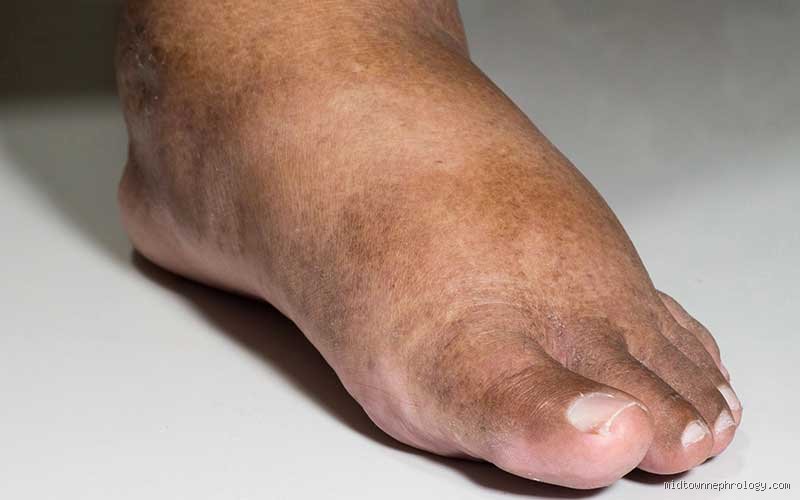
While medical diagnostics traditionally rely on blood panels—such as measuring serum creatinine and estimated glomerular filtration rate (eGFR), and urinalysis, the human exterior often serves as an immediate, visible map of internal distress. Surprisingly, the lower extremities, particularly the feet and ankles, frequently become a primary canvas for the systemic disruptions caused by renal failure. Examining what the feet look like under these conditions reveals a striking combination of fluid dynamics anomalies, dermatological transformations, vascular shifts, and neurological indicators.
This comprehensive expert analysis digs into the intricate physical transformations that affect the feet when the kidneys fail, breaking down the physiological mechanisms that turn subtle internal changes into overt, observable symptoms.
1. Fluid overload and peripheral edema: The Visual signature of renal decline
The most prominent and immediately recognizable physical alteration in the feet of an individual experiencing kidney failure stems from a disruption in fluid and sodium homeostasis. Healthy kidneys function as precise biological filters, sorting through approximately 150 quarts of blood daily to selectively reabsorb essential elements while excreting excess water and metabolic waste products like urea and creatinine into the urine.
When the kidneys fail, this filtration capacity plummets. Consequently, sodium and water are retained within the vascular system and subsequently leak into the interstitial spaces, the microscopic compartments surrounding tissue cells. Because of gravity, this excess fluid naturally migrates downward, accumulating in the lowest points of the body. This phenomenon is clinically designated as peripheral edema.
The Visual presentation of Pitting edema
When observing a foot affected by advanced renal-induced edema, several distinct physical characteristics become apparent:
Loss of Anatomical Contour: The normal bony landmarks of the foot, such as the malleoli (ankle bones), the tendons traversing the dorsum (top) of the foot, and the individual contours of the metatarsals, begin to blur and flatten. The foot may take on a smooth, rounded, or "sausage-like" appearance as subcutaneous fluid fills the spaces.
The Pitting Phenomenon: A hallmark clinical sign of systemic fluid retention is known as "pitting edema". When an examiner or the individual presses a finger firmly against the dorsal skin of the foot or over the bony prominence of the ankle for several seconds, the pressure displaces the interstitial fluid. Upon releasing the pressure, an indentation or "pit" remains visible and slow to rebound. The depth and duration of this depression often correlate directly with the severity of the fluid overload.
Skin Tightness and a Shiny Texture: As fluid continues to pack the interstitial tissues, the skin on the feet and lower legs stretches tightly over the underlying volume. This over-stretching causes the epidermis to appear glossy, taut, and remarkably shiny, losing its normal skin markings and pliability.
Footwear Discrepancies and Sock Indentations: Individuals often first notice this presentation practically rather than visually. Shoes that previously fit comfortably suddenly feel tight, restrictive, or entirely impossible to lace up. The elastic bands of socks leave deep, angry red grooves or rings etched sharply into the skin around the ankles long after the socks have been removed.
2. Dermatological Manifestations: Uremic Changes and extreme Skin pathology
Beyond the hydrodynamic swelling caused by fluid retention, the skin of the feet undergoes striking biochemical changes during kidney failure. The accumulation of uremic toxins, substances that healthy kidneys normally filter out, circulates globally through the bloodstream, profoundly altering the physiology of the integumentary system, particularly in the lower extremities where circulation is already subject to gravitational resistance.
Extreme Xerosis (severe dryness)
The skin on the feet of a patient with kidney failure frequently exhibits severe, pathological dryness, clinically termed uremic xerosis.
Texture and Scaling: The skin loses its natural moisture-retaining capabilities and natural lipid production. On the feet, an area already prone to thick stratum corneum layers, this dryness manifests as rough, flaky, and scaly surfaces. In advanced stages, the skin can resemble fish-like scales or crack painfully, particularly around the heels and the soles where pressure is highest.
The Itch-Scratch Cycle (Uremic Pruritus): Associated with this severe dryness and underlying mineral imbalances (such as elevated serum phosphorus and calcium-phosphate product accumulation), patients frequently experience deep, relentless itching known as uremic pruritus. While this can affect the entire body, the feet and lower legs are common sites. The physical appearance of the feet is often altered secondary to this chronic scratching: dermatologists frequently observe excoriations, scratch marks, areas of localized bleeding, crusting, and in chronic cases, lichenification (thickened, leathery skin resulting from repetitive trauma).
Coloration and pigmentary shifts
Uremic toxins and secondary systemic alterations can also shift the color profile of the skin and nails on the feet:
Pallor and Sallow Hues: Patients with advanced kidney disease frequently develop severe anemia due to a deficiency in erythropoietin, a hormone normally produced by healthy kidneys to stimulate red blood cell production. This anemic state imparts an unhealthy, pale, or yellowish-gray hue to the skin of the extremities.
Hyperpigmentation: Conversely, some individuals experience patchy or diffuse darkening of the skin due to the deposition of retained pigments and chronic irritation from scratching.
The progression of lower extremity Manifestations in Advanced renal decline
As chronic kidney disease (CKD) advances toward end-stage renal failure, the physiological disturbances within the body begin to manifest physically in the lower extremities. The kidneys' primary roles, filtering waste products, maintaining electrolyte equilibrium, and regulating fluid balance, begin to fail catastrophically. Consequently, the visual and structural appearance of the feet and ankles transforms, serving as an external indicator of internal systemic distress.
Severe edema and Pitting characteristics
The most prominent physical alteration in the feet during kidney failure is systemic fluid retention, clinically known as edema. When renal filtration drops, excess sodium and water accumulate extracellularly. Because of gravity, this excess fluid pools in the lowest parts of the body, heavily impacting the feet, ankles, and lower legs.
Visual Changes: The feet may appear noticeably enlarged, shiny, and tightly stretched. Skin contours, such as the normal bony prominences around the ankle bones and tendons on the top of the foot, can become entirely obscured by smooth, taut tissue.
The Pitting Test: A hallmark characteristic of renal-induced edema is "pitting." When firm pressure is applied with a finger to the swollen dorsal surface of the foot for a few seconds, an indentation remains after the finger is lifted. This depression occurs because the fluid is displaced from the interstitial spaces beneath the pressure point and takes time to flow back.
Dermatological Alterations and chronic dryness
Beyond fluid overload, the accumulation of uremic toxins and profound mineral imbalances (such as calcium and phosphorus dysregulation) severely affect the skin integrity of the lower limbs.
Uremic Xerosis: Patients frequently develop extreme, generalized skin dryness known as xerosis. On the feet, this often presents as thick, scaly, and flaking skin, particularly across the heels and soles. The natural moisture and sweat glands fail to function properly due to systemic toxicity and nerve changes.
Uremic Pruritus and Scratch Marks: Intense, deep-seated itching is a common complication. Consequently, the skin on the feet and lower legs often displays secondary trauma marks, including excoriations, redness, and localized thickening (lichenification) from chronic scratching.
Rare Manifestations (Uremic Frost): In profound, untreated end-stage renal failure where blood urea nitrogen (BUN) levels are exceptionally high, sweat can excrete high concentrations of urea. As the perspiration evaporates on the skin surface, it leaves behind a fine, white, powdery crystalline deposit known as "uremic frost". While rare in modern healthcare settings with access to dialysis, it historically appeared as a frosted, salt-like dusting on the extremities.
Vascular, perfusion, and Nail Changes
Kidney failure rarely occurs in isolation; it frequently coexists with systemic vascular disease, diabetes, and hypertension, all of which alter the appearance of the feet at a microvascular level.
| Feature | Appearance in Advanced Kidney Failure | Underlying Physiological Cause |
|---|---|---|
| Skin Tone & Temperature | Pale, cool to the touch, or mildly cyanotic in advanced peripheral vascular disease. | Compromised microcirculation and frequent concurrent atherosclerosis. |
| Nail Bed Alterations | Half-and-half nails (Lindsay’s nails), where the proximal portion is white and the distal portion is reddish-brown. | Chronic azotemia and altered protein synthesis affecting nail matrix blood vessels. |
| Vulnerability to Ulceration | Slow-healing fissures, particularly around dry heels, carrying a high risk of secondary infection. | Reduced tissue perfusion, compromised skin barrier under edema pressure, and altered immune response. |
Clinical significance and monitoring
Recognizing these foot and ankle manifestations is vital for timely medical intervention. Clinical management typically involves a combination of nephrology care, strict dietary sodium and fluid restrictions, diuretic therapy, and regular monitoring of renal replacement therapies such as dialysis. For individuals experiencing unexplained or persistent lower extremity swelling alongside systemic symptoms like fatigue or changes in urination patterns, prompt laboratory evaluation of kidney function remains essential.