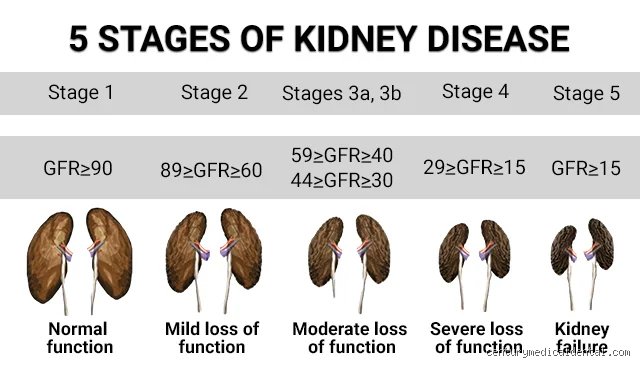
The human kidney is an exceptionally complex and resilient organ, yet its healing timeline is not governed by a single universal clock. Instead, recovery varies dramatically depending on the root cause of the injury, the extent of structural damage, the timeliness of medical intervention, and whether the condition is classified as an acute insult or a chronic, long-term degradation.
To understand how long kidney improvement takes, one must first deconstruct the fundamental biological nature of renal injury. The kidneys are microscopic filtration powerhouses, housing roughly one million functional units called nephrons. Each nephron contains a specialized cluster of blood vessels known as the glomerulus, paired with a delicate tubular system responsible for filtering waste, balancing electrolytes, regulating blood pressure, and maintaining fluid homeostasis. When disease, toxicity, trauma, or systemic shock strikes, these structures experience varying degrees of stress, ischemia, or cellular death.
Acute Kidney Injury (AKI): The 90-Day clinical framework
The fastest and most dramatic recoveries occur in cases of Acute Kidney Injury (AKI)—a sudden and rapid decline in kidney filtration capacity that typically unfolds over hours to days. AKI is frequently triggered by events such as severe dehydration, major surgery, sepsis, heavy blood loss, urinary tract obstructions, or exposure to nephrotoxic medications and contrast dyes.
Medical literature and nephrology guidelines classify the evolution of an acute renal event into distinct chronological phases. Understanding these milestones is vital because an elevated serum creatinine or a depressed estimated glomerular filtration rate (eGFR) immediately following an injury does not automatically denote permanent failure; rather, it often reflects an organ caught mid-recovery.
Phase 1: The initiation and maintenance phase (weeks 1 to 3)
During the initial days following an acute insult, kidney function plummets. In clinical settings, this is often marked by the maintenance or oliguric phase, where urine output drops significantly and waste products such as creatinine and blood urea nitrogen (BUN) peak. Cellular swelling, tubular cell death (acute tubular necrosis), and localized inflammation peak during this window.
For severe cases—particularly those requiring temporary renal replacement therapy or dialysis in an intensive care setting, the kidneys are resting while an artificial filter manages blood chemistry. Even in these severe scenarios, the kidneys frequently retain intrinsic regenerative capacity. This phase typically lasts anywhere from a few days to three weeks.
Phase 2: The diuretic phase (days 3 to weeks 2)
As the underlying trigger is resolved and tubular cells begin repairing themselves, patients often enter the diuretic phase. Urine output increases sharply, sometimes reaching several liters per day, as the healing kidneys flush out accumulated fluid and toxins. While alarming to families unfamiliar with the process, this high-output phase is a positive sign that tubular function is waking up, though it requires meticulous clinical monitoring to prevent electrolyte depletion (such as drops in potassium, sodium, and magnesium).
Phase 3: The recovery window (weeks to 12 months)
Following diuresis, serum creatinine begins a gradual descent toward baseline levels, and overall physical stamina slowly returns. Nephrologists track this trajectory across three critical temporal thresholds:
Days 1 to 7: The acute injury window where immediate stabilization occurs.
Day 7 to Day 90 (Acute Kidney Disease): If functional recovery extends beyond the first week, the condition is categorized as Acute Kidney Disease (AKD). During this window, cellular remodeling, basement membrane repair, and microvascular restoration take place over several weeks.
The 90-Day Checkpoint: Modern clinical guidelines treat the three-month mark as the definitive line of demarcation. If elevated creatinine or structural markers of damage persist past 90 days, the diagnosis transitions from acute injury to Chronic Kidney Disease (CKD).
Factors that accelerate or stalls Renal healing
Not all acute injuries resolve at the same pace. A mild prerenal AKI driven purely by acute volume depletion (such as severe dehydration or over-diuresis) can reverse completely within 2 to 7 days once fluids are restored. Conversely, profound Stage 3 AKI complicated by sepsis or prolonged ischemia may require 3 to 12 months for the nephrons to achieve maximum functional plateau.
Several key determinants dictate this timeline:
Baseline Renal Health: Individuals with pristine pre-injury kidney function possess greater physiological reserve, enabling faster and more complete cellular regeneration.
Speed of Intervention: Relieving an acute urinary obstruction or removing a nephrotoxic drug within the first 24 to 48 hours dramatically shortens the recovery timeline and minimizes permanent scarring (fibrosis).
Age and Comorbidities: Controlled blood pressure, stable glycemic indices in diabetes, and younger age favor robust tissue repair, whereas chronic vascular damage can sluggishly drag out the healing curve.
This concludes the first part of our exploration into renal recovery timelines. The subsequent section will examine chronic kidney disease progression, lifestyle and therapeutic interventions that support long-term stabilization, and what to expect during post-recovery monitoring.
Understanding the trajectory: From Acute recovery to Long-Term Renal resilience
While the initial weeks following a sudden drop in kidney function center around halting damage and clearing accumulated toxins, the broader arc of renal recovery extends far beyond the hospital discharge. When looking at how long it takes for kidneys to improve, nephrologists emphasize a crucial distinction: true biological repair unfolds across distinct metabolic checkpoints. For patients recovering from Acute Kidney Injury (AKI), the journey transitions from acute crisis management into a stabilization phase where cellular regeneration takes center stage.
The cellular mechanics of Renal regeneration
Unlike many other visceral organs that heal primarily through scar formation, the kidneys possess a remarkable, albeit delicate, capacity for intrinsic cellular repair. Following an ischemic or toxic insult, such as severe dehydration, sepsis, or exposure to nephrotoxic agents, the epithelial cells lining the renal tubules experience severe stress or apoptosis.
Dedifferentiation and Migration: Surviving tubular cells rapidly shed their specialized transport characteristics, dedifferentiating into highly motile cells that migrate to cover denuded basement membranes.
Proliferation: Driven by local growth factors (such as epidermal growth factor and hepatocyte growth factor), these cells undergo active mitosis to restore structural integrity.
Redifferentiation: Over subsequent weeks, the newly populated cells re-establish their complex polarity, brush borders, and ion transport channels, gradually restoring the kidney's sophisticated filtration and reabsorption mechanics.
This microscopic cellular ballet explains why laboratory markers like serum creatinine and estimated glomerular filtration rate (eGFR) often improve rapidly at first, yet continue a slow, asymptotic upward trend for many months.
Navigating the Multi-Month recovery Horizon
The timeline of recovery is heavily dictated by the initial severity of the insult and the promptness of medical intervention. While mild prerenal events often resolve within days, more complex clinical scenarios require a structured, long-term monitoring protocol:
The 30-Day Checkpoint: By the end of the first month, acute inflammation typically subsides. Blood pressure regulations stabilize, and systemic fluid overload resolves. Clinicians focus heavily on electrolyte balance and ensuring that blood pressure medications (such as ACE inhibitors or ARBs) can be safely reintroduced without provoking a secondary drop in filtration pressure.
The 90-Day Watershed (AKD vs. CKD): Nephrology guidelines designate the 90-day mark as the definitive boundary separating Acute Kidney Disease (AKD) from Chronic Kidney Disease (CKD). If functional deficits, persistent proteinuria, or elevated serum creatinine persist past three months, the condition is formally classified as chronic damage, requiring long-term nephroprotective strategies.
The One-Year Horizon: Even patients who achieve a seemingly complete normalization of baseline creatinine levels continue to experience subtle structural remodeling for up to 12 months. Clinical data demonstrates that full physical stamina, cardiovascular equilibrium, and metabolic stability after a severe Stage 3 AKI episode often take a full year to materialize.
Lifestyle optimization and nephroprotection during recovery
Supporting the kidneys during their prolonged recovery phase requires a deliberate shift toward physiological preservation. Because recovering nephrons operate with a reduced functional reserve, minimizing secondary renal stress is paramount:
Hydration Discipline: Maintaining adequate, steady fluid intake ensures optimal renal perfusion without imposing sudden volume overloads. Patients must avoid extreme dehydration, particularly during hot weather or physical exertion, as a second ischemic hit during the recovery window can cause disproportionate, lasting damage.
Strict Medication Stewardship: Avoiding nephrotoxic agents, particularly non-steroidal anti-inflammatory drugs (NSAIDs) like ibuprofen or naproxen, is essential. These compounds constrict the afferent arterioles of the glomeruli, directly undermining fragile recovery processes.
Dietary Adjustments: Partnering with a renal dietitian to manage sodium, phosphorus, and potassium intake helps reduce the hyperfiltration burden on surviving nephrons, stabilizing long-term functional decline.
Whether recovery spans a few weeks or stretches across a full year, consistent outpatient monitoring, rigorous blood pressure control, and disciplined lifestyle modifications remain the cornerstones of restoring and preserving long-term kidney health.