Understanding Osmotic diarrhea: Mechanisms and Clinical foundations
Defining Osmotic diarrhea and its pathophysiological basis
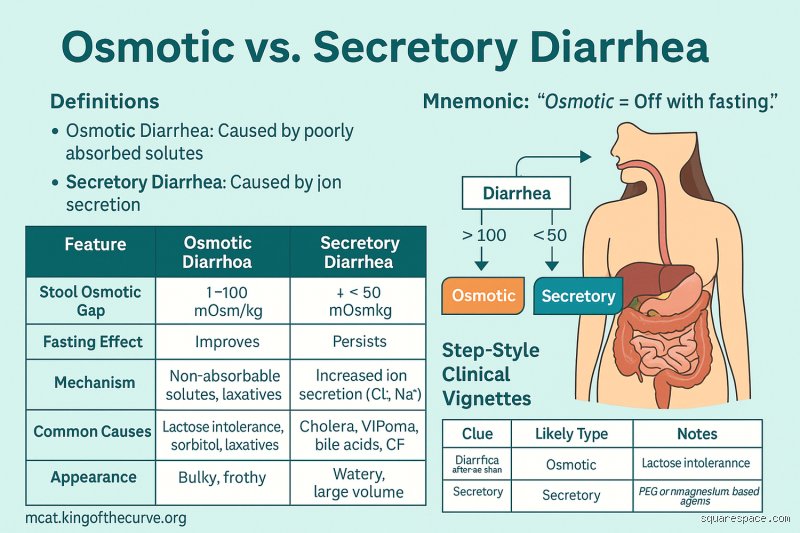
Key distinguishing features from secretory diarrhea
To fully grasp the nature of osmotic diarrhea, it is helpful to contrast it with its primary counterpart, secretory diarrhea. While both conditions result in watery stools, their underlying physiological triggers diverge sharply:
Fasting Response: Osmotic diarrhea typically resolves or significantly improves when the patient undergoes fasting or ceases ingestion of the offending substance. Secretory diarrhea, by contrast, continues even during prolonged periods of fasting because active electrolyte secretion by crypt cells persists.
Stool Osmotic Gap: In osmotic cases, calculating the stool osmotic gap reveals a high gap (typically greater than 100 mOsm/kg), as the unabsorbed solutes account for a substantial portion of stool osmolality. Secretory diarrhea generally presents a low stool osmotic gap, driven predominantly by active sodium and chloride secretion.
Electrolyte Composition: The stool electrolyte concentrations in osmotic diarrhea reflect the unabsorbed solute dilution, whereas secretory diarrhea is characterized by high active secretion of sodium and potassium regardless of dietary intake.
Recognizing these foundational mechanisms allows clinicians and researchers to pinpoint the precise etiologies behind various gastrointestinal presentations, paving the way for targeted diagnostic and dietary interventions.
Unraveling complex malabsorption syndromes
Beyond simple food intolerances and intentional laxative use, chronic osmotic diarrhea frequently serves as a red flag for complex, systemic malabsorption syndromes. When the structural integrity or biochemical machinery of the small intestine is compromised, multiple nutrients bypass absorption, creating a powerful osmotic gradient within the lumen.
Celiac disease and small intestinal damage
Celiac disease is an autoimmune enteropathy triggered by the ingestion of gluten. When individuals with this condition consume gluten, an immune-mediated response damages the microvilli of the small intestine—the tiny, finger-like projections responsible for maximizing nutrient absorption.
The Pathophysiology: As the brush border flattens (villous atrophy), the surface area available for absorbing carbohydrates, fats, and proteins plummets.
The Result: Unabsorbed complex breakdown products and secondary unabsorbed carbohydrates remain osmotically active, dragging water into the bowel and causing chronic, watery stools alongside nutritional deficiencies.
Pancreatic Insufficiency
The pancreas plays an indispensable role in digestion by secreting crucial enzymes—such as lipase, amylase, and proteases, into the duodenum. Conditions such as chronic pancreatitis, cystic fibrosis, or pancreatic duct obstruction severely diminish enzyme output.
The Pathophysiology: Without adequate enzymes, dietary macronutrients cannot be broken down into absorbable units (monosaccharides, free fatty acids, and amino acids).
The Result: Large, intact nutrient molecules travel down the gastrointestinal tract, retaining luminal water through high osmotic pressure and leading to bulky, greasy, and frequent stools (steatorrhea and osmotic diarrhea combined).
Diagnostic approach and Clinical management
Distinguishing osmotic diarrhea from other etiologies, such as secretory or inflammatory diarrhea, requires a systematic clinical approach. Because osmotic diarrhea is fundamentally driven by luminal contents that draw water, the cornerstone diagnostic feature is its resolution during fasting. When a patient stops oral intake, the influx of unabsorbed substrates halts, and the diarrhea rapidly improves, a pattern rarely observed in secretory conditions.
+-------------------------------------------------------------------+
| DIAGNOSTIC DIFFERENTIATION |
+-------------------------------------------------------------------+
| Fasting Test: Osmotic diarrhea stops or significantly improves. |
| Stool Osmotic Gap: High (> 50 mEq/L) in osmotic diarrhea. |
| Fecal Testing: Evaluates for hidden magnesium or laxatives. |
+-------------------------------------------------------------------+
Key diagnostic tools
Detailed Dietary and Medication History: Reviewing the patient's consumption of sugar-free products, dairy, fruit juices, and over-the-counter supplements often reveals the culprit instantly.
Stool Osmotic Gap Calculation: Analyzing stool electrolytes allows clinicians to calculate the osmotic gap. A gap greater than 50 mEq/L strongly points toward an osmotic mechanism driven by unabsorbed solutes.
Breath Testing and Serology: Hydrogen breath tests can confirm carbohydrate malabsorptions (such as lactose or fructose), while specific blood panels (like tissue transglutaminase antibodies) screen for celiac disease.
Therapeutic Strategies
Management focuses primarily on eliminating the offending agent or treating the underlying systemic disorder:
Dietary Elimination: Removing identified triggers, such as swapping regular dairy for lactose-free alternatives or cutting back on sorbitol-heavy sugar-free gums, resolves symptoms completely.
Enzyme Replacement Therapy: Patients with exocrine pancreatic insufficiency find relief through oral pancreatic enzyme replacement therapy (PERT), which restores normal nutrient breakdown.
Mucosal Healing: For autoimmune or inflammatory enteropathies, strict adherence to specialized diets (such as a gluten-free diet for celiac disease) allows the intestinal brush border to regenerate over time, normalizing water absorption and restoring gastrointestinal health.
Clinical Note: While acute osmotic episodes from dietary indiscretion are typically self-limiting, persistent or chronic osmotic diarrhea warrants a thorough medical evaluation to rule out underlying structural enteropathies, malabsorption syndromes, or covert laxative use.