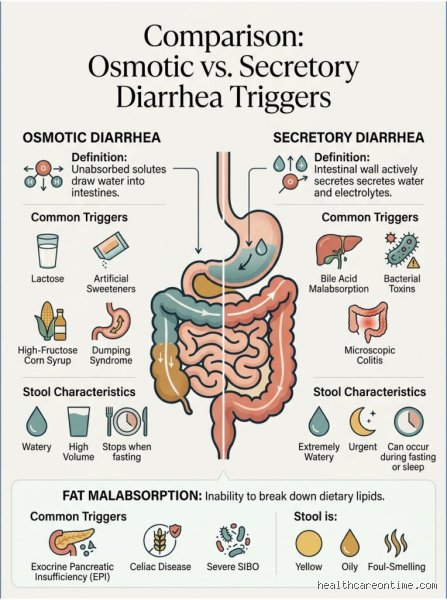
We live in an era of extreme dietary scrutiny. People obsess over macronutrients, glycemic loads, fermentable fibers, and gut microbiomes, scrolling endlessly through wellness blogs looking for the secret to optimal digestion. Yet, despite our cultural fixation on what we eat, most people completely misunderstand one of the most fundamental physical mechanisms governing the human gastrointestinal tract. They do not think about this enough.
When digestive distress strikes—cramps, sudden bloating, urgent watery bowel movements—our minds immediately jump to food poisoning, viral gastroenteritis, or perhaps a sudden flare-up of an irritable bowel. We blame the chicken salad from lunch or the suspicious leftovers in the back of the fridge. But more often than not, the culprit isn't a pathogen or an infection at all. It is a quiet, relentless rule of physics playing out inside your small intestine: the laws of osmosis.
Conventional medical wisdom often treats dietary diarrhea as a blunt instrument, categorizing all loose stools under the broad umbrellas of irritation, inflammation, or bacterial contamination. We are told to eat bland diets, drink electrolytes, and wait for our immune systems to clear out whatever microscopic invader has supposedly laid siege to our gut. But that changes everything once you realize that a significant portion of acute and chronic digestive distress is not an immune response or an infection. It is purely physical. It is a massive, microscopic fluid shift driven by concentration gradients, and the triggers are often everyday foods hiding in plain sight on supermarket shelves.
Far from being a rare medical anomaly, osmotic diarrhea is happening around us every day—sometimes to us, right after we finish a seemingly healthy snack or a sugar-free treat. And contrary to popular belief, we're far from it when we assume that fiber and healthy eating are universally protective against this phenomenon. In fact, some of the very foods we adopt in the name of wellness are prime architects of osmotic chaos.
The Physics of the Flush: Understanding Osmosis in the Gut
To grasp why certain foods trigger a sudden, watery evacuation, we have to look past the biology of digestion and examine basic chemistry. The human gastrointestinal tract is an extraordinarily sophisticated processing plant. Every day, it handles liters of ingested fluids, digestive enzymes, biliary secretions, and mucus, efficiently reabsorbing nearly all of that liquid before it ever reaches the colon.
In a healthy digestive system, the lining of the small intestine acts as a semi-permeable membrane. It absorbs water passively, following the movement of nutrients—primarily sodium, glucose, and amino acids—transported across the intestinal epithelial cells via active transport mechanisms. Water follows solute through a process called solvent drag and osmotic coupling. When you eat a meal, your intestines break down complex carbohydrates, proteins, and fats into smaller molecules, absorbing them along with water, leaving the remaining digesta relatively isotonic (balanced in solute concentration) by the time it reaches the large intestine.
However, this delicate balance shatters when you ingest specific substances that the small intestine cannot adequately digest, break down, or absorb.
When unabsorbed, osmotically active molecules remain trapped inside the lumen of the small intestine. Because these molecules cannot cross the intestinal wall into the bloodstream, they stay put, acting like microscopic sponges. To restore chemical equilibrium between the contents of the intestine and the body's internal tissues, water is aggressively drawn out of the bloodstream, through the intestinal wall, and directly into the gut lumen.
Imagine pouring dry salt onto a wet surface; the salt pulls moisture toward it. Similarly, an influx of poorly absorbed solutes in your digestive tract creates a high-osmolarity environment. The body responds by flooding the intestine with water to dilute those trapped particles. By the time this heavily diluted, fluid-heavy mixture overwhelms the small intestine and surges into the colon, the large intestine—which has a finite capacity for reabsorbing water—simply cannot keep up. The result is a sudden, voluminous, watery discharge: classic osmotic diarrhea.
The Sugar-Alcohol Paradox: Sweeteners That Trap Water
One of the most common and misunderstood triggers of osmotic diarrhea is a class of compounds known as polyols, or sugar alcohols. Found abundantly in modern "diet," "sugar-free," and keto-friendly products, these ingredients are marketed as healthy alternatives to table sugar because they have a lower glycemic index and fewer calories.
Common sugar alcohols include:
Sorbitol (found naturally in stone fruits like prunes, peaches, and cherries, and heavily synthesized as an artificial sweetener in sugar-free gums and candies)
Xylitol (widely used in sugar-free chewing gums, mints, and diabetic-friendly baked goods)
Mannitol (used in medications, diet foods, and as a dusting powder for chewing gum)
Maltitol (a staple in sugar-free chocolates, protein bars, and syrups)
The human body struggles to process these compounds efficiently. Unlike glucose, which is rapidly and actively absorbed across the brush border of the small intestine, sugar alcohols are passively absorbed, and they cross the intestinal epithelium at a remarkably slow rate.
When you consume a large quantity of sugar-free candy or several "keto" protein bars sweetened with maltitol, your small intestine becomes completely bottlenecked. The enzymes simply cannot clear the influx of polyols fast enough. As these unabsorbed sugar alcohols travel down the digestive tract, they create a massive osmotic gradient.
Water rushes from the body's tissues into the intestinal lumen to dilute the accumulating polyols. Furthermore, once these sugar alcohols finally reach the large intestine (the colon), the resident microbiome feasts on them through bacterial fermentation. This fermentation process produces large volumes of gas—hydrogen, carbon dioxide, and methane—leading to severe bloating, abdominal distention, and explosive flatulence, all while the unabsorbed polyols continue to hold onto water inside the colon.
It is a double-whammy of digestive distress: osmotic fluid drawing paired with intense gas production. People often experience this after a movie night featuring a whole bag of sugar-free gummy bears, wondering why a calorie-free snack caused a gastrointestinal emergency. The answer lies entirely in the osmotic pressure exerted by the trapped sugar alcohols.
Fructose Malabsorption: When Fruit Becomes a Burden
We are conditioned from childhood to believe that fruit is universally good for us. Apples, pears, mangoes, watermelons, and cherries are praised for their vitamins, antioxidants, and dietary fiber. Yet, for a surprising number of people, eating a large fruit salad or drinking a glass of 100% fruit juice can trigger rapid, painful osmotic diarrhea.
The culprit here is fructose, a simple monosaccharide found naturally in fruits, honey, and high-fructose corn syrup (HFCS).
In humans, fructose absorption in the small intestine relies primarily on a specific transport protein embedded in the cell membranes called GLUT5, working alongside another transporter called GLUT2. Unlike glucose, which is absorbed quickly and efficiently via dedicated sodium-dependent transporters (SGLT1), fructose transport has a strictly limited capacity. It is a passive, facilitated diffusion process that can easily become saturated.
When you consume a food where fructose is present in quantities that significantly exceed the amount of glucose, or simply when you ingest an extremely high dose of free fructose all at once, the GLUT5 transporters become completely overwhelmed. This condition is known as dietary fructose malabsorption.
The unabsorbed excess fructose remains trapped in the lumen of the small intestine. Just like sugar alcohols, free fructose molecules act as osmotically active solutes. They hold onto water, prevent normal reabsorption, and draw additional fluid out of the intestinal wall. When this sugar-laden, water-logged chyme hits the large intestine, it creates a dual problem:
Osmotic fluid accumulation, causing watery stools and sudden urgency.
Rapid bacterial fermentation, as colonic bacteria rapidly ferment the excess fructose, producing copious gas and metabolic byproducts that cause cramping and severe discomfort.
What makes fructose malabsorption particularly tricky is that the presence of glucose actually enhances fructose absorption by recruiting additional transport mechanisms (GLUT2). This is why a fruit containing equal parts glucose and fructose (like a banana) is often much easier on the stomach than a food containing an excess of free fructose (like a pear, an apple, or a glass of apple juice). When the ratio tilts heavily toward unbound fructose, the risk of triggering an osmotic flush sky-rockets.
Lactose Intolerance: The Enzyme Deficiency That Drives Fluid Shifts
Perhaps the most classic and widespread example of osmotic diarrhea is lactose intolerance—a condition affecting a vast majority of the world's adult population.
Lactose is the primary disaccharide sugar found in mammalian milk. To be absorbed by the small intestine, lactose must be cleaved into its two constituent monosaccharides—glucose and galactose—by an enzyme called lactase, which is anchored to the brush border of the small intestinal enterocytes.
In infancy and early childhood, lactase production is robust. However, in approximately 65 to 70 percent of the global human population, the gene responsible for lactase production undergoes a programmed downregulation after weaning, leading to primary lactase non-persistence (commonly called adult-onset lactose intolerance).
When an adult with low lactase activity consumes a glass of milk, a bowl of ice cream, or a large serving of fresh cheese, the unhydrolyzed lactose molecules cannot be absorbed by the small intestine. Intestinal cells lack the transport proteins necessary to absorb disaccharides directly; they can only absorb single-ring monosaccharides.
Consequently, the intact lactose molecules remain stranded in the intestinal lumen. Acting as potent osmotically active particles, they exert osmotic pressure, pulling extracellular fluid and water from the intestinal mucosa into the lumen.
By the time the lactose-and-water mixture reaches the ileum and enters the colon, the volume is massive. Furthermore, colonic bacteria eagerly ferment the undigested lactose, generating short-chain fatty acids, hydrogen gas, and carbon dioxide. The combination of unabsorbed lactose holding onto water (osmotic diarrhea) and bacterial fermentation producing gas creates the classic symptoms of lactose intolerance: watery diarrhea, explosive gas, borborygmi (stomach rumbling), and severe abdominal cramping within 30 to 120 minutes of consumption.
Artificial Sweeteners and Beyond: The Hidden Additives in Processed Foods
Beyond naturally occurring sugars and polyols, the modern food supply is saturated with synthetic compounds and food additives designed to alter texture, enhance shelf life, or reduce calorie counts. Many of these compounds possess inherent osmotic properties that can catch the digestive system off guard.
Consider polydextrose, maltodextrin, and various chemical thickeners and stabilizers used in low-fat or "diet" processed foods. While some are inert, others can act as osmotic agents when consumed in large quantities. Similarly, certain mineral-based additives or laxatives—such as magnesium citrate or magnesium sulfate (Epsom salts)—are explicitly used for their potent osmotic effects in clinical settings to clear out the bowels before medical procedures.
However, people frequently ingest magnesium supplements, antacids containing magnesium hydroxide, or specific mineral waters in quantities high enough to unintentionally trigger mild to moderate osmotic diarrhea. Magnesium ions are poorly absorbed in the small intestine; as they accumulate, they draw water into the intestinal lumen via osmosis, directly stimulating peristalsis and resulting in a laxative effect.
Understanding these mechanisms shifts our perspective entirely. Diarrhea is not always an infection to be fought off with antibiotics or a mysterious ailment to be endured; frequently, it is simply chemistry in action—a direct physiological consequence of putting molecules into our digestive tract that our bodies cannot break down and absorb.
Clinical Manifestations and Diagnostic Differentiation
Understanding how foods induce osmotic diarrhea requires a clear distinction between osmotic diarrhea and its secretory or motility-driven counterparts. Osmotic diarrhea is fundamentally characterized by its cessation during periods of fasting or when the offending solute is completely removed from the diet. When osmotically active, poorly absorbed molecules remain within the intestinal lumen, they create an osmotic gradient that draws extracellular fluid and electrolytes across the mucosa and into the lumen.
Detailed Breakdown of Primary Dietary Culprits
1. Polyols and Sugar Alcohols
Sugar alcohols—including sorbitol, xylitol, mannitol, and isomalt—are widely utilized as low-calorie sweeteners in "diet" foods, sugar-free chewing gums, pharmaceuticals, and diabetic-friendly snacks.
2. Fructose Malabsorption and Excess Free Fructose
Natural fruits, honey, agave nectar, and high-fructose corn syrup (HFCS) deliver substantial quantities of fructose.
When free fructose outnumbers available glucose molecules, unabsorbed fructose travels down to the lower gastrointestinal tract.
3. Lactose Intolerance and Disaccharide Deficiencies
Lactose, the primary sugar found in mammalian milk, must be hydrolyzed by the brush-border enzyme lactase into constituent monosaccharides (glucose and galactose) before absorption can occur.
Diagnostic Approach and Clinical Management
When patients present with chronic or recurrent postprandial diarrhea linked to osmotic triggers, clinicians typically follow a structured diagnostic pathway:
Detailed Dietary and Symptom Logging: Correlating the exact timing of loose stools with specific food intake (e.g., sugar-free products or large fruit portions) often pinpoints the offending dietary agent.
Elimination Diets and Structured Challenges: Removing suspected categories—such as high-FODMAP foods or artificial sweeteners—for a trial window of two to four weeks, followed by systematic single-food reintroductions.
Exclusion of Secondary Pathology: Ensuring symptoms are not driven by inflammatory bowel disease (IBD), celiac disease, or chronic infections that compromise overall mucosal absorptive surface area.
Management centers primarily on targeted dietary modifications, portion management, and reading packaged food labels to catch hidden sources of sorbitol, HFCS, and lactose. Ensuring adequate hydration during acute episodes remains vital to offset electrolyte shifts.