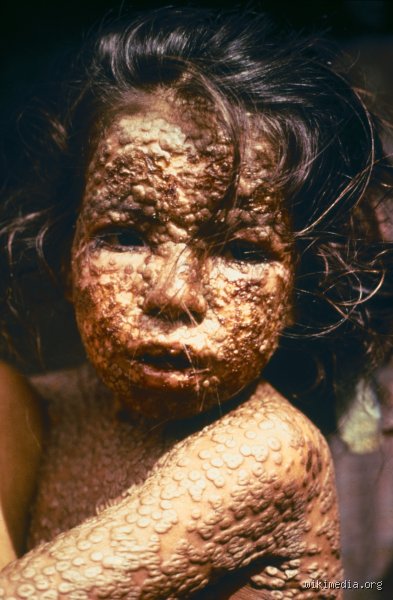
For millennia, few entities struck as much terror into the human imagination as smallpox. Caused by the Variola virus—a member of the Orthopoxvirus genus—this ancient scourge shaped the course of empires, decimated indigenous populations upon contact with new trade and exploration routes, and left survivors permanently scarred or blind.
To understand the lethality of smallpox, one must look beyond a simple viral infection. Smallpox was a systemic, multi-organ assault driven by an extraordinary evolutionary arms race between the pathogen and the human immune system. Its high case-fatality rate—averaging roughly 30% for the most common severe form (Variola major) and soaring near 100% for malignant and flat variants—was not the result of a single flaw in human biology, but rather the consequence of a sophisticated suite of immune-evasion tactics, overwhelming viremia, and catastrophic systemic inflammation.
1. The Evolutionary Profile of Variola Major
The genus Poxviridae, and specifically the chordopoxviruses that infect vertebrates, represents some of the largest and most complex viruses known to science. Unlike many common human viruses (such as influenza or rhinoviruses) that possess minimal genetic material relying heavily on host machinery, the Variola virus possesses a massive double-stranded DNA genome comprising roughly 186,000 base pairs encoding over 200 proteins.
This vast genetic footprint gave Variola a distinct evolutionary advantage. Rather than merely hijacking host cells to replicate, the virus brought its own comprehensive toolkit for cellular manipulation. A significant portion of the viral genome is dedicated not to structural components of the virion itself, but to "immunomodulatory proteins." These proteins acted as biochemical saboteurs, specifically engineered to intercept, mimic, and neutralize human cytokine signaling, complement activation, and inflammatory responses.
Because smallpox was strictly a human pathogen—having no known animal reservoir or vector like mosquitoes—it evolved alongside human populations for at least three millennia.
2. Transmission, Entry, and the Initial Silent Phase
The pathogenesis of smallpox began quietly, masking its deadly intent during the initial days of infection. Transmission occurred primarily via person-to-person contact through respiratory droplets shed from the mucous membranes of the upper respiratory tract, or more directly through contact with the characteristic skin lesions and scabs.
Once inhaled or deposited onto the oropharyngeal or respiratory mucosa, the virus encountered its first line of defense: the innate immune system residing in the respiratory epithelium. However, Variola was uniquely equipped to bypass these initial barriers.
The Incubation Period
Initial Deposition: The virus infects macrophages and dendritic cells in the respiratory mucosa without triggering an immediate, localized inflammatory warning.
Lymphatic Spread: Infected phagocytic cells migrate to regional lymph nodes, allowing the virus to multiply silently away from immediate immune surveillance.
Primary Viremia: Around the third or fourth day, the virus enters the bloodstream (primary viremia), spreading quietly to secondary internal organs including the spleen, bone marrow, and liver.
During this incubation period—which typically lasted between 7 to 17 days—the patient experienced no symptoms and remained entirely unaware that a systemic invasion was underway. The virus used this window to replicate extensively within internal organs, setting the stage for a sudden and catastrophic secondary release into the bloodstream.
3. Secondary Viremia and the Onset of Toxicity
The turning point of a smallpox infection occurred roughly around the tenth to twelfth day, coinciding with secondary viremia. At this stage, massive quantities of newly replicated virus particles burst from internal tissues back into the circulatory system, flooding the bloodstream and initiating systemic toxicity.
This massive surge of circulating viral antigens and virions triggered a severe systemic reaction. Patients who had felt entirely normal abruptly plummeted into a state of high fever, severe prostration, rigors, headache, and intense backache. This prodromal phase signaled that the infection had transitioned from a localized exposure to a systemic crisis.
The sheer viral load in the blood during secondary viremia played a direct role in patient prognosis. High viral titers correlated closely with the most severe clinical presentations, foreshadowing whether a patient would develop ordinary smallpox, or the catastrophically fatal flat or hemorrhagic variants.
4. Disruption of the Immune System: Cytokine Storms and Complement Evasion
Why didn't the human immune system simply clear the virus during secondary viremia? The answer lies in Variola's intricate arsenal of molecular decoys. The virus produced structural mimics of human complement regulatory proteins and cytokine receptors.
Complement Inhibition: The complement cascade is a crucial component of the innate immune system designed to lyse pathogens and flag them for destruction. Variola proteins actively bound to and deactivated complement components, preventing the lysis of virus particles and dampening the recruitment of inflammatory cells.
Interference with Interferons: Interferons are critical signalling proteins released by virus-infected cells to warn neighboring cells and activate natural killer (NK) cells. Variola expressed proteins that bound directly to human interferons, effectively jamming the cellular alarm system.
Chemokine Scavenging: By releasing soluble decoy receptors that bound chemokines, the virus disrupted the chemical gradients required to guide white blood cells to the site of infection.
Paradoxically, while the virus attempted to suppress specific immune pathways, the sheer magnitude of the systemic infection often provoked a runaway inflammatory response known colloquially today as a "cytokine storm." The body's frantic attempt to control the pathogen resulted in systemic endothelial damage, vascular leakage, and widespread tissue destruction, compounding the direct cytopathic effects of the virus itself.
5. Pathological Impact on the Skin and Mucous Membranes
As secondary viremia seeded the skin and mucosal surfaces, the classic hallmark of smallpox manifested: the enanthem and the exanthem.
The virus had a distinct tropism for the dermal-epidermal junction. Infected cells swelled, degenerated, and ruptured, forming fluid-filled vesicles that eventually evolved into pustules. Unlike chickenpox (caused by the Varicella-zoster virus), which erupts in successive crops and centers primarily on the torso, smallpox lesions developed synchronously—appearing all at once—and exhibited a characteristic centrifugal distribution, concentrating heavily on the face, arms, and legs.
The mucosal lesions in the mouth, pharynx, and upper airway were equally critical. As these lesions ulcerated, they shed staggering numbers of infectious virions into the saliva and respiratory secretions. This mucosal breakdown not only facilitated transmission to new hosts but also compromised the airway integrity of the patient, opening the door to secondary bacterial superinfections.
Looking Ahead
The complex interplay between Variola's genetic immunomodulators, its silent incubation, and the explosive secondary viremia explains the initial stages of its terrifying lethality. However, the ultimate cause of death varied depending on the clinical classification of the disease—ranging from the immune-mediated collapse in flat-type smallpox to secondary bacterial pneumonia and toxemia in ordinary-type infections.
In the second part of this expert analysis, we will explore the specific clinical manifestations, the role of cardiovascular collapse, and the immunological factors that determined why some individuals survived while the vast majority succumbed to the infection.
What specific aspect of smallpox pathogenesis or historical control measures would you like to explore further in relation to its clinical impact?
The Pathological Cascade: Systemic Collapse and Immune Evasion
To truly comprehend why the variola virus held such absolute dominion over human mortality—claiming approximately 30% of those it infected and leaving survivors permanently scarred or blind—one must examine the multi-systemic catastrophe it triggered within the body. Unlike pathogens that target a single organ system, variola major executed a synchronized assault on multiple physiological fronts, plunging the host into a profound state of biological disarray.
Once the virus breached the respiratory mucosa and bypassed early innate defenses, it systematically hijacked the lymphatic system, multiplying unchecked before seeding into the bloodstream (secondary viremia). This massive viral load initiated a relentless chain reaction:
Direct Cytotoxicity: The sheer volume of replicating virus particles caused widespread cell lysis and tissue destruction across vital organs, most notably the skin, liver, spleen, and bone marrow.
Vascular Compromise and Hypotension: Extensive endothelial damage permitted plasma leakage, precipitating dangerous drops in blood pressure and predisposing patients to hypovolemic shock.
Secondary Organ Failure: Severe inflammation of the respiratory tract frequently culminated in viral or secondary bacterial pneumonia, starving vital tissues of oxygen. Simultaneously, acute kidney injury and hepatic impairment compromised the body's primary filtration and metabolic safety nets.
Malignant and Hemorrhagic Variants: The Ultimate Expressions of Lethality
While ordinary-type smallpox accounted for the majority of cases with a staggering one-in-three fatality rate, the virus possessed even more terrifying phenotypes that pushed human survivability to its absolute limit: flat-type (malignant) and hemorrhagic smallpox.
In flat-type smallpox, the classic fluid-filled vesicles failed to mature properly.
In hemorrhagic smallpox, the virus directly targeted the clotting cascade and vascular integrity. Rather than developing a pustular rash, victims experienced catastrophic internal and external bleeding.
Immune Subversion: Outsmarting the Human Shield
The lethality of smallpox cannot be separated from its evolutionary arms race with the human immune system. Over millennia, the variola virus engineered a sophisticated arsenal of immunomodulatory proteins designed to neutralize or deceive host defenses.
The virus produced specialized proteins that molecularly mimic human cytokines and chemokines, effectively throwing molecular "jamming signals" into the body’s communication network. By intercepting interferons and dampening inflammatory signaling, variola delayed the deployment of adaptive immunity. This evasion window allowed the virus to replicate to catastrophic titers before T-cells and neutralizing antibodies could mount a coordinated counter-offensive. By the time the immune system recognized the scale of the invasion, the tissue damage was already irreversible.
Conclusion: The Triumph Over a Masterclass in Pathogenicity
Smallpox was not fatal due to a single mechanical failure, but because it operated as a multi-systemic destroyer equipped with precision immune-evasion tools and devastating tissue-destroying variants. Its elimination through global vaccination stands as one of the crowning achievements of modern medicine, permanently neutralizing a pathogen that had shaped human history, demography, and evolution for thousands of years.
What aspects of viral immunology or historical epidemiology would you like to explore next?