Sorry, something went wrong. Please try your request again.
Prescribed and Over-the-Counter Pharmacological Triggers
While dietary choices and metabolic factors exert a slow, cumulative effect on prostate growth and overall systemic inflammation, certain common medications can trigger acute urinary retention or significantly worsen lower urinary tract symptoms (LUTS) almost immediately. Understanding how over-the-counter (OTC) and prescription drugs interact with bladder and prostate physiology is essential for avoiding sudden clinical crises.
Decongestants and Sympathomimetics
Over-the-counter cold and sinus remedies routinely contain sympathomimetic agents such as pseudoephedrine, phenylephrine, or oxymetazoline. These compounds work as alpha-1 adrenergic receptor agonists, intended to constrict dilated blood vessels in the nasal passages.
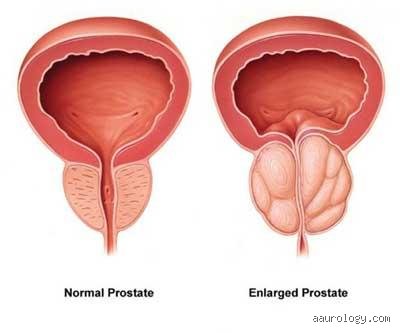
However, alpha-1 receptors are also concentrated in high density within the smooth muscle tissue of the prostate capsule and the bladder neck. When an alpha-agonist circulates systemically, it causes these smooth muscle fibers to contract tightly, further narrowing the prostatic urethra. For a man with baseline luminal narrowing due to BPH, taking a standard dose of an oral decongestant can abruptly transform partial urinary hesitation into complete acute urinary retention—a painful medical emergency requiring catheterization.
Anticholinergic Medications and First-Generation Antihistamines
Many common medications possess anticholinergic properties, including first-generation antihistamines (e.g., diphenhydramine, chlorpheniramine), tricyclic antidepressants (e.g., amitriptyline), and drugs for overactive bladder (e.g., oxybutynin).
Anticholinergics block acetylcholine from binding to muscarinic receptors on the detrusor muscle—the smooth muscle wall of the bladder responsible for contracting to expel urine. Inhibiting the detrusor muscle reduces its contractile strength. In a healthy bladder, this may cause minimal disruption; in a bladder already working against high outflow resistance caused by an enlarged prostate, weakened detrusor contractions prevent effective emptying. This leads to high post-void residual volumes, increased urinary frequency, overflow incontinence, and elevated risks of urinary tract infections (UTIs) or bladder stones.
Diuretics
Prescribed widely for hypertension and congestive heart failure, loop diuretics (e.g., furosemide) and thiazide diuretics (e.g., hydrochlorothiazide) accelerate renal urine production. The resulting surge in volume overwhelms the bladder's diminished capacity, causing severe urinary urgency and frequency. When taken late in the afternoon or evening, diuretics dramatically worsen nocturia, disrupting sleep cycles and impairing overall health.
Lifestyle Behaviors and Urinary Dynamics
Day-to-day habits directly influence the physical mechanics of the bladder, pelvic floor, and prostate gland. Even modest behavioral adjustments can significantly relieve baseline symptom severity.
 [ Sedentary Lifestyle / Prolonged Sitting ]
 │
 ▼
 [ Increased Pelvic Congestion ]
 │
 ▼
 [ Higher Sympathetic Tone (Stress) ] ──► [ Smooth Muscle Spasm ]
 │ │
 └───────────┬────────────┘
 │
 ▼
 [ Exacerbated BPH Symptoms ]
Sedentary Behavior and Prolonged Sitting
Extended periods of sitting—common in desk-bound occupations or during long commutes—cause localized pelvic venous congestion. Blood pools in the pelvic venous plexus, increasing pressure within the surrounding tissues and temporarily worsening prostate swelling. Sedentary habits also correlate with reduced pelvic floor muscular tone and poor metabolic health, both of which are documented independent risk factors for rapid BPH progression.
Conversely, regular moderate aerobic exercise (such as brisk walking or swimming) lowers systemic inflammation, reduces sympathetic nervous system tone, improves metabolic profiles, and reduces nocturnal urinary frequency.
Fluid Management and Dysregulated Intake Timing
Inadequate or mismanaged fluid intake can aggravate lower urinary tract symptoms:
Severe Fluid Restriction: Men experiencing frequency often intentionally limit their water intake. However, underhydration causes urine to become highly concentrated with urea and acidic metabolic waste products.
Concentrated urine acts as a direct chemical irritant to the bladder mucosa, triggering involuntary detrusor contractions and paradoxical surges in urinary urgency. Bolus Fluid Intake: Drinking large quantities of liquid in a short window stretches the bladder wall rapidly, triggering urgent detrusor spasms that an obstructed prostate cannot easily accommodate.
Late-Evening Consumption: Consuming significant fluid volumes within two to three hours of sleep guarantees increased nocturnal urine output, amplifying nocturia.
Delayed Voiding Habits
Voluntarily suppressing the urge to urinate—whether due to lack of bathroom access, occupation, or habit—forces the bladder to overdistend. Chronic overstretching damages the detrusor muscle's collagen matrix and nerve supply, compromising its long-term ability to contract effectively. Over time, this leads to decompensation of the bladder wall, urinary retention, and chronic incomplete emptying.
Psychological Stress and Neurogenic Interactions
The lower urinary tract is densely innervated by the autonomic nervous system. The autonomic interplay between stress and prostatic function is a frequently overlooked driver of symptom flare-ups.
Psychological stress, chronic anxiety, and sleep deprivation stimulate the sympathetic nervous system, causing elevated systemic levels of catecholamines (adrenaline and noradrenaline). Catecholamines bind to the abundant alpha-1 adrenergic receptors located throughout the prostate capsule and bladder neck, causing acute smooth muscle hypertonicity.
This stress-induced spasm physically constricts the prostatic urethra, making voiding significantly more difficult during periods of high emotional strain. Furthermore, stress heightened central nervous system sensitivity lowers the threshold at which the brain registers bladder filling, compounding feelings of urgency and frequency even when actual bladder volume is low.
Comparative Overview of Risk Factors
To aid clinical risk stratification, the key exacerbating factors of BPH and their primary physiological mechanisms are summarized below:
Comprehensive Management and Prevention Strategies
Mitigating BPH progression requires a systematic approach combining targeted dietary adjustments, behavioral modifications, and careful medication management.
 [ Comprehensive BPH Management ]
 │
 ┌───────────────────────┼───────────────────────┐
 ▼ ▼ ▼
[ Dietary Optimization ] [ Behavioral Therapy ] [ Clinical Oversight ]
 • Reduce saturated fat • Double-voiding • Medication review
 • Cut caffeine/alcohol • Timed fluid intake • Annual IPSS/PSA
 • Increase lycopene • Aerobic movement • Tailored therapy
Dietary Optimization: Prioritize a plant-forward or Mediterranean-style diet rich in polyphenols, zinc, and lycopene (found in cooked tomatoes) while minimizing saturated animal fats, refined sugars, and ultra-processed foods.
Behavioral and Fluid Modifications: Implement timed fluid intake—aiming for adequate daily hydration while restricting fluids two to three hours before bedtime. Utilize "double-voiding" techniques (waiting a few moments after urinating to try emptying the bladder a second time) to reduce post-void residual volume.
Medication Oversight: Review all over-the-counter and prescription drugs with a physician or pharmacist to identify and replace compounds that impair bladder contraction or increase urethral resistance.
Physical Activity and Weight Management: Engage in at least 150 minutes of moderate aerobic exercise weekly to improve metabolic parameters, reduce pelvic congestion, and lower sympathetic nerve activity.
Managing an enlarged prostate requires recognizing that BPH is not merely an isolated structural issue of the prostate gland, but a multi-factorial condition sensitive to systemic metabolic health, pharmacological exposures, and daily habits.