Please provide the prompt or question for Part 1, and I will be happy to help!
I will generate the continuation and conclusion of the medical comparative article in a Markdown document.
Procedural Complexity and Anesthesia Considerations
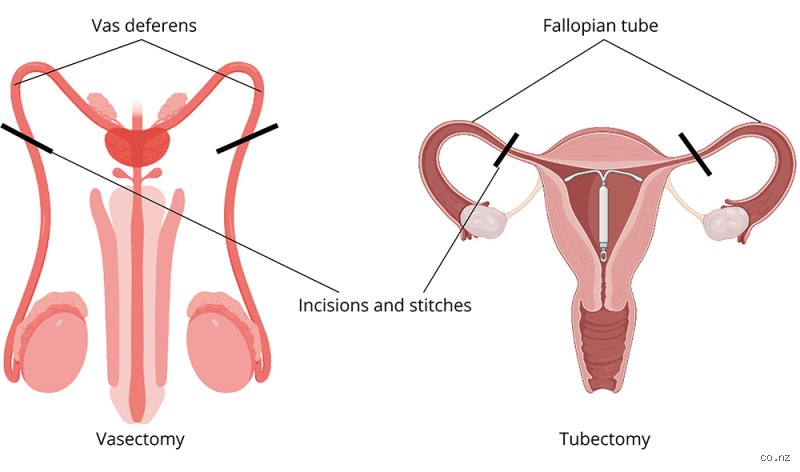
Vasectomy is a minimally invasive outpatient procedure performed outside the abdominal cavity. Because the vas deferens lies just beneath the scrotal skin, the clinician requires only local anesthesia (often paired with mild oral sedation if requested by the patient). The surgical insult is localized, short-lived, and does not require entering any major bodily cavities.
In contrast, tubal ligation (and its modern standard, bilateral salpingectomy—the complete removal of the fallopian tubes) requires intra-abdominal access. Accessing the fallopian tubes typically involves:
Laparoscopy or Mini-Laparotomy: Inserting instruments and cameras through small abdominal incisions.
Insufflation: Inflating the peritoneal cavity with carbon dioxide (
CO2 ) gas to create a working space for the surgeon.General Anesthesia: Requiring endotracheal intubation and mechanical ventilation.
The necessity of general anesthesia alone shifts the risk baseline significantly. While general anesthesia is safe for healthy individuals, it inherently carries risks that local anesthesia does not, including airway trauma, cardiovascular instability, adverse drug reactions, and postoperative nausea or respiratory depression. Furthermore, introducing sharp trocars or instruments into an inflated abdomen carries a low, but non-zero, risk of accidental bowel, bladder, or vascular injury.
+-------------------------------------------------------------------------------+
| PROCEDURAL RISK PROFILE MATRIX |
+--------------------------+-------------------------+--------------------------+
| Parameter | Vasectomy | Tubal Ligation |
+--------------------------+-------------------------+--------------------------+
| Primary Anesthesia | Local Anesthesia | General Anesthesia |
| Anatomical Access | Extraperitoneal | Intra-abdominal |
| Procedure Duration | 10 – 30 Minutes | 30 – 60 Minutes |
| Major Organ Risk | Virtually Zero | Low (Bowel/Bladder/Vessel)|
| Recovery Timeframe | 2 – 4 Days | 1 – 2 Weeks |
+--------------------------+-------------------------+--------------------------+
Short-Term Complications: Side-by-Side Comparison
Both procedures demonstrate low overall rate of serious early complications, but the types and severities of these complications differ markedly.
Short-Term Risks of Vasectomy
Hematoma: Blood accumulation within the scrotum occurs in roughly
1% to2% of cases. While uncomfortable, most resolve with rest, cold therapy, and supportive care.Infection: Local skin or superficial wound infections occur at rates under
2% and respond well to standard oral antibiotic therapy.Sperm Granuloma: A benign nodule formed by leaking sperm provoking a localized immune response, usually harmless and self-limiting.
Short-Term Risks of Tubal Ligation
Visceral or Vascular Injury: Unintended trauma to the intestines, urinary bladder, or abdominal blood vessels occurs in approximately
0.1% to0.6% of laparoscopic procedures, occasionally requiring immediate open surgery (laparotomy) to repair.Infection and Bleeding: Wound infections