The nature of Parkinson's Progression
Parkinson's disease is fundamentally characterized by the progressive loss of dopamine-producing neurons in the substantia nigra region of the brain. Dopamine is a vital neurotransmitter responsible for facilitating smooth, coordinated muscle movement and regulating various autonomic and cognitive networks. As dopamine depletion deepens across years, the brain's internal signaling pathways become disrupted.
However, disease progression rarely follows a uniform, predictable straight line. Instead, it often unfolds through distinct phases marked by periods of relative stability interspersed with notable clinical shifts. Clinicians frequently utilize standardized scales—such as the Hoehn and Yahr staging system or the Movement Disorder Society-Sponsored Revision of the Unified Parkinson's Disease Rating Scale (MDS-UPDRS)—to quantify these changes. Recognizing when symptoms cross from mild, localized inconveniences into broader, more disabling challenges is the cornerstone of proactive medical management.
Escalation of core motor Symptoms
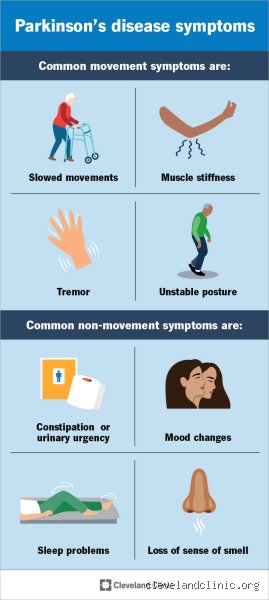
The most recognizable hallmarks of Parkinson's disease involve physical movement. In the early stages, these symptoms are typically asymmetric, affecting only one side or a single limb. As the disease advances, motor signs typically cross the body's midline, intensifying in frequency, duration, and functional impact.
1. Worsening bradykinesia and akinesia
Bradykinesia, or the profound slowness of movement, is one of the defining features of Parkinson's progression. Initially, individuals may notice that routine tasks, such as buttoning a shirt, tying shoes, typing on a keyboard, or cutting food, take significantly longer. As the condition worsens, slowness can transition into akinesia, which represents a complete difficulty in initiating movement. Patients may experience sudden brief episodes where their limbs feel entirely stuck, rendering simple physical actions frustratingly complex and time-consuming.
2. Spreading muscle rigidity
Muscle rigidity refers to a persistent stiffness or tightness in the limbs and trunk, even when the patient is at rest. In advanced phases, this rigidity intensifies, severely limiting the normal range of motion and frequently causing physical discomfort or persistent aching pain. When rigidity affects the chest wall and trunk muscles, it can also restrict deep breathing patterns and contribute to fatigue.
3. Altered tremor patterns
While tremors are often the initial symptom that prompts a medical evaluation, their behavior over time can vary. For some individuals, resting tremors become more pronounced, constant, or generalized across multiple limbs. Conversely, some patients develop a postural or kinetic tremor component that interferes directly with reaching, grasping, and holding objects during purposeful tasks.
4. Postural Instability and balance Impairment
Perhaps one of the most critical milestones in Parkinson's progression is the emergence of postural instability. As protective postural reflexes diminish, the body struggles to make automatic adjustments to maintain balance when shifting weight. This manifests as a stooped posture, a shuffling gait with reduced step length, and sudden freezing episodes where feet feel glued to the floor. Consequently, the frequency of trips and falls increases substantially, transforming balance issues into a primary safety concern.
Amplification of Non-Motor Symptoms
While physical movement changes capture immediate attention, non-motor symptoms often dictate the overall day-to-day quality of life. These internal symptoms can predate motor signs, but they frequently grow more severe and disruptive as the underlying neurodegeneration advances.
Cognitive Shifts and Memory Changes: Mild cognitive impairment may emerge several years after diagnosis, affecting executive functions such as planning, multitasking, and problem-solving. Over extended periods, a subset of individuals may develop Parkinson's disease dementia, introducing serious challenges with memory and daily orientation.
Autonomic Dysfunction: The autonomic nervous system regulates involuntary bodily functions. Worsening autonomic signs include persistent constipation, urinary urgency or incontinence, and neurogenic orthostatic hypotension, a sharp drop in blood pressure upon standing that can cause dizziness and lightheadedness.
Sleep Architecture Disruptions: Fragmented nighttime sleep, vivid dreaming associated with REM sleep behavior disorder, and excessive daytime somnolence frequently worsen over time, compounding physical fatigue.
Mood and Neuropsychiatric Fluctuations: Feelings of deep apathy, chronic anxiety, and clinical depression can intensify as neurological pathways shift. In more advanced phases, some individuals may experience visual hallucinations or delusions, often linked either to disease progression or as a side effect of long-term medication regimens.
Medication Fluctuations and treatment complications
Ironically, the very pharmaceutical therapies designed to manage Parkinson's symptoms can present new challenges as the condition progresses. Over years of treatment, the brain's ability to store dopamine diminishes, leading to changing responses to levodopa and other medications:
"Wearing-Off" Effect: Patients notice that their medication begins to wear off well before the next scheduled dose is due, causing symptoms to re-emerge prematurely.
"On-Off" Fluctuations: Transitions between therapeutic benefit ("on" periods where movement is relatively smooth) and severe symptom resurgence ("off" periods of intense stiffness and slowness) can become sudden and unpredictable.
Dyskinesias: Prolonged high-dose medication use can trigger dyskinesias, involuntary, erratic, writhing movements of the face, arms, or trunk that occur when dopamine levels peak.
Functional independence and Daily Living
The cumulative weight of motor and non-motor symptom progression translates into tangible changes in functional autonomy. Clinicians evaluate how well an individual manages Activities of Daily Living (ADLs), such as bathing, dressing, eating, and walking, alongside Instrumental Activities of Daily Living (IADLs), which include cooking, managing finances, and home maintenance.
When individuals require dedicated assistance with basic ADLs, or when walking requires continuous mobility aids like canes, walkers, or wheelchairs, the disease has entered its advanced stages. Recognizing these milestones early ensures that families and clinical care teams can seamlessly integrate physical therapy, speech therapy, nutritional support, and caregiver resources to optimize safety and comfort.
Recognizing the milestones of Progression: Advanced motor Changes
As Parkinson’s disease (PD) advances, the cardinal motor symptoms, bradykinesia (slowness of movement), rigidity, and resting tremors, frequently undergo qualitative transformations. While dopamine replacement therapies such as levodopa remain foundational, their long-term efficacy often becomes complicated by motor fluctuations and dyskinesias (involuntary, erratic movements).
A critical turning point in disease progression is the emergence of postural instability and## Advanced Progression: Recognizing Mid-to-Late Stage Transitions
As Parkinson's disease (PD) advances beyond the early phases, the nature of the symptoms shifts significantly. While initial manifestations are predominantly motor-related, such as a resting tremor, mild rigidity, or a slight slowing of movement (bradykinesia), later stages often introduce complex motor complications and non-motor symptoms that affect daily independence and cognitive well-being. Understanding these progressive milestones is crucial for patients, families, and caregivers to adapt management strategies, optimize quality of life, and prepare for appropriate levels of care.
1. The emergence of motor Fluctuations and Dyskinesia
One of the most definitive indicators that Parkinson's is progressing is the alteration in how the brain processes medication, specifically levodopa. Over time, as dopamine-producing neurons continue to degenerate, the brain's ability to store dopamine diminishes. This leads to predictable shifts in clinical status:
The "Wearing-Off" Phenomenon: Patients begin to notice that the therapeutic benefit of a medication dose wears off well before the next scheduled dose is due. This results in the re-emergence of stiffness, slowness, and tremors prior to the next pill time.
On-Off Fluctuations: Transitions between mobility ("on" periods where medication is working effectively) and immobility ("off" periods where symptoms return abruptly) become more unpredictable and rapid. These swings can occur multiple times a day.
Levodopa-Induced Dyskinesia: Paradoxically, as the body struggles to regulate dopamine levels, patients may experience involuntary, non-rhythmic movements, such as writhing, twisting, or swaying, typically during peak medication times. While not painful, severe dyskinesia can be physically exhausting and socially distressing.
2. Axial Symptoms and Postural Instability
As the disease spreads to non-dopaminergic brain networks, symptoms involving the body's central axis become more prominent. These features are frequently less responsive to standard dopaminergic medications and signal a more advanced stage of progression.
Gait Freezing and Festination: Patients may experience sudden, brief episodes where their feet feel glued to the floor, often when turning, initiating movement, or navigating narrow spaces like doorways. Festination involves an involuntary acceleration of steps, where the upper body leans forward over the center of gravity, increasing the risk of forward falls.
Postural Instability: Loss of reflexive postural adjustments makes maintaining balance exceptionally difficult. A gentle push or an unexpected uneven surface can easily result in a fall, as the body fails to make the rapid corrective stepping movements characteristic of healthy balance control.
Bulbar Symptoms: Swallowing difficulties (dysphagia) and quiet, breathy, or monotonous speech (hypophonia) often worsen. Managing saliva and safely swallowing various food textures require specialized speech and swallowing therapy to prevent aspiration pneumonia.
3. Deepening Non-Motor and Cognitive complications
While motor symptoms are the hallmark of Parkinson's, the non-motor aspects frequently dictate the overall quality of life in advanced stages. These symptoms reflect the widespread accumulation of alpha-synuclein pathology throughout the central and peripheral nervous systems.
Parkinson's Disease Dementia (PDD) and Mild Cognitive Impairment: Executive dysfunction, such as difficulties with planning, multitasking, attention, and working memory, often deepens. In some individuals, this progresses to characteristic dementia marked by visual hallucinations, fluctuating alertness, and profound challenges with spatial orientation.
Neuropsychiatric Changes: Heightened anxiety, clinical depression, and apathy are common. Medications used to treat motor symptoms can sometimes trigger or worsen visual hallucinations, paranoia, or impulse control disorders, requiring delicate medication adjustments by a movement disorder specialist.
Autonomic Dysfunction: The regulation of involuntary body functions becomes increasingly erratic. This includes worsening orthostatic hypotension (sharp drops in blood pressure upon standing that can cause dizziness or fainting), severe chronic constipation, urinary urgency or incontinence, and thermoregulatory issues such as excessive sweating or intolerance to cold.
4. Comprehensive management and Caregiver integration
Navigating advanced Parkinson's requires a multidisciplinary, proactive approach. Adjusting therapy is no longer just about managing stiffness; it involves balancing mobility with cognitive stability and fall prevention.
Advanced Therapies: For patients experiencing severe motor fluctuations that oral medications can no longer control, advanced therapeutic options may be evaluated. These include deep brain stimulation (DBS) surgery, continuous levodopa-carbidopa intestinal gel infusions administered via a portable pump, or subcutaneous apomorphine infusions.
Palliative and Supportive Care: Integrating palliative care early in the advanced stages provides an essential layer of support. It focuses on symptom relief, pain management, advance care planning, and emotional support for both the patient and their family.
Caregiver Sustainability: As care needs escalate around the clock, caregivers face high rates of physical strain, burnout, and emotional fatigue. Utilizing respite care, joining support networks, and establishing a reliable care team are vital components of sustainable long-term management.
Recognizing these signs early allows families to transition from reactive crisis management to structured, compassionate care planning, ensuring dignity, comfort, and the highest possible quality of life through every stage of the condition.