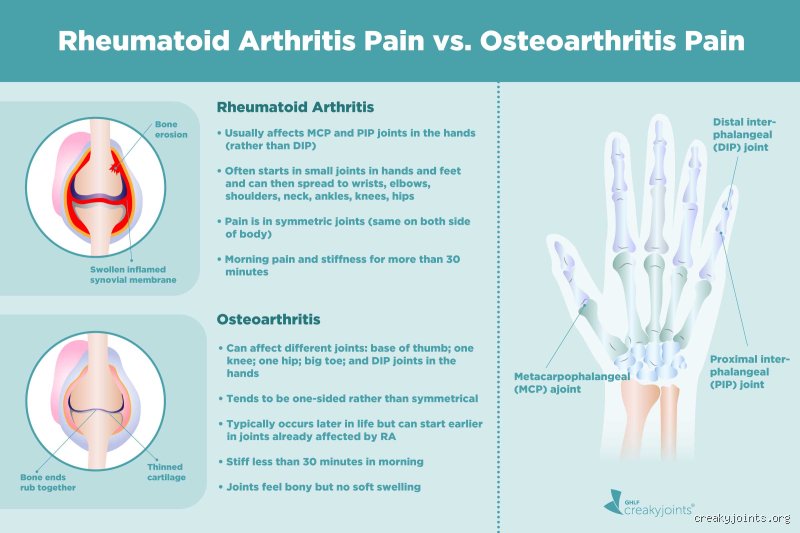
While both conditions share the common denominators of joint pain, stiffness, and restricted mobility, they are fundamentally different diseases. They stem from entirely different physiological mechanisms, target different parts of the body, behave differently throughout the day, and require completely distinct medical interventions. Mistaking one for the other can lead to delayed care and ineffective management.
This comprehensive, two-part expert guide will deconstruct the biological roots, clinical presentations, daily symptom patterns, and diagnostic markers that set these two conditions apart.
The core divide: Mechanical wear versus Systemic autoimmunity
To understand how to differentiate between osteoarthritis and rheumatoid arthritis, you must first understand why they happen. The single most important distinction between the two lies in their root causes: OA is a degenerative, mechanical disease, whereas RA is a systemic, autoimmune condition.
Osteoarthritis: The "Wear-and-Tear" Degeneration
Osteoarthritis is by far the most common form of arthritis. For decades, it was colloquially dismissed as simple "wear-and-tear," and while that label is a slight oversimplification—modern science recognizes OA as a complex disease involving the whole joint organ—the mechanical core remains true.
The Cartilage Breakdown: In a healthy joint, the ends of your bones are capped by a smooth, rubbery substance called articular cartilage. This tissue acts as a low-friction shock absorber, allowing bones to glide effortlessly against one another. Over years of use, mechanical stress, previous joint trauma (such as a sports injury or fracture), genetic predisposition, or age-related cellular changes, this protective cartilage begins to thin, fray, and eventually wear away entirely.
Bone-on-Bone Friction: As the cartilage cushion degrades, the space between the bones narrows. Eventually, bone rubs directly against bone. This friction triggers localized inflammation, remodeling of the bone structure, and the formation of bony projections known as osteophytes (bone spurs).
Localized Impact: Because OA is driven primarily by mechanical use and structural degradation, it is generally confined to the specific joints that bear the brunt of weight, impact, or repetitive motion, most commonly the knees, hips, spine, and the base of the thumbs or fingers. It does not attack the rest of your body or trigger systemic illness.
Rheumatoid Arthritis: The immune system's misdirected attack
Rheumatoid arthritis is an entirely different clinical entity. It is not caused by mechanical overuse or aging; rather, it is a chronic, systemic autoimmune disease.
The Autoimmune Trigger: In a person with RA, the immune system, which is normally designed to hunt down and destroy foreign invaders like bacteria and viruses, suffer a catastrophic signaling error. It mistakes the healthy tissue lining your joints (the synovium) for a dangerous threat.
The Synovial Siege: White blood cells flood the synovial membrane, causing it to become severely inflamed, thickened, and hyperactive. This aggressive tissue layer (known as a pannus) releases destructive enzymes that actively eat away at adjacent cartilage and erode the underlying bone.
Systemic Reach: Because the immune system circulates freely through the bloodstream, RA is rarely confined to just the joint capsules. It is a systemic illness, meaning it can trigger widespread bodily inflammation resulting in chronic fatigue, low-grade fevers, malaise, and occasional complications affecting external organs such as the heart, lungs, and eyes.
Decoding the daily clock: Morning Stiffness and Pain patterns
One of the most reliable diagnostic clues you can evaluate at home is when your joints hurt and how they respond to movement. The temporal behavior of arthritis pain provides a window straight into its biological origin.
The Osteoarthritis pattern: Activity-Driven Pain
If your joint pain follows a mechanical logic, it will usually look like this:
Worse with Use, Better with Rest: OA pain typically builds up over the course of the day as you use the affected joints. Walking long distances, climbing stairs, or typing for hours will exacerbate the ache because you are placing mechanical stress on un-cushioned bone surfaces. Rest and unloading the joint generally bring relief.
Brief Morning Stiffness: People with OA often experience stiffness after waking up, but it is notoriously short-lived, usually lasting less than 30 minutes (frequently under 15 minutes). Think of it like a rusty hinge: it takes a few moments of movement to loosen up, after which it functions reasonably well until it gets overworked later in the day.
The Rheumatoid Arthritis pattern: Rest-Driven inflammation
If your joint pain follows an inflammatory logic, the pattern is almost inverted:
Worse with Rest, Better with Movement: Inflammatory pain thrives on inactivity. When you sit still or sleep, inflammatory chemicals pool inside the joint capsule. Consequently, individuals with RA often experience intense pain and severe stiffness after prolonged periods of rest, such as sitting through a movie or waking up in the morning. Gentle movement and physical activity help disperse the fluid and ease the discomfort.
Prolonged Morning Stiffness: The hallmark clinical signature of RA is morning stiffness that lasts for an hour or significantly longer. Waking up feeling as though your hands are encased in thick concrete, unable to easily make a fist or turn your wrists for over 60 minutes, is a massive red flag pointing toward an inflammatory, autoimmune process.
Joint distribution and Symmetry: The map of your body
Another powerful way to differentiate between the two conditions is to look at which joints are hurting and where those aches are distributed across your frame.
Osteoarthritis: Asymmetrical and Weight-Bearing
Isolated and Selective: OA tends to target specific, high-stress sites. It frequently affects the knees, hips, lower back, and the distal interphalangeal joints (the finger joints closest to your fingernails, often producing bony knobs called Heberden's nodes).
Asymmetrical Nature: OA is typically asymmetrical. If you have severe osteoarthritis in your right knee due to an old soccer injury or uneven gait, your left knee may be entirely healthy or only mildly affected. It goes wherever mechanical stress or injury dictates.
Rheumatoid Arthritis: Symmetrical and Small-Joint focused
The Rule of Symmetry: One of the most unique and reliable features of RA is its symmetrical presentation. If your left wrist is inflamed, swollen, and painful, there is a very high probability that your right wrist will experience the exact same symptoms. This mirror-image distribution reflects the systemic nature of an immune system circulating evenly through both sides of the body.
Small Joints First: Unlike OA, which heavily favors large, weight-bearing joints early on, RA typically makes its initial debut in the small joints of the hands (the knuckles and middle finger joints) and the feet. Over time, as the disease progresses unchecked, it can march upward into larger joints like the wrists, elbows, knees, ankles, and shoulders.
Summary checklist for part 1
| Feature | Osteoarthritis (OA) | Rheumatoid Arthritis (RA) |
|---|---|---|
| Primary Cause | Mechanical wear and tear / cartilage breakdown | Autoimmune attack on joint linings |
| Nature of Disease | Degenerative / Localized | Systemic / Inflammatory |
| Morning Stiffness | Brief (< 30 minutes) | Prolonged (> 1 hour) |
| Pain Response | Worse with activity, better with rest | Worse with rest, better with movement |
| Joint Symmetry | Often asymmetrical (one side or joint) | Highly symmetrical (mirror image on both sides) |
In the second part of this expert guide, we will dive deeper into the physical appearance of the joints, explore systemic red flags like fatigue and low-grade fevers, and detail the precise diagnostic blood panels and imaging tests doctors use to confirm whether your symptoms point to osteoarthritis or rheumatoid arthritis.
Osteoarthritis vs Rheumatoid Arthritis Differences
This video provides a concise visual overview contrasting the core mechanical and autoimmune differences between osteoarthritis and rheumatoid arthritis.
Navigating diagnostic tests and clinical evaluations
When physical symptoms overlap or present ambiguously, clinicians rely on a structured suite of diagnostic tools to differentiate between osteoarthritis (OA) and rheumatoid arthritis (RA). Because the underlying pathology of each condition is fundamentally different, mechanical degeneration versus systemic autoimmune attack, the diagnostic journey diverges significantly.
Blood markers and laboratory analysis
One of the most definitive ways a physician separates RA from OA is through blood work.
Rheumatoid Arthritis: Because RA is an autoimmune disorder, blood tests often reveal specific circulating antibodies and elevated inflammatory markers. Clinicians typically test for Rheumatoid Factor (RF) and anti-cyclic citrullinated peptide (anti-CCP) antibodies. The presence of anti-CCP is particularly specific to rheumatoid arthritis. Systemic inflammation is tracked using markers like C-reactive protein (CRP) and the erythrocyte sedimentation rate (ESR).
Osteoarthritis: There are no specific blood tests that can confirm osteoarthritis, as it is a mechanical and degenerative condition rather than an systemic inflammatory or autoimmune disease. Routine blood panels in OA patients typically return normal inflammatory markers unless a secondary condition is present.
Imaging techniques: What lies beneath the surface
Imaging provides a direct look at the structural state of the joint, revealing distinct signatures of wear versus immune-mediated destruction.
| Imaging Feature | Osteoarthritis (OA) | Rheumatoid Arthritis (RA) |
|---|---|---|
| Primary X-ray Findings | Asymmetrical joint-space narrowing, subchondral sclerosis (hardening of bone), and osteophytes (bone spurs). | Symmetrical joint-space narrowing and distinct bone erosions (marginal bone loss where the synovium attacks the bone). |
| Advanced Scans (Ultrasound/MRI) | Highlights localized cartilage thinning, meniscal changes, and minor fluid accumulation without aggressive synovial hypertrophy. | Detects early synovitis (inflammation of the joint lining), aggressive pannus formation, and active soft-tissue swelling before bone damage appears on standard X-rays. |
Treatment pathways and management goals
An accurate diagnosis is vital because treating the wrong condition can lead to accelerated joint damage and unnecessary discomfort. The therapeutic strategies reflect the root cause of the disease:
Targeting Osteoarthritis: Management focuses heavily on symptom relief, functional preservation, and mechanical support. Interventions include structured physical therapy to strengthen supporting muscles, weight management to reduce joint load, assistive devices, non-steroidal anti-inflammatory drugs (NSAIDs) for pain, and occasionally intra-articular corticosteroid injections.
Targeting Rheumatoid Arthritis: Treatment centers on halting the immune system's attack to induce remission and prevent systemic complications. This requires disease-modifying antirheumatic drugs (DMARDs), biologic agents, and targeted synthetic therapies designed to modulate or suppress specific pathways of the immune response.
Recognizing these nuances empowers individuals to partner effectively with rheumatologists and primary care providers, ensuring a tailored approach that addresses the precise origin of joint distress.
Rheumatoid Arthritis vs. Osteoarthritis
This video provides a clear visual breakdown comparing the mechanical nature of osteoarthritis with the inflammatory processes of rheumatoid arthritis.