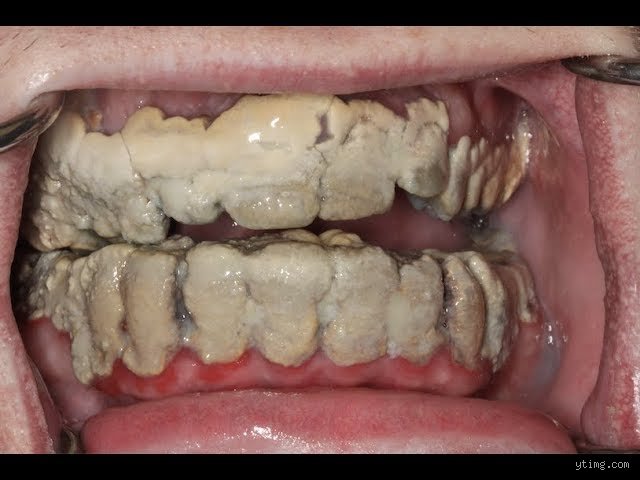
The human mouth is one of the most complex, densely populated microbial ecosystems in nature, acting as the primary gateway to both the digestive and respiratory tracts. When an individual permanently abandons the toothbrush, flossing, and all forms of oral maintenance, they initiate a predictable, cascading biological sequence.
To answer the provocative question—How long can a person live without brushing their teeth?, we must first dissect the precise timeline of oral degeneration, examining how localized bacterial proliferation eventually transforms into systemic pathology. This first part of our expert analysis explores the timeline from the first few hours of neglect to the multi-year establishment of advanced periodontal disease.
Phase 1: The first 24 to 72 hours, the birth of the biofilm
The moment an individual ceases brushing, the biological countdown begins. Within minutes of a person's last cleaning, a thin, protein-rich layer known as the acquired pellicle coats the enamel surfaces of the teeth. Derived primarily from saliva, this film acts as a sticky landing pad for wandering oral microorganisms.
Initial Colonization: Within hours, free-floating (planktonic) bacteria, predominantly harmless or commensal streptococci, begin to adhere to the pellicle.
Microbial Maturation: As these early colonizers multiply, they secrete extracellular polymers, creating a protective, adhesive matrix. This transforms a loose collection of bacteria into a structured, resilient community known as a dental plaque biofilm.
The Shift in Oxygen: By the end of the first 48 hours, the innermost layers of this thickening plaque become depleted of oxygen. This environmental shift allows anaerobic bacteria, species that thrive in oxygen-free environments, to proliferate rapidly.
During this initial window, the physical symptoms are subtle. The teeth may begin to feel "fuzzy" or rough to the tongue, and a mild, pasty film accumulates along the gumline. While no permanent damage has occurred yet, the foundational ecosystem for long-term decay has been successfully established.
Phase 2: One week to one month, acid attacks and early gingivitis
As days stretch into weeks without mechanical disruption via brushing or flossing, the plaque mass expands exponentially. The composition of the microbial community shifts dramatically, moving away from simple oral flora toward aggressive, acid-producing and inflammatory strains.
The Mechanism of Demineralization
Every time the host consumes carbohydrates, sugars, or starches, the bacteria residing within the plaque biofilm feast on these substrates. Through metabolic fermentation, they excrete organic acids, such as lactic, acetic, and formic acid.
Under normal conditions, daily brushing neutralizes these acids and sweeps away the substrate.
Without brushing, these acids remain trapped directly against the tooth enamel.
The localized pH drops below the critical threshold of approximately 5.5, causing calcium and phosphate ions to leach out of the hydroxycrystal structure of the enamel. This is the microscopic beginning of a dental caries (cavity) lesion.
The Onset of gingival Inflammation
Simultaneously, the sheer volume of bacterial byproducts and endotoxins begins to irritate the adjacent gum tissue (the gingiva). The body’s immune system recognizes this invasion and mounts an inflammatory response, rushing white blood cells to the gumline.
Clinically, this manifests as gingivitis.
Gums transition from a healthy, pale coral-pink to a dark, inflamed red or purple.
They become swollen, tender, and prone to spontaneous bleeding during eating or even light contact. Halitosis (chronic bad breath) also establishes itself firmly during this phase, driven by volatile sulfur compounds produced by anaerobic bacteria.
Phase 3: One month to one year, the mineralization of calculus
If plaque is allowed to accumulate unchecked past the one-month mark, a chemical transformation occurs that seals the individual's fate regarding home remedy solutions.
Saliva is naturally supersaturated with calcium and phosphate ions designed to remineralize teeth. However, when these minerals interact with the unremoved bacterial plaque biofilm, they precipitate and calcify the organic matrix. Within weeks, soft plaque hardens into a rock-hard, porous mineral deposit known as calculus (commonly referred to as tartar).
Subgingival Migration: Calculus does not merely form above the gumline (supragingival); it creeps below the margin into the delicate space between the tooth root and the gum tissue (subgingival calculus).
A Permanent Bacterial Reservoir: Because calculus is intensely porous and rough, it acts as an unyielding anchor for more bacteria. Crucially, calculus cannot be removed with a toothbrush or dental floss; it requires professional scaling instruments operated by a dental hygienist.
As calculus crowds the subgingival space, the gum tissue physically detaches from the tooth root, creating pathological spaces called periodontal pockets. The infection deepens, moving from the superficial gums into the deeper supporting structures of the jaw.
Phase 4: One to five years, the destruction of the periodontium
By the multi-year mark without oral hygiene, the localized disease process transitions into severe, chronic periodontitis. The ongoing warfare between the expanding subgingival bacterial flora and the body's chronic inflammatory immune response results in collateral tissue damage.
Alveolar Bone Loss: The body’s inflammatory cytokines (such as Interleukin-1 and Tumor Necrosis Factor-alpha) begin to stimulate osteoclasts, cells responsible for breaking down bone tissue. The jawbone supporting the teeth slowly dissolves away to distance itself from the chronic infection.
Tooth Mobility and Exfoliation: As the alveolar bone resorbs and the periodontal ligament fibers are destroyed, the teeth lose their structural foundation. They begin to loosen, shift positions, drift, and develop gaps. Eventually, multi-rooted teeth lose so much bone support that they become completely mobile and either fall out spontaneously or require extraction.
Widespread Decay: Concurrently, untreated cavities deep within the enamel breach the dentin layer and invade the dental pulp (the nerve and blood vessel center of the tooth). This leads to agonizing pulpitis, necrotic tissue death, and the formation of painful periapical abscesses, pockets of pus trapped at the apex of the tooth roots.
At this stage, the individual is not only experiencing severe chronic pain, profound functional masticatory impairment (inability to chew food properly), and aesthetic degradation, but they have also crossed a critical physiological threshold: the localized infection begins to breach systemic boundaries.
In the second part of this expert analysis, we will examine how advanced oral neglect crosses into the bloodstream, triggering systemic inflammatory diseases, cardiovascular complications, sepsis, and evaluating the ultimate question of overall life expectancy when oral hygiene is entirely abandoned.
The Mid-Term cascade: Months two through six
As the timeline extends past the initial months, the localized oral crisis begins to transition into a systemic threat. By the third to sixth month of complete neglect, the dynamic inside the oral cavity shifts from simple enamel decay to structural collapse.
Advanced Enamel Breakdown: The continuous acid bath produced by unchecked plaque successfully breaches the hard outer layer of the tooth, exposing the much softer dentin underneath. Cavities expand rapidly once they reach this layer, often merging to compromise entire tooth crowns.
The Onset of Periodontitis: Gingivitis, if left unmanaged, matures into full-scale periodontitis. The chronic inflammatory response causes the body's immune system to begin breaking down the connective tissue and alveolar bone supporting the teeth. Gums recede visibly, exposing sensitive root surfaces and creating deep periodontal pockets packed with anaerobic bacteria.
Persistent Infection and Abscess Formation: Bacteria eventually infiltrate the dental pulp, the living core of the tooth housing nerves and blood vessels. When the pulp dies, an infection can travel down the root tip, forming painful pus-filled abscesses in the jawbone.
Long-Term Systemic consequences: One year and beyond
When hygiene is abandoned for a year or longer, the human body suffers consequences that stretch far beyond a painful smile. While a person may technically "survive" for many years without brushing, since poor dental hygiene is rarely an immediate cause of mortality on its own, the chronic burden placed on the body is immense.
+-------------------------------------------------------------+
| SYSTEMIC PATHWAYS OF ORAL NEGLECT |
+-------------------------------------------------------------+
| Chronic Periodontal Inflammation |
| │ |
| ▼ |
| Bacterial Toxins Enter Bloodstream (Bacteremia) |
| │ |
| ├───────────────────┬───────────────────┐ |
| ▼ ▼ ▼ |
| Cardiovascular Systemic Immune Metabolic |
| Strain / Plaque Activation & Disruption |
| Aggravation Inflammation (Diabetes Complications)
+-------------------------------------------------------------+
1. Cardiovascular Complications
The blood vessels in inflamed, bleeding gums provide a direct superhighway for oral bacteria and inflammatory byproducts to enter the bloodstream (a condition known as transient bacteremia). Once circulating, these pathogens can contribute to the formation of arterial plaques, elevating the long-term risk of heart attacks and strokes.
2. Metabolic and Immune Strain
A body fighting chronic, low-grade oral infections experiences a persistently elevated inflammatory state. For individuals managing conditions like diabetes, this constant immune activation makes blood sugar regulation significantly more difficult, worsening overall systemic health.
3. Nutritional decline and social isolation
As teeth loosen, fracture, or fall out entirely, the ability to chew nutrient-dense foods, such as fresh vegetables, lean proteins, and complex carbohydrates, disappears. Diets shift toward soft, highly processed, sugary alternatives, compounding both metabolic decline and localized tooth decay. The combination of chronic halitosis, facial structure changes from bone loss, and visible tooth degradation frequently leads to profound social withdrawal and psychological distress.
The resilience of the human body versus daily care
While the human body is remarkably resilient and can endure years of severe dental neglect without immediate fatal outcomes, the quality of life degrades drastically. Brushing twice a day and flossing daily are not merely cosmetic routines; they are essential biological defenses that protect the gateway to the rest of the body, ensuring that minor bacterial accumulations never escalate into systemic health crises.