The short answer is yes—as neurodegenerative conditions progress, individuals frequently spend significantly more time sleeping, both during the day and night. However, this phenomenon is rarely straightforward. Increased sleep is not merely a sign of simple physical tiredness; it is the physical manifestation of complex neuropathological damage, disruption of the brain’s internal master clock, secondary medication side effects, and metabolic fatigue.
This comprehensive analysis explores the neurobiology behind why individuals with dementia sleep more, how sleep architecture changes across different stages of the disease, and what caregivers must evaluate when hypersomnia (excessive sleeping) occurs.
1. The neurological foundation: Why dementia alters Sleep architecture
To understand why individuals with dementia sleep a lot, we must first look inside the brain. The human sleep-wake cycle is governed by intricate neural networks involving the hypothalamus, the brainstem, and various neurotransmitter systems that regulate alertness and sleep.
As neurodegenerative diseases—such as Alzheimer’s disease, vascular dementia, and dementia with Lewy bodies (DLB), advance, they cause widespread structural and functional damage.
Suprachiasmatic Nucleus (SCN) Degradation: The SCN, located in the hypothalamus, acts as the body's master biological clock. In many forms of dementia, protein aggregations (such as amyloid-beta plaques and tau tangles in Alzheimer's) damage the SCN. This degradation blurs the distinction between day and night, leading to a fragmented circadian rhythm where the brain loses its ability to sustain consolidated blocks of wakefulness.
Loss of Wake-Promoting Neurons: Neurodegeneration often targets brain regions responsible for producing neurotransmitters that keep us alert, such as acetylcholine, orexin/hypocretin, and norepinephrine. When these wake-promoting centers deteriorate, the brain defaults to a state of chronic fatigue and increased sleep propensity.
Altered Sleep Stages: Polysomnography studies show that dementia patients spend drastically less time in restorative slow-wave sleep (deep sleep) and rapid eye movement (REM) sleep. Because their nighttime sleep is shallow, fragmented, and inefficient, they wake up unrefreshed, triggering an intense biological need for compensatory sleep (napping) during daylight hours.
2. Stage-by-Stage breakdown of Sleep changes
Sleep alterations are not uniform throughout the entire course of dementia. They evolve dynamically as brain tissue degeneration spreads:
Early Stages: Insomnia, restlessness, and subtle Shifts
In the early stages of cognitive decline, excessive daytime sleepiness is less common than fragmentation and insomnia. Patients frequently experience difficulties falling asleep, frequent nocturnal awakenings, and heightened anxiety. Paradoxically, while they may struggle with nighttime rest, they might begin taking short, unintentional naps during the day as their brains work harder to process everyday cognitive tasks.
Middle Stages: The emergence of Day-Night reversal
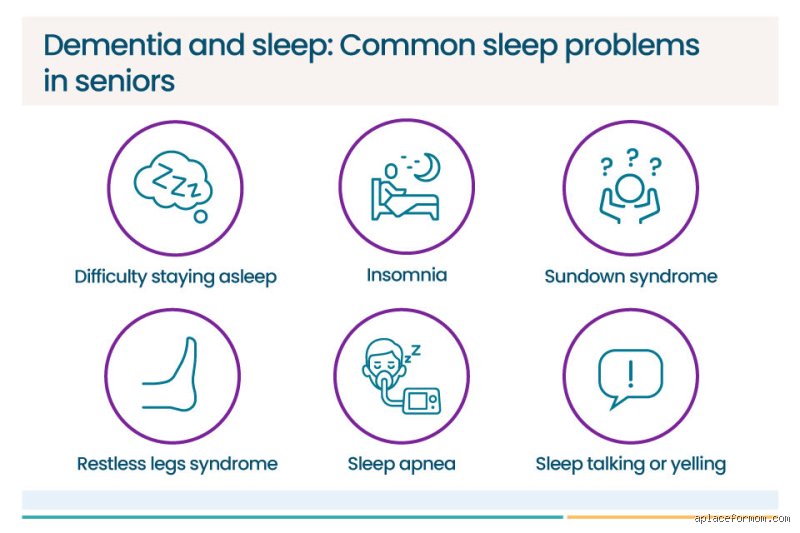
As the disease progresses into the middle stages, hypersomnolence (excessive daytime sleepiness) becomes much more pronounced. This phase is frequently characterized by circadian confusion or a total sleep pattern reversal. Patients may doze extensively in an armchair throughout the afternoon, only to become completely awake, restless, and disoriented during the middle of the night. This phase often features "sundowning", a late-afternoon surge of confusion, agitation, and fatigue that further scrambles normal sleep hygiene.
Late Stages: Profound hypersomnia and frailty
In advanced or late-stage dementia, individuals often spend the vast majority of their time, frequently 14 to 16 hours a day or more, sleeping. This heavy, continuous sleeping is driven by extensive, irreversible damage across broad networks of the cerebral cortex and subcortical structures. At this juncture, simple everyday actions, such as processing conversation, chewing, swallowing, or orienting to an environment, require an immense cognitive and physical expenditure. The brain and body become fundamentally exhausted, resulting in prolonged periods of unresponsiveness and deep sleep as the body grows progressively frailer.
3. Beyond pathology: Secondary contributors to excessive Sleep
While neurodegeneration is the primary driver of increased sleep in dementia, clinical evaluations must rule out secondary, often treatable, contributors that exacerbate lethargy:
Medication Side Effects: Many individuals with dementia take a complex regimen of pharmaceuticals. Drugs such as antipsychotics, sedatives, certain antidepressants, antihistamines, and anti-anxiety medications list central nervous system depression and profound daytime drowsiness as prominent side effects.
Sleep-Disordered Breathing: Conditions like obstructive sleep apnea (OSA) are highly prevalent in older adults. Interrupted breathing causes micro-awakenings throughout the night, destroying sleep quality and resulting in severe excessive daytime sleepiness.
Medical Complications and Delirium: A sudden or dramatic increase in sleeping, as opposed to a gradual progression, is often a red flag. It can signal an underlying acute medical issue, such as a urinary tract infection (UTI), pneumonia, dehydration, chronic pain, electrolyte imbalances, or the onset of delirium.
Psychological Factors: Depression in older adults can manifest not only through sadness or withdrawal, but also through profound psychomotor retardation, fatigue, and an increased desire to stay in bed and sleep.
Navigating the later Stages: Increased hypersomnia and neurological decline
As neurodegenerative conditions progress into their advanced stages, the clinical presentation frequently shifts from fragmented nighttime sleep and erratic daytime napping to a profound, overarching increase in total sleep time. This transition toward hypersomnia is not merely a behavioral quirk; it reflects the compounding structural damage occurring deep within the subcortical and cortical networks of the brain.
In late-stage dementia, the widespread loss of neurons and synapses compromises the brain’s core energy reserves. Simple everyday tasks, such as processing sensory input, communicating basic needs, navigating a room, or chewing and swallowing food, demand an exhausting level of cognitive and physiological effort. Consequently, the physical and mental fatigue experienced by individuals is immense, manifesting as prolonged periods of slumber both day and night.
Structural deterioration within the ascending reticular activating system (ARAS), the network responsible for maintaining wakefulness and arousal, directly impairs the brain's capacity to sustain a alert state. When these regulatory centers atrophy, the default state of the organism leans heavily toward conservation and rest.
Secondary contributors to excessive Sleep
While organic brain damage remains the primary driver of altered sleep architecture in advanced cognitive decline, clinical management must also account for secondary, compounding variables that exacerbate drowsiness:
Pharmacological Side Effects: Individuals with dementia often manage multiple comorbidities. Prescriptions such as antipsychotics, anxiolytics, sedating antidepressants, and certain analgesics can significantly increase daytime sedation.
Co-morbid Sleep Disorders: Conditions like obstructive sleep apnea (OSA), which features recurrent upper airway collapse during sleep, lead to severe nocturnal hypoxia and sleep fragmentation. This lack of restorative rest forces the body to compensate through heavy daytime sleeping.
Metabolic and Systemic Shifts: Chronic low-grade infections (such as urinary tract infections), subclinical pain, nutritional deficits, and hepatic or renal inefficiencies frequently present in older adults as lethargy and increased sleep duration.
Comprehensive care strategies and environmental optimization
Managing sleep alterations in individuals with cognitive impairment requires a delicate balance between respecting the body's increased need for rest and preventing total circadian inversion (where the person sleeps all day and stays awake all night). Caregivers and clinical teams can implement structured, non-pharmacological interventions to support healthy rest-activity rhythms:
Enhancing Daytime Light Exposure: Maximizing exposure to bright natural daylight, especially during morning hours, helps anchor the biological clock, stimulating endogenous melatonin production when evening approaches.
Structured Physical and Social Engagement: Incorporating gentle, personalized activities, short walks, or sensory stimulation throughout the day prevents prolonged daytime inertia and promotes a healthier sleep debt by nighttime.
Managing the Sleep Environment: Keeping bedroom spaces quiet, comfortably cool, and dimly lit at night minimizes sensory confusion, reducing nocturnal wandering and agitation.
Evaluating Medication Regimens: Regular reviews with healthcare providers to assess whether current medications are unnecessarily compounding daytime drowsiness can help optimize alertness levels.
Understanding why individuals with dementia sleep extensively requires looking beyond the surface symptom. It involves viewing sleep disturbances through the lens of progressive neurodegeneration, recognizing that excessive rest is often the brain's physiological response to profound exhaustion and structural reorganization.