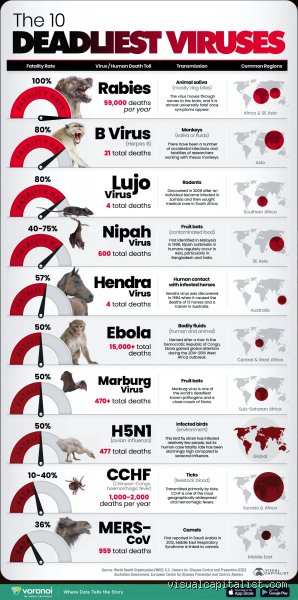
To properly investigate this medical frontier, one must separate total case fatality rate (CFR) from kinetic speed. Several chronic or subacute conditions possess a 100% mortality rate over time, but true "lightning killers" operate on scales measured not in months or weeks, but in hours or days. This first installment of our expert analysis explores the pathological mechanisms, historical contexts, and biological terror of the world's most rapidly fatal medical conditions.
Defining "Speed" in Disease progression
In clinical pathology, speed is categorized through two distinct temporal lenses: incubation velocity and clinical trajectory speed.
Incubation Velocity: The duration between pathogen entry and the manifestation of initial symptoms. Some agents remain silent for weeks before abruptly seizing control of the host.
Clinical Trajectory Speed: The window from the very first overt symptom (such as a headache, fever, or rash) to irreversible organ failure or death.
The most terrifying agents combine short incubation periods with explosive clinical trajectories, leaving a narrow or nonexistent window for medical intervention. When an infectious agent or acute clinical syndrome bypasses the adaptive immune system's capacity to mount a defense, the human body transitions from homeostasis to catastrophic failure with terrifying swiftness.
1. Rabies: The 100% inevitable neurotropic nightmare
While rabies virus infection is preventable through prompt post-exposure prophylaxis (PEP), once clinical symptoms manifest, it stands as one of the most uniformly fatal and psychologically harrowing conditions known to human medicine. Caused by a neurotropic lyssavirus transmitted primarily through the saliva of infected mammals (most commonly via bites or scratches), rabies initiates a stealthy ascent up the peripheral nervous system toward the central nervous system.
Pathological Mechanism and Timeline
The incubation period of rabies is notoriously variable, ranging from weeks to months depending on the site of the bite (bites closer to the head and neck accelerate the timeline). However, once the virus reaches the brain and clinical signs—such as encephalopathy, hydrophobia, agitation, and autonomic instability, appear, the biological trajectory is almost exclusively fatal.
The virus induces severe inflammation of the brain while actively evading major immune detection during its neural transit. Death typically occurs via respiratory arrest or generalized cardiovascular collapse within days of symptom onset. With fewer than a handful of documented historical survivors who received experimental treatments (such as the Milwaukee protocol, though its efficacy remains heavily debated and difficult to replicate), rabies represents a terrifying benchmark of absolute neurological fatality.
2. Peracute Bacterial meningitis: Death in a matter of Hours
Among bacterial infections, few match the breathtaking speed of peracute bacterial meningitis, particularly strains driven by Neisseria meningitidis (meningococcus). When these Gram-negative diplococci colonize the nasopharynx and breach the bloodstream, they can trigger a fulminant systemic cascade known as meningococcemia.
The Mechanism of rapid collapse
The danger of meningococcal disease lies not merely in the inflammation of the meninges (the protective membranes surrounding the brain and spinal cord), but in the massive release of endotoxins into the vascular system. This triggers disseminated intravascular coagulation (DIC) and septic shock, frequently culminating in Waterhouse-Friderichsen syndrome, characterized by catastrophic bilateral hemorrhage of the adrenal glands.
Timeline: Healthy individuals can transition from feeling mildly unwell with flu-like aches to experiencing purpuric rashes, delirium, profound hypotension, and death in under 24 hours.
Clinical Challenge: Because early symptoms mimic a common viral upper respiratory infection, patients or primary caregivers often delay seeking emergency care until the tipping point has passed, making peracute bacterial meningitis one of the most feared acute emergencies in emergency medicine.
3. Primary Amoebic Meningoencephalitis (PAM): The Brain-Eating invader
Caused by Naegleria fowleri, a thermophilic, free-living amoeba found in warm freshwater bodies such as lakes, hot springs, and poorly maintained swimming pools, primary amoebic meningoencephalitis is an exceptionally rare yet astonishingly swift aquatic infection.
Invasion and Destruction
Infection occurs when water containing the amoeba is forced up the nasal passages, typically during swimming or diving. Naegleria fowleri breaches the cribriform plate, migrating directly along the olfactory nerve fibers into the anterior cranial fossa. Once inside the brain parenchyma, the amoeba aggressively feeds on neural tissue, releasing cytolytic enzymes that rapidly destroy brain cells.
Progression: Initial symptoms, including frontal headache, fever, nausea, and altered smell or taste, begin within 1 to 9 days of exposure.
The Fatal Drop: Within days of these initial symptoms, the infection escalates rapidly into stiff neck, seizures, altered mental status, hallucinations, and coma. The case fatality rate exceeds 98%, with death usually occurring due to raised intracranial pressure and herniation within 3 to 7 days of symptom onset.
Comparative overview of rapidly Fatal pathogens
| Disease Agent / Condition | Primary Transmission Vector | Average Time from Symptom Onset to Critical Phase | Approximate Untreated Case Fatality Rate |
|---|---|---|---|
| Rabies (Encephalitic Phase) | Animal Saliva (Bites/Scratches) | Days to 1 Week | >99% |
| Meningococcal Septicemia | Respiratory Droplets | 6 to 24 Hours | 50% to 100% (if untreated) |
| Primary Amoebic Meningoencephalitis | Contaminated Warm Water (Nasally) | 3 to 7 Days | >98% |
| Pneumonic Plague | Airborne Droplets / Respiratory | 24 to 72 Hours | ~100% |
The role of host immune overreaction
A critical insight uncovered by modern immunology is that the absolute speed of a killing disease is often driven not solely by the direct destruction wreaked by the pathogen, but by the host's hyper-inflammatory response.
When pathogens like filoviruses (Ebola, Marburg), virulent bacterial strains, or acute neurotropic viruses breach host barriers, they can trigger a "cytokine storm." This systemic overproduction of immune signaling proteins causes widespread vascular leakage, multi-organ failure, and clotting abnormalities. Paradoxically, a robust immune system can sometimes accelerate mortality if its signaling pathways are hijacked into a runaway feedback loop of tissue destruction.
Looking ahead: Part II preview
While neurological and bacterial infections claim lives in hours or days, systemic viral hemorrhagic fevers and hyper-virulent respiratory pathogens operate on alternative epidemiological vectors, combining high contagiousness with swift structural damage. In the upcoming second part of this analysis, we will examine filoviral dynamics, systemic shock syndromes, and the modern medical interventions designed to interrupt these lightning-fast pathological cascades before they cross the threshold of no return.
When examining medical literature to identify the absolute "fastest killing disease," epidemiologists and infectious disease specialists generally divide the question into two distinct categories: time from initial symptom onset to death (acuity) and case fatality rate without medical intervention (virulence).
While chronic conditions like tuberculosis or lifestyle-related illnesses claim millions of lives over months or years, a select group of acute pathogens and neurodegenerative anomalies can dismantle human physiological systems in a matter of hours or days.
The spectrum of rapid lethality
To understand how rapidly a disease can kill, we must look at the mechanisms by which pathogens overwhelm human defenses. The fastest-killing conditions typically fall into three distinct classifications:
Peracute Bacterial Toxemias: Diseases where the bacteria itself multiplies rapidly, but the true lethality stems from potent exotoxins or endotoxins that trigger catastrophic systemic responses, such as vascular collapse and disseminated intravascular coagulation (DIC).
Fulminant Viral Hemorrhagic Fevers and Encephalitides: Viral infections that evade the early immune response, target vital organs (such as the liver, kidneys, or central nervous system), and cause massive tissue destruction or brain inflammation.
Incurable Prion Diseases: Degenerative neurological conditions that, while possessing a longer incubation period, carry a virtually 100% mortality rate once clinical symptoms manifest, with progressive deterioration leading to death.
Key contenders for Speed and lethality
1. Pneumonic Plague (Yersinia pestis)
While bubonic plague is famous for its slow lymph node invasion, the pneumonic form of the plague is among the most rapidly lethal bacterial infections known to humanity.
The Mechanism: When transmitted via respiratory droplets, Yersinia pestis attacks the lungs directly, causing severe pneumonia, rapid respiratory failure, and systemic sepsis.
The Timeline: If left untreated, pneumonic plague has a case fatality rate approaching 100%, often causing death within 24 to 72 hours of initial symptom onset.
2. Rabies Encephalitis
Rabies is unique because of its exceptionally long and variable incubation period (ranging from weeks to months), but once clinical neurological symptoms appear, it is virtually a death sentence.
The Mechanism: The rabies virus travels along peripheral nerves toward the central nervous system, causing profound inflammation of the brain (acute encephalitis).
The Timeline: Once symptoms such as hydrophobia, confusion, and paralysis manifest, death typically follows within days to a week due to respiratory or cardiac arrest. Fewer than a handful of individuals have ever survived symptomatic rabies without immediate, pre-symptom post-exposure prophylaxis.
3. Neisseria meningitidis (Meningococcal Septicemia)
Meningococcal disease can turn from mild flu-like symptoms into a life-threatening crisis faster than almost any other common bacterial infection.
The Mechanism: When the bacteria enter the bloodstream (meningococcemia), they release endotoxins that cause blood vessels to leak throughout the body, leading to massive blood pressure drops, multi-organ failure, and rapid tissue necrosis.
The Timeline: Patients can transition from feeling unwell to entering profound shock and dying within hours of the first visible symptoms, such as a purpuric rash.
4. Filoviruses (Ebola and Marburg)
Though often associated with a multi-day progression of weakness, fever, and gastrointestinal distress, the most aggressive strains of Ebola and Marburg viruses can overwhelm the host via fulminant shock.
The Mechanism: These filoviruses trigger an overwhelming immune response (cytokine storm) coupled with widespread damage to endothelial cells lining blood vessels, leading to unmanageable fluid loss, shock, and organ failure.
The Timeline: In severe, untreated cases, the downward spiral from initial high fever to terminal shock can occur in under a week.
The role of modern medicine
The terrifying timelines associated with these diseases largely describe their behavior in unvaccinated and untreated populations. Modern intensive care units, broad-spectrum antibiotics, fluid resuscitation, and targeted antiviral monoclonal antibodies have transformed what were once rapid executioners into survivable, albeit severe, medical emergencies.
While rabies and untreated pneumonic plague contend for the title of absolute speed combined with a 100% mortality rate, the razor-thin margin between symptom onset and fatality in meningococcal septicemia makes it one of the most frighteningly fast killers in modern clinical practice.