Unraveling the silent epidemic: Cardiovascular Disease and Global Mortality
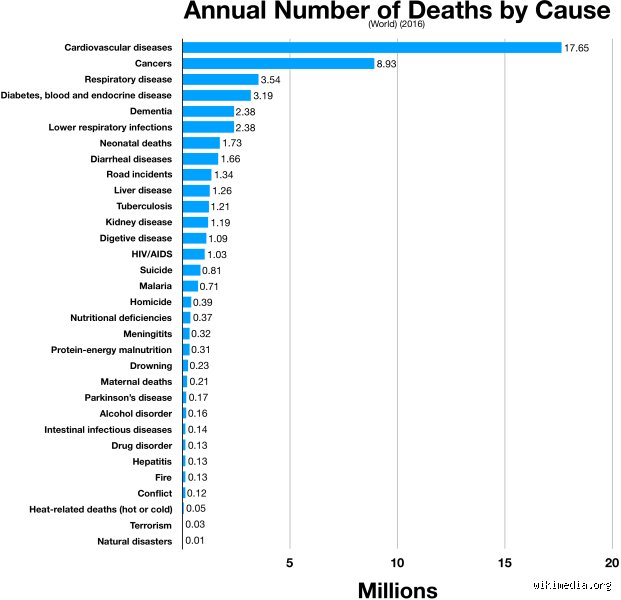
When examining global mortality statistics provided by institutions like the World Health Organization (WHO), a clear and striking reality emerges: the highest killing disease in the world is not a sudden, terrifying viral pandemic or an exotic tropical pathogen. Instead, the undisputed leader in global fatalities is ischaemic heart disease (also known as coronary artery disease), closely followed by stroke. Together, cardiovascular diseases (CVDs) account for roughly 16% to over 30% of all global deaths annually, cementing their status as the world's most formidable public health crisis.
Understanding why these conditions claim millions of lives each year requires an in-depth look at their pathology, risk factors, and the socioeconomic shifts driving their prevalence across different populations.
The pathophysiology of Ischaemic heart Disease
To grasp why ischaemic heart disease is the world’s leading killer, one must understand how it develops inside the human body. The disease is characterized by atherosclerosis—the narrowing and hardening of the coronary arteries due to the buildup of fatty plaques composed of cholesterol, calcium, and cellular waste products.
As these plaques accumulate over decades, they gradually restrict blood flow to the heart muscle (myocardium). When the heart is starved of oxygen-rich blood, individuals may experience angina (chest pain). More critically, if a plaque ruptures, it can trigger a blood clot that completely blocks the artery, leading to a myocardial infarction (heart attack). If oxygen deprivation persists, heart tissue begins to die, which can result in fatal arrhythmias, heart failure, or sudden cardiac arrest.
Why stroke follows closely behind
Operating on a similar vascular mechanism, cerebrovascular disease—commonly known as stroke, ranks second among non-communicable global killers. While a heart attack cuts off blood supply to the heart, a stroke disrupts blood flow to regions of the brain. This occurs either via an ischemic block (a blood clot in a cerebral artery) or a hemorrhagic event (a ruptured blood vessel in the brain). Because brain cells are exceptionally sensitive to oxygen deprivation, cellular death begins within minutes, resulting in long-term neurological deficits or death.
Shifting paradigms: Communicable vs. Non-Communicable diseases
Historically, humanity’s greatest demographic threats came from infectious or communicable diseases, such as plague, cholera, smallpox, and influenza. However, over the past century, advancements in public health, sanitation, antibiotics, and widespread vaccination programs have drastically reshaped global mortality.
Today, non-communicable diseases (NCDs) dominate the leading causes of death worldwide. This epidemiological transition represents a double-edged sword: as global life expectancies increase and absolute poverty rates decline in many regions, more people are surviving infectious diseases in youth, only to live long enough to develop chronic, age-related conditions like heart disease, cancer, and neurodegenerative disorders.
| Disease Category | Primary Examples | Global Mortality Share / Impact |
|---|---|---|
| Non-Communicable (NCDs) | Ischaemic heart disease, stroke, Alzheimer's | Responsible for the vast majority of global deaths (approx. 74-88% of top causes) |
| Communicable / Infectious | Lower respiratory infections, tuberculosis, HIV/AIDS | Highly prevalent in low-income regions; declining overall due to modern medicine |
| Injuries | Road traffic accidents, trauma | Significant contributor to mortality among younger demographics |
Global disparities and risk factors
The burden of ischaemic heart disease is not distributed uniformly across the globe. While mortality rates from cardiovascular diseases have plateaued or declined in many high-income countries due to aggressive preventative care, advanced surgical interventions, and public health education, they are surging in low- and middle-income nations.
This shift is heavily tied to the "Westernization" of lifestyle habits, including:
Dietary Changes: Increased consumption of ultra-processed foods, refined sugars, sodium, and unhealthy trans-fats.
Sedentary Lifestyles: Urbanization and desk-bound occupations drastically reducing daily physical activity.
Tobacco Use: Smoking remains one of the single most potent catalysts for endothelial damage and arterial plaque buildup.
Metabolic Syndrome: The rising global prevalence of obesity, type 2 diabetes, and hypertension, all of which heavily exacerbate cardiovascular strain.
Prevention, public Policy, and the path forward
Because ischaemic heart disease is largely chronic and behavioral, the key to reducing its global footprint lies in proactive prevention and systemic healthcare reform. Public health initiatives focus heavily on early screening for high blood pressure and hypercholesterolemia, as these conditions act as silent precursors to major cardiac events.
Interventions operate on multiple levels:
Individual Lifestyle Modifications: Adopting a Mediterranean-style diet rich in whole grains, omega-3 fatty acids, and leafy greens; engaging in regular aerobic exercise; maintaining a moderate weight; and completely eliminating tobacco use.
Medical Management: Utilizing medications such as statins to lower cholesterol, antihypertensives to control blood pressure, and antiplatelet drugs (like low-dose aspirin) to prevent clot formation in high-risk patients.
Macro-Level Policy: Implementing sugar taxes, restricting trans-fats in commercial manufacturing, mandating clear nutritional labeling, and launching nationwide anti-smoking campaigns.
Conclusion
In summary, while terrifying viral outbreaks capture headlines, the true apex predator of global health is the slow, cumulative progression of cardiovascular disease. Ischaemic heart disease stands alone as the world’s leading killer, driven by a complex mix of aging populations, lifestyle evolutions, and systemic socioeconomic factors. Mitigating this crisis requires a coordinated global shift toward preventative medicine, healthy living environments, and equitable access to cardiovascular care, ensuring that humanity’s increasing longevity is matched by sustained quality of life.