Unmasking the silent threat: The insidious dangers of high cholesterol
To understand the gravity of high cholesterol, one must first look beyond the numbers on a routine lab printout and examine the intricate mechanics of human vascular biology. Cholesterol is not inherently evil; in fact, it is a vital, fat-like substance (lipid) that your body requires to build healthy cell walls, produce essential hormones, and synthesize vitamin D. The liver manufactures more than enough cholesterol for these baseline physiological needs. However, modern dietary patterns, genetic predispositions, metabolic shifts, and sedentary lifestyles frequently push circulating lipid levels far past the body's capacity to manage them safely.
When excess low-density lipoprotein (LDL), commonly labeled "bad" cholesterol, circulates in the bloodstream in high concentrations, a dangerous pathological cascade begins. Unlike a plumbing pipe that remains smooth and unchanging, the inner lining of your blood vessels (the endothelium) is a dynamic, highly sensitive tissue. Chronic exposure to high LDL levels damages this delicate endothelial lining, creating microscopic breaches. Once the barrier is compromised, LDL particles slip beneath the surface into the arterial wall, where they become trapped and undergo oxidation.
This oxidation triggers a localized immune response, dispatching white blood cells called macrophages to engulf the modified cholesterol. Overwhelmed by the sheer volume of fat, these cells transform into lipid-laden foam cells. As these foam cells accumulate, they form fatty streaks, which eventually mature into complex, rigid structures known as atherosclerotic plaques. This foundational process, atherosclerosis, marks the true beginning of the dangers associated with high cholesterol.
The Cascade of Vascular degradation: Beyond the numbers
The accumulation of plaque does not happen uniformly; it is a progressive disease of the arterial tree that fundamentally alters the physical properties of the cardiovascular system. Healthy arteries are elastic, flexible conduits that expand and contract smoothly with every heartbeat, dampening pressure waves and ensuring seamless blood delivery to every organ. As cholesterol plaque builds up, it co-opts this elasticity, replacing flexible tissue with calcified, fibrous scar material.
This hardening of the arteries creates a multi-pronged systemic threat:
Progressive Arterial Stenosis: As plaques expand inward, they physically narrow the lumen (the internal channel) of the blood vessels. This restriction throttles the volume of blood that can pass through, starving downstream tissues of the oxygen and vital nutrients they require to function under stress.
Systemic Pressure Elevation: Because the plumbing network has become rigid and narrow, the heart must generate significantly higher pumping pressures to force blood through the resistance. This synergy between high cholesterol and secondary hypertension creates a destructive feedback loop, wherein high pressure further damages endothelial cells, accelerating even more plaque deposition.
Vascular Vulnerability and Inflammation: Plaques are not inert mineral deposits; they are active, inflamed lesions. Unstable plaques develop a thin, fragile fibrous cap over a soft core of cellular debris, cholesterol crystals, and inflammatory chemicals. If this cap fractures, it exposes the thrombogenic (clot-promoting) interior directly to the rushing blood stream, setting the stage for catastrophic acute events.
Understanding this progression shifts our perspective from viewing high cholesterol as a mere biochemical anomaly to recognizing it as an aggressive, systemic restructuring of the body's vital transit lines. The downstream consequences of this structural failure manifest in some of the most lethal and debilitating medical emergencies known to modern medicine, affecting the heart, brain, and peripheral limbs with equal ferocity.
The primary arenas of damage: Heart, brain, and limbs
Because the cardiovascular network supplies every square inch of the body, the dangers of high cholesterol are broad, but they concentrate heavily on organs with high metabolic demands and delicate microvasculature.
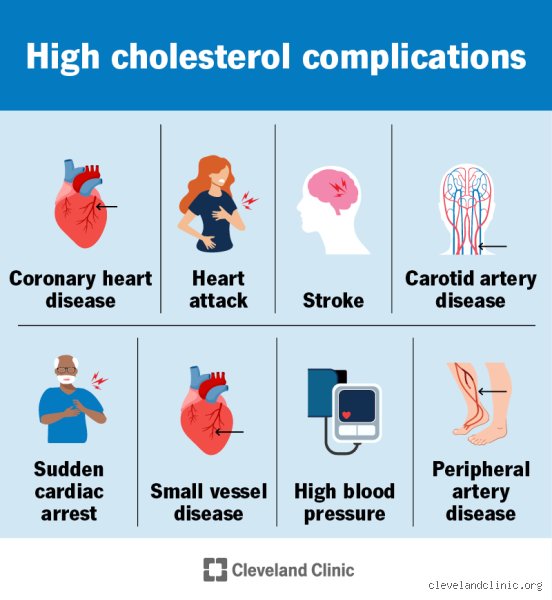
When coronary arteries, the dedicated lifeline supplying the heart muscle itself, become choked with cholesterol plaque, the patient enters the shadow of Coronary Artery Disease (CAD). Initially, this may manifest only during exertion as angina pectoris (chest discomfort, tightness, or shortness of breath) because the narrowed arteries cannot supply enough blood to meet the heart's increased oxygen demand during exercise. However, the true peril lies in total occlusion. If a plaque ruptures, a massive blood clot (thrombus) can form instantly over the site, cutting off blood flow to a region of the myocardium. The result is a myocardial infarction, commonly known as a heart attack, where heart muscle tissue begins to die within minutes.
Simultaneously, the cerebral circulation is at high risk. The carotid and cerebral arteries feeding the brain can undergo the exact same atherosclerotic narrowing. If a plaque ruptures and clots locally, or if a piece of debris breaks loose (an embolus) and travels upward to lodge in a tighter brain vessel, an ischemic stroke occurs. Brain cells deprived of oxygen undergo rapid necrosis, potentially leading to permanent neurological deficits, paralysis, loss of speech, or death.
Beyond the core organs of the upper body, high cholesterol aggressively targets the extremities through Peripheral Artery Disease (PAD). Plaque buildup in the arteries of the legs and pelvis restricts blood flow to the lower limbs. Sufferers often experience painful cramping, heaviness, fatigue, or aching in their calves, thighs, or buttocks during walking, a symptom known as intermittent claudication. In severe, advanced cases, the tissue starvation becomes so acute that non-healing ulcers, infections, and gangrene can develop, frequently culminating in critical limb ischemia and amputation.
Genetic vulnerabilities and silent accelerators
While lifestyle factors such as a high-saturated-fat diet, physical inactivity, and smoking play a massive role in shaping lipid profiles, it is a dangerous misconception to assume high cholesterol only affects those with poor habits. Millions of people grapple with hereditary conditions that drive cholesterol to dangerous heights regardless of how cleanly they eat or how many hours they spend at the gym.
The most prominent of these genetic anomalies is Familial Hypercholesterolemia (FH), a dominant inherited disorder caused by mutations in genes (most notably the LDL receptor gene) responsible for clearing LDL cholesterol from the bloodstream. Individuals born with FH have severely impaired liver clearance mechanisms, resulting in astronomical LDL-C levels from birth. Without early diagnosis and aggressive medical intervention, individuals with homozygous or heterozygous FH can suffer heart attacks, strokes, or sudden cardiac death at remarkably young ages, sometimes even in their twenties or thirties.
High cholesterol rarely acts in a vacuum. Its dangers multiply exponentially when it coexists with other metabolic disruptors:
Type 2 Diabetes Mellitus: Diabetes alters lipid metabolism, driving up triglycerides and small, dense LDL particles while suppressing protective HDL cholesterol. Simultaneously, high blood sugar glycates and damages blood vessel walls, making them exceptionally receptive to plaque formation.
Systemic Inflammation: Elevated inflammatory markers, such as high-sensitivity C-reactive protein (hs-CRP), act like an accelerant on cholesterol deposits, transforming stable plaques into unstable, rupture-prone hazards.
Chronic Kidney Disease: Impaired renal function alters systemic electrolyte and lipid handling, sharply multiplying overall cardiovascular vulnerability.
Recognizing these compounding factors emphasizes why managing cholesterol is never a one-dimensional pursuit. It requires a comprehensive, highly individualized medical strategy designed to evaluate cumulative lifetime risk rather than chasing a single isolated lab value.
Defining atherosclerotic cardiovascular disease (ASCVD)
This video is relevant because it breaks down the specific vascular mechanisms, artery occlusion patterns, and physiological risks associated with plaque buildup caused by elevated lipid levels.
Beyond the silent Build-Up: The Severe consequences of unchecked high cholesterol
While the initial accumulation of low-density lipoprotein (LDL) cholesterol inside your blood vessels begins silently, often without a single warning sign or symptom for decades, the long-term physiological toll can be catastrophic. Understanding why elevated cholesterol is frequently referred to as a "silent danger" requires looking past the routine lab report and examining how chronic hypercholesterolemia systematically degrades the cardiovascular, cerebrovascular, and peripheral vascular systems.
1. Coronary Artery Disease and myocardial infarction
The most direct and well-documented consequence of high cholesterol is atherosclerosis, or the hardening and narrowing of the arteries.
The Pathological Cascade: When excess LDL particles infiltrate the innermost lining of the arterial walls (the endothelium), they become oxidized. This triggers an immune response, drawing white blood cells called macrophages to engulf the cholesterol, transforming them into foam cells. Over time, these cells accumulate into a fatty streak, eventually forming a hard, fibrous plaque.
Ischemia and Chest Pain: As these plaques expand, they restrict the lumen (the interior space) of the coronary arteries that feed the heart muscle. When physical exertion or stress increases the heart's demand for oxygen-rich blood, the narrowed arteries cannot keep up, resulting in chest pain or tightness known as angina.
The Acute Trigger (Heart Attack): The greatest danger is not always a slow, steady blockage, but rather plaque instability. Vulnerable plaques have thin caps that can rupture unexpectedly. When a plaque ruptures, the body attempts emergency repair by forming a sudden blood clot. If this clot completely occludes the coronary artery, a portion of the heart muscle is instantly starved of oxygen and begins to die, triggering a myocardial infarction (heart attack).
2. Cerebrovascular accidents (ischemic Strokes)
The destructive path of plaque buildup is not limited to the heart; it poses an equally grave threat to the brain.
Carotid and Cerebral Narrowing: The carotid arteries, the major blood vessels supplying blood to the brain, are prime targets for atherosclerotic plaque deposition. When high cholesterol narrows these pathways, cerebral blood flow diminishes.
Thrombotic and Embolic Strokes: Similar to coronary events, a plaque within a cerebral vessel can rupture, or a clot can form elsewhere in the body and travel upward to lodge in the narrow vessels of the brain. This cuts off oxygen supply to critical neural tissues, causing an ischemic stroke. The aftermath can range from transient ischemic attacks (TIAs) to permanent neurological deficits, including paralysis, speech impairments, and cognitive decline.
3. Peripheral Artery Disease (PAD)
Atherosclerosis is a systemic condition, meaning it affects arteries throughout the entire body, not just the core organs.
Restricted Mobility: When plaque accumulates in the arteries supplying the lower extremities (the pelvis, thighs, and calves), it causes Peripheral Artery Disease (PAD).
Symptoms and Severe Outcomes: The hallmark symptom of PAD is claudication, cramping, aching, or tired pain in the legs triggered by walking and relieved by rest. In advanced stages, severe arterial narrowing severely compromises tissue viability, leading to non-healing ulcers, chronic infections, and, in worst-case scenarios, critical limb ischemia requiring tissue amputation.
4. Compounding complications with metabolic syndrome and Diabetes
High cholesterol rarely occurs in a vacuum. It frequently interacts synergistically with other metabolic risk factors, compounding overall cardiovascular risk:
The Diabetes Nexus: Type 2 diabetes and insulin resistance characteristically lower protective high-density lipoprotein (HDL) levels while elevating triglycerides and small, dense LDL particles. High blood glucose damages the endothelial lining of blood vessels, accelerating the rate at which cholesterol plaques deposit and harden.
The Hypertension Feedback Loop: As arteries lose their elasticity due to stiffening plaque deposits, the heart must generate higher pressures to circulate blood throughout the body. This chronic hypertension places strain on the entire cardiovascular system, further injuring vessel walls and worsening the underlying atherosclerotic process.
Prevention and strategic management
Because high cholesterol is fundamentally asymptomatic until an acute crisis strikes, proactive screening and early intervention are essential. Managing lipid profiles requires a two-pronged approach:
Lifestyle Modification: Adopting a heart-healthy dietary pattern rich in soluble fiber (found in oats, beans, and lentils), replacing saturated and trans fats with unsaturated fats (such as olive oil and fatty fish), engaging in regular aerobic exercise, and eliminating tobacco use.
Medical Interventions: For individuals with genetic predispositions (such as familial hypercholesterolemia) or high calculated 10-year cardiovascular risk scores, lifestyle changes alone may be insufficient. In these cases, clinicians frequently prescribe pharmacotherapy, most commonly statins, to safely lower LDL levels, stabilize existing plaques, and dramatically reduce the incidence of fatal cardiovascular events.