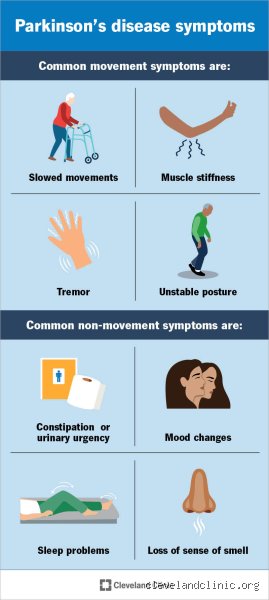
<h1>Understanding the Onset of Parkinson's Disease</h1> <p>Parkinson's disease is a complex neurodegenerative condition that typically develops gradually over an extended period. Because the early manifestations of the illness are often subtle and easily mistaken for normal signs of aging, recognizing how the condition truly begins requires looking far beyond the classic movement issues that usually bring patients to a clinical neurologist. For generations, medical science viewed this disorder strictly as a movement problem defined by shaking and rigid limbs. Modern research reveals a much broader picture, demonstrating that the biological cascade responsible for the disease begins years or even decades before a formal clinical diagnosis takes place.</p> <h2>The Hidden Early Indicators Before Movement Changes</h2> <p>Long before a person experiences any noticeable difficulty with coordination or walking, the underlying pathology of Parkinson's disease is often already at work within the central and peripheral nervous systems. One of the most common early indicators that frequently goes unrecognized is a gradual reduction or total loss of the sense of smell, medically known as anosmia or hyposmia. Individuals may find themselves unable to detect familiar scents like coffee, citrus fruits, or spices. This sensory deficit occurs because abnormal protein aggregates accumulate in the olfactory bulb and surrounding brain structures early in the disease process, impairing the neural pathways dedicated to processing odors long before motor regions sustain heavy damage.</p> <p>Another prominent non-motor forerunner involves sleep architecture disturbances, particularly rapid eye movement sleep behavior disorder (RBD). During normal rapid eye movement sleep, the body undergoes a state of temporary muscle paralysis to prevent individuals from physically acting out their dreams. When neurological pathways degenerate, this protective paralysis fails. Consequently, people may thrash, punch, kick, or vocalize loudly while dreaming, often startling their partners. Sleep specialists increasingly recognize rapid eye movement sleep behavior disorder as one of the most specific clinical predictors of future neurodegenerative conditions, serving as an early window into brainstem vulnerability.</p> <h2>Gastrointestinal and Autonomic Changes</h2> <p>The earliest origins of Parkinson's disease frequently involve regions outside the brain entirely, pointing to a gut-brain connection that has fascinated researchers for decades. Chronic, unexplainable constipation often plagues individuals years before any motor symptoms manifest. The enteric nervous system—the vast network of neurons embedded in the lining of the gastrointestinal tract—is heavily impacted by the same cellular pathology found in the brain. As nerve cells governing digestion begin to misbehave and lose function, intestinal motility slows down drastically. (Medical experts note that this gastrointestinal slowdown is frequently compounded by changes in autonomic regulation that also affect blood pressure control and bladder function.) Other non-motor signs include persistent fatigue that does not resolve with rest, unexplainable anxiety, and low mood or clinical depression that arises seemingly out of nowhere.</p> <h2>The Transition to Motor Symptoms</h2> <p>Eventually, the degenerative process advances toward the brain structures directly responsible for controlling physical movement, most notably a deep midbrain region called the substantia nigra. The neurons located here are responsible for producing dopamine, a vital chemical messenger that facilitates smooth, coordinated muscle activity. When a significant percentage of these dopamine-producing cells become damaged and die, the classic motor features of Parkinson's disease finally emerge into plain sight.</p> <p>For many individuals, the initial motor sign is a subtle, barely perceptible resting tremor affecting just one hand, fingers, or a single foot. This tremor is often described as a pill-rolling motion, where the thumb and forefinger rhythmically rub against each other. It typically appears when the limb is completely relaxed and tends to diminish temporarily when the person performs a purposeful action. However, not everyone experiences a tremor at the start; roughly thirty percent of individuals never develop significant shaking at all.</p> <p>Instead of a tremor, alternative patients experience an insidious onset of bradykinesia, which is the medical term for slowness of movement. Everyday tasks that once happened automatically—such as buttoning a shirt, tying shoes, cutting food, or walking at a normal pace—take markedly longer to complete. Handwriting often undergoes a distinct transformation, becoming noticeably smaller and cramped as the person continues to write across a page, a phenomenon known as micrographia. Muscles may grow stiff, rigid, and achy, particularly in the shoulders, hips, or limbs, creating a sensation that the body is operating under heavy resistance. Posture can subtly shift, and the natural swinging motion of the arms during walking may gradually diminish on one side of the body.</p> <h2>Conclusion of the Initial Phase</h2> <p>Understanding how Parkinson's disease starts requires appreciating its multifaceted nature. It is never a sudden event but rather a slow, continuous progression that bridges hidden internal changes with observable physical alterations. By identifying non-motor clues like olfactory loss, sleep disorders, and digestive slowdowns alongside early motor shifts, medical professionals hope to detect the condition much earlier, paving the way for future interventions that could alter its ultimate course.</p>
The Transition from Non-Motor to Motor Symptoms: Crossing the Threshold
While the initial years of Parkinson's disease are characterized predominantly by quiet, non-motor warning signs, the condition eventually crosses a clinical threshold. This transition marks the shift from the prodromal phase (pre-motor stage) to overt clinical Parkinson's disease.
As the accumulation of misfolded alpha-synuclein proteins progresses upward from the lower brainstem and peripheral nervous systems into the midbrain, it ultimately reaches the substantia nigra. This region is home to the specialized neurons responsible for producing dopamine, the chemical messenger critical for coordinating smooth, purposeful movement.
Once approximately 50% to 70% of these dopamine-producing cells are damaged or lost, the brain can no longer compensate smoothly. This cellular tipping point triggers the emergence of the classic physical movements historically associated with Parkinson's disease.
The First Physical Warning Signs: Subtle Motor Shifts
When motor symptoms finally manifest, they rarely arrive as an overwhelming physical collapse. Instead, they typically start subtly, often confined to one side of the body (asymmetric presentation), tricking individuals into attributing them to ordinary aging, arthritis, or a minor sports injury.
1. Bradykinesia (Slowness of Movement)
Bradykinesia is perhaps the most fundamental hallmark of early motor-stage Parkinson's.
Everyday impact: People notice that routine tasks take significantly longer. Buttoning a shirt, tying shoes, typing on a keyboard, or cutting food requires a conscious, deliberate effort rather than flowing automatically.
Physical expression: Individuals may notice a reduced arm swing on one side when walking, or a slight dragging of a single leg.
2. Resting Tremor
While not universal—some patients never experience a tremor—a characteristic resting tremor is often what drives a person to schedule a doctor's appointment.
Characteristics: Unlike tremors associated with other conditions (which worsen when reaching for an object), a Parkinson's tremor typically occurs when the limb is completely relaxed and unsupported.
It frequently begins in one hand or fingers—often famously described as a "pill-rolling" motion—and may temporarily subside when the hand begins an active task.
3. Micrographia (Changes in Handwriting)
Fine motor control is heavily impacted early on. One of the classic manifestations is micrographia, a gradual shrinking and cramping of handwriting.
4. Facial Masking and Soft Speech
Because motor control governs automatic expressions, the muscles of the face and throat can become rigid.
Hypomimia (Facial Masking): The face may take on a fixed, serious, or unexpressive appearance, even when the individual feels emotionally engaged or happy.
Hypophonia: Speech patterns may soften, becoming breathy, monotone, or difficult to project across a room.
Modern Diagnostic Challenges and the Future of Early Detection
Historically, diagnosing Parkinson's disease has relied entirely on a physical neurological examination once these core motor symptoms become visible. Physicians look for a combination of resting tremor, rigidity, and bradykinesia, often confirming the diagnosis retrospectively by observing how well the patient responds to dopamine-replacement medications.
However, waiting for motor symptoms to appear means that significant neural damage has already taken place. Modern neurology is shifting toward biological and biomarker-based definitions of Parkinson's.
Conclusion: Empowering Early Awareness
Understanding how Parkinson's disease usually starts—quietly in the gut, the olfactory system, and the sleep architecture years before affecting physical motion—redefines how medical science approaches neurodegeneration.
While experiencing isolated issues like constipation, temporary anxiety, or a diminished sense of smell does not mean an individual will develop Parkinson's, recognizing these constellations of early non-motor and subtle motor clues allows for unprecedented proactivity.
What specific aspect of neurological health or early symptom management would you like to explore further?