When you wake up with a nagging ache in your upper abdomen or a dull, persistent throb in your mid-back, your first instinct is rarely to suspect your internal organs. Most of us automatically assume we overdid it at the gym, slept in an awkward position, or strained a muscle while lifting groceries. Because musculoskeletal strain is a common, everyday ailment, we tend to frame physical discomfort through a mechanical lens: I pulled something.
However, the human body is a complex network of overlapping nerve pathways, and visceral pain—pain originating from an internal organ—does not always advertise its true source. Among the most commonly misunderstood and misattributed sources of visceral discomfort is the pancreas.
Can pancreas pain truly feel like a pulled muscle? The short answer is yes.
The Anatomical Illusion: Why Visceral Pain Misleads Us
To comprehend how a deep-seated digestive gland can feel like an exterior muscular injury, we must first look at where the pancreas lives and how it communicates with the brain.
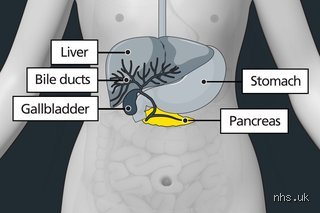
The pancreas is an elongated, spongy organ roughly six inches long, tucked deep behind the stomach in the upper left abdomen.
When a muscle is pulled or strained, specialized sensory receptors called nociceptors in the muscle fibers or connective tissue fire off signals through somatic nerve pathways. Somatic nerves are finely mapped; they allow your brain to pinpoint exactly where an injury has occurred (e.g., my left latissimus dorsi hurts right here when I twist).
Internal organs, by contrast, are innervated by the autonomic nervous system. Visceral pain fibers are sparse compared to somatic fibers, and they lack precise topographical mapping. When the pancreas becomes inflamed, irritated, or compressed, it does not send a neatly localized signal to the brain. Instead, it fires off dull, diffuse distress signals that travel along shared neural pathways.
Because the pancreas shares neurological real estate with the surrounding spine, rib cage, and back muscles, the brain often misinterprets the origin of the signal.
The Mechanics of Pancreatitis and Muscle Strain: A Comparative Breakdown
To the person experiencing the discomfort, a dull ache in the upper back or abdomen feels physical and localized, regardless of whether its origin is muscular or glandular. Yet, the underlying mechanisms driving a pulled muscle and a distressed pancreas are entirely different.
What Happens During a Muscle Strain?
A pulled muscle (or strain) occurs when muscle fibers are stretched beyond their normal limits or torn due to sudden exertion, heavy lifting, fatigue, or poor posture. This results in localized microscopic damage, inflammation, and localized muscle spasms.
Behavior with Movement: Musculoskeletal pain is mechanically driven. Bending, twisting, reaching, or pressing directly on the affected muscle triggers or intensifies the sharp, localized pain.
Behavior with Rest: Taking weight off the area, resting, applying ice or heat, and utilizing gentle stretches generally brings progressive relief.
Timeline: Muscle strains typically peak within 24 to 48 hours after the inciting event and steadily improve over the course of several days to a couple of weeks.
What Happens During Pancreatic Inflammation?
The pancreas produces vital digestive enzymes and hormones like insulin. When these enzymes become prematurely activated inside the organ—often triggered by gallstones, heavy alcohol consumption, high triglycerides, or certain medications—they begin to digest the pancreas itself. This condition, known as pancreatitis, triggers acute or chronic inflammation.
Behavior with Movement: Unlike a pulled muscle, pancreatic pain is largely decoupled from mechanical motion.
Twisting your torso, walking, or stretching will not alter the underlying ache. However, posture can play a distinct role: many individuals with pancreatitis find temporary, albeit partial, relief by leaning forward or curling into a fetal position, which takes pressure off the retroperitoneal space. Conversely, lying flat on the back often dramatically worsens the discomfort. Behavior with Food: This is the ultimate differentiator. Pancreatic pain is intimately tied to digestion. Because the pancreas is forced to secrete enzymes when food enters the GI tract, eating—especially high-fat meals—frequently causes a sharp escalation in pain within minutes to hours. A pulled muscle does not care whether you ate a salad or a cheeseburger; a struggling pancreas does.
Timeline: Pancreatic pain is persistent, deep, and steady.
It does not resolve with a good night's sleep or a muscle relaxant. In acute cases, it builds rapidly and remains constant for days unless medically managed.
The "Boring" Pain Profile and Radiating Patterns
Patients who have experienced both a severe back spasm and pancreatic inflammation frequently note distinct qualitative differences in how the pain feels, even if both initially present as a dull ache in the mid-back.
Musculoskeletal pain is often described as sharp, stabbing, or aching, and it is usually confined to a specific spot that feels tender to the touch when you press on it.
Pancreatic pain, on the other hand, is classically described by gastroenterologists as boring, gnawing, or deep.
Red Flag Symptoms That Rule Out a Pulled Muscle
Because early pancreatic symptoms can masquerade as common musculoskeletal complaints or routine indigestion, looking exclusively at the pain location is insufficient. The body usually provides accompanying systemic clues when an internal organ is in distress.
If your back or upper abdominal discomfort is actually stemming from the pancreas rather than a pulled muscle, you will typically notice secondary symptoms that have nothing to do with a physical injury:
Digestive Distress and Changes in Stool: Since the pancreas is responsible for manufacturing digestive enzymes, its dysfunction directly impacts nutrient absorption. Individuals with chronic pancreatic issues often experience steatorrhea—stools that are pale, oily, bulky, foul-smelling, and notoriously difficult to flush.
Nausea, Vomiting, and Loss of Appetite: The systemic inflammatory response triggered by pancreatitis frequently slows down the digestive tract, resulting in persistent nausea, episodic vomiting, and a profound aversion to food.
Unexplained Weight Loss: Chronic pancreatic dysfunction prevents proper calorie and nutrient breakdown, leading to steady, unintentional weight loss even when dietary intake remains normal.
Jaundice: If inflammation, a cyst, or a mass near the head of the pancreas blocks the common bile duct, bilirubin backs up into the bloodstream. This causes a yellowing of the skin and the whites of the eyes, often accompanied by dark, tea-colored urine.
Sudden Blood Sugar Dysregulation: Because the pancreas houses the islets of Langerhans (which produce insulin and glucagon), severe or progressive pancreatic damage can impair glucose regulation, sometimes resulting in the sudden onset of secondary diabetes.
A pulled muscle will cause localized stiffness, soreness, and temporary movement restrictions, but it will never cause your stool to float, your skin to turn yellow, or your blood sugar to spike unpredictably.
Common mistakes and misconceptions
When evaluating upper abdominal and mid-back discomfort, it is remarkably easy to misinterpret internal organ distress as a routine physical injury. Because the symptoms of conditions like pancreatitis can overlap with musculoskeletal complaints, several persistent misconceptions often delay proper medical evaluation. Understanding these pitfalls can prevent dangerous missteps in personal health management.
Assuming all torso pain is mechanical or fitness-related
A frequent error is automatically attributing upper body discomfort to a recent workout, heavy lifting, or poor posture. People frequently assume that a dull ache or sharp spasm in the upper abdomen or mid-back is simply a pulled muscle or a strained intercostal muscle.
While musculoskeletal strains are common, they typically follow a clear triggering event, such as intense physical exertion or an awkward twist.
Misreading the role of food and posture
Another common misconception involves how the pain responds to daily activities. Individuals experiencing musculoskeletal back or core strains usually notice that specific movements—like bending, twisting, or sitting upright—directly aggravate the soreness, while lying completely still brings relief.
With pancreatic distress, the rules change entirely:
The eating trigger: Pancreatic pain frequently flares up or intensifies within minutes to hours after eating, particularly following meals high in fat or heavy carbohydrates, because the organ is actively stimulated to release digestive enzymes.
The positional paradox: While a pulled muscle hurts worse when stretched, pancreatic pain often temporarily eases when a person curls into a fetal position or leans sharply forward.
This posture slightly decompresses the retroperitoneal space where the pancreas resides, reducing pressure on surrounding nerves. Mistaking this positional relief for a strained back muscle stretching out can delay crucial diagnostic imaging.
Ignoring the crucial accompanying systemic signs
Perhaps the most hazardous mistake is looking at the pain in complete isolation. A pulled muscle is generally an isolated local issue—it hurts to move the affected tissue, but the rest of the body functions normally.
Pancreatic inflammation, however, is a systemic event that almost always triggers accompanying biochemical and gastrointestinal distress. Dismissing upper abdominal or back discomfort while ignoring subtle red flags—such as persistent nausea, unexplained low-grade fever, rapid heart rate, sudden digestive changes, or an unexplained drop in weight—can lead to severe medical complications.