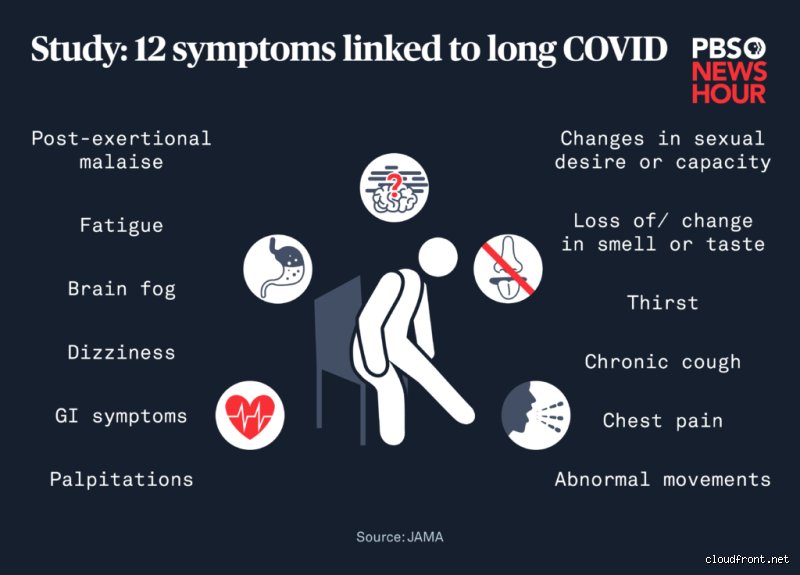
Unraveling the chronicity of long COVID: Are symptoms permanent?
To answer this question accurately, modern clinical research must move past generalized assumptions and examine longitudinal data, underlying biological mechanisms, and the distinction between permanent organ damage and chronic post-viral dysregulation. Current epidemiological data tracking patients over multi-year spans reveal a nuanced reality: while complete, rapid remission can be elusive for many, long-term permanence is not the universal rule. Instead, recovery often unfolds as a slow, non-linear trajectory of incremental improvement rather than an overnight cure.
The evolving recovery timeline: What Multi-Year data show
Long-term cohort studies tracking patients months and years post-infection provide critical insight into how symptoms progress or resolve over time. Landmark findings, such as those from large-scale observational networks and multi-year follow-ups published in journals like the Annals of Internal Medicine, demonstrate that recovery trajectories vary dramatically based on symptom phenotype, initial viral variant, and individual host characteristics (Bergeson, 2026).
Gradual Improvement vs. Full Remission: Data indicate that roughly half of individuals experiencing long COVID symptoms at the one-year mark achieve meaningful, sustained improvement by the three-year milestone. However, rates of complete symptom remission are notably lower, with roughly one in four adults reaching total resolution within a three-year window.
Variant and Symptom-Specific Trajectories: The nature of the initial infection matters. For instance, individuals whose primary long COVID manifestations involve sensory alterations, such as persistent loss of taste or smell, frequently experience higher rates of long-term recovery compared to those battling multi-system manifestations. Conversely, symptom clusters dominated by profound fatigue, cognitive impairment ("brain fog"), and post-exertional malaise (PEM) tend to exhibit a more persistent, chronic course.
Pathophysiological drivers: Why do symptoms linger?
To understand whether long COVID symptoms are permanent, researchers must decipher why they persist long after the acute SARS-CoV-2 virus has cleared from the upper respiratory tract. Several primary pathophysiological mechanisms have been identified as central drivers of chronic post-COVID illness:
Viral Persistence and Reservoir Storage: Autopsy and tissue biopsy studies have uncovered evidence of lingering SARS-CoV-2 viral RNA and viral proteins sequestered within deep tissue reservoirs, including the gut mucosa, lymph nodes, and olfactory bulbs, months or even years after initial infection. This ongoing local presence can drive chronic, low-grade immune activation.
Immune Dysregulation and Autoimmunity: Long COVID is frequently characterized by sustained systemic inflammation, abnormal cytokine profiles, and the reactivation of latent latent viruses such as the Epstein-Barr virus (EBV). The production of autoantibodies targeting the body's own tissues can maintain a self-perpetuating cycle of immune-mediated injury.
Endothelial Injury and Microvascular Dysfunction: The lining of blood vessels (the endothelium) expresses ACE2 receptors, making it a prime target for SARS-CoV-2. Damage to the microvasculature can lead to impaired tissue oxygenation, endothelial dysfunction, and the formation of microscopic blood clots (microthrombi), contributing to chronic muscular fatigue and cognitive dysfunction.
Autonomic Nervous System Disruption: Many patients suffer from dysautonomia, most notably postural orthostatic tachycardia syndrome (POTS). Damage or functional dysregulation within the autonomic nervous system disrupts heart rate variability, blood pressure regulation, and vascular tone, explaining symptoms like dizziness, palpitations, and exercise intolerance.
Structural damage versus Functional Dysregulation
A vital distinction in answering the permanency question lies in separating structural tissue destruction from functional dysregulation:
Structural Sequelae: In a minority of patients, particularly those who suffered severe acute illness requiring intensive care hospitalization, persistent symptoms are tied to permanent structural alterations, such as pulmonary fibrosis (scarring of lung tissue) or permanent myocardial injury. Once structural scarring occurs, it is generally considered permanent, though the body can adapt over time through pulmonary and cardiac rehabilitation.
Functional Sequelae: For the vast majority of long COVID sufferers, particularly those with mild initial infections, testing often reveals normal structural imaging (such as clear chest X-rays and standard cardiac scans). Their symptoms stem from functional abnormalities, such as mitochondrial energy production deficits, localized neuroinflammation, or metabolic dysfunction. Because these processes do not represent fixed structural destruction, they possess a higher theoretical capacity for long-term healing and cellular repair.
Clinical management and the path forward
Because there is currently no single universal pharmacological cure for long COVID, medical management relies heavily on a targeted, multi-disciplinary approach. Clinicians focus on mitigating dominant symptoms, utilizing pacing strategies to manage post-exertional malaise, treating underlying autonomic dysfunction, and supporting patients through structured rehabilitation protocols tailored to individual energy envelopes.
While the road to recovery can be frustratingly protracted, the prevailing medical consensus rejects the notion that long COVID is universally permanent for all who contract it. Continued clinical trials investigating antiviral therapies, immune-modulators, and targeted metabolic treatments aim to accelerate this natural healing curve in the years ahead.
Understanding Long-Term Trajectories and recovery patterns
As longitudinal data matures, medical science is moving away from broad generalizations and toward granular, data-backed insights regarding post-acute sequelae. Large-scale cohort studies tracking patients over multi-year windows reveal that while the colloquial fear of "permanent damage" is understandable, the clinical reality is far more nuanced.
Recent findings published in leading medical literature, including landmark three-year follow-up analyses, demonstrate that long COVID is not a static, irreversible state for everyone, nor is it a brief hurdle that vanishes overnight. Instead, recovery often unfolds across protracted timelines, characterized by distinct biological trajectories, periodic relapses, and gradual physiological adaptation.
What the Multi-Year data reveals about Remission
For individuals grappling with persistent symptoms months or years after an initial infection, the central question remains: do symptoms eventually resolve?
Current epidemiological data paints a picture of slow, incremental improvement:
Gradual Improvement vs. Full Remission: Approximately half of adults living with long COVID a year post-infection experience meaningful symptom reduction by the three-year mark. However, complete symptom remission, a return to baseline health across all organ systems, occurs in roughly one in four adults over that same period.
Variant Differences: Individuals infected during later viral waves (such as the Omicron era) exhibit higher rates of sustained improvement compared to those affected by earlier wild-type strains, highlighting the mitigating impact of viral evolution, partial immunity, and vaccination.
Symptom-Specific Trajectories: The rate of resolution varies significantly depending on the dominant clinical phenotype. Sensory issues, such as altered smell or taste, demonstrate higher rates of long-term recovery, whereas multi-system clusters involving neurocognitive difficulties ("brain fog") or profound fatigue often follow a more stubborn, relapsing-remitting course.
Key factors influencing Long-Term Persistence
Why do some individuals recover within months while others experience multi-year symptoms? Clinical research highlights several overlapping biological drivers and risk factors:
+-------------------------------------------------------------------+
| PRIMARY DRIVERS OF SYMPTOM PERSISTENCE |
+-------------------------------------------------------------------+
| • Immune Dysregulation: Persistent low-grade inflammation and |
| autoantibody production targeting healthy tissues. |
| • Viral Persistence: Residual viral reservoirs or RNA fragments |
| undetected in routine blood work lingering in tissues.|
| • Endothelial Dysfunction: Microvascular injury affecting blood |
| flow, tissue oxygenation, and autonomic regulation. |
+-------------------------------------------------------------------+
Individual baseline health, demographic variables, and the severity of the initial acute infection play critical roles in shaping whether symptoms become chronic.
Clinical management and the shift toward pacing
In the absence of a universal curative pharmaceutical intervention, modern clinical management relies on a personalized, symptom-targeted approach. Rather than forcing rigorous exercise regimens, which can trigger severe post-exertional malaise (PEM) in patients with energy-limiting profiles, guidelines increasingly emphasize energy envelope management or "pacing".
Comprehensive care also involves ruling out secondary mimics, such as thyroid dysfunction or new-onset metabolic shifts, ensuring that treatable overlapping conditions are addressed to alleviate overall systemic burden. While navigating multi-year symptoms demands patience and specialized multidisciplinary support, the accumulating evidence shows that the human body retains an ongoing capacity for repair and adaptation over time.