The chronology conundrum: Can Long COVID emerge years down the line?
For years, the conventional clinical consensus framed Long COVID as a continuation of acute illness—a relentless, unbroken chain of symptoms where a patient never quite recovers from the initial infection. But as we look at population data and longitudinal cohorts, a more unsettling question arises: Can Long COVID come on years later? Can a person contract the virus, seemingly bounce back with zero residual issues, and then suddenly develop full-blown, chronic post-viral illness months or even years down the road?
Unpacking the timeline: Persistent residue vs. Delayed onset
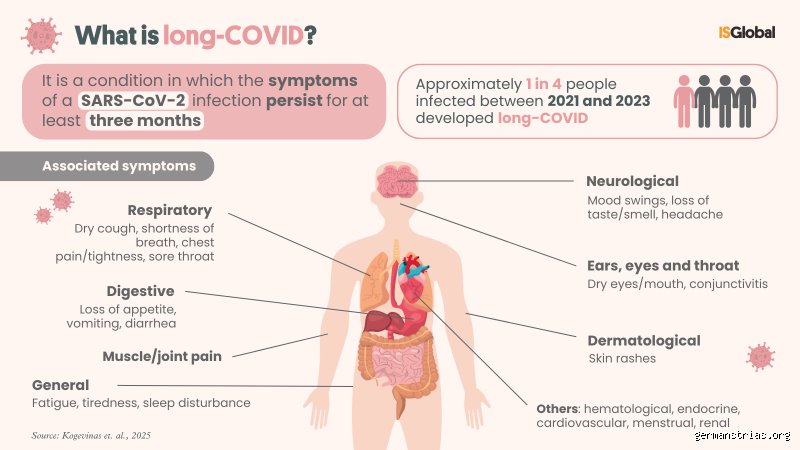
To understand whether Long COVID can manifest years later, we first have to clarify how researchers define its onset. In standard epidemiological tracking, such as data compiled by institutions like the U.S. Centers for Disease Control and Prevention (CDC) or the National Institutes of Health (NIH), Long COVID is typically diagnosed when symptoms persist or develop past three months post-infection.
However, medical history shows us that post-viral syndromes are rarely straightforward. Consider historical analogs like Myalgic Encephalomyelitis/Chronic Fatigue Syndrome (ME/CFS), which has frequently been triggered by Epstein-Barr virus or influenza. In many cases, patients report a "honeymoon period" of apparent full recovery lasting several months before a sudden, precipitous crash into chronic dysfunction.
“Post-viral illness does not always march in a straight line. Often, the body compensates quietly in the background, masking systemic damage until a secondary trigger, like physical stress, a reinfection, or normal aging, exceeds the biological tipping point.”
When examining modern cohorts, researchers tracking patient health records note a subtle but crucial distinction: true "delayed-onset" Long COVID (where a patient is entirely asymptomatic for a prolonged window before symptoms appear) versus "subclinical smoldering," where low-grade inflammation, viral persistence in tissues like the gut or brain, and immune dysregulation silently erode organ systems without immediately setting off alarm bells.
The biological engine: Why symptoms Can seemingly sleep
To see how a condition can appear long after the initial pathogen has cleared the upper respiratory tract, we have to look at what SARS-CoV-2 leaves behind. Multiomic tissue profiling studies have demonstrated that viral remnants, or viral reservoirs, can linger in hidden pockets of the body, such as the gastrointestinal tract, lymph nodes, and neural tissues, long after acute PCR tests turn negative.
Think of it like a slow-burning ember buried deep under forest mulch. For months, the forest looks green and healthy on the surface. But the heat remains. Over time, that localized immune activation can trigger several delayed processes:
Molecular Mimicry and Autoimmunity: The immune system, confused by lingering viral proteins, begins mistakenly attacking the body's own healthy tissues, leading to delayed-onset neuropathies or vascular damage.
Endothelial Dysfunction: Chronic, low-level damage to the inner lining of blood vessels can take years to manifest as overt cardiovascular or cognitive symptoms.
Dopaminergic and Neurological Disruption: Recent neuroimaging and biomarker studies from late 2026 highlight how subtle damage to dopamine-releasing neurons can slowly accumulate, eventually crossing a threshold where fatigue and brain fog become debilitating, even if the initial infection happened years prior.
Real-World context: Names, dates, and data
To ground these mechanisms in reality, we can look at documented longitudinal tracking. In major metropolitan health systems, such as those studied across large electronic health record networks in the United States and Europe, epidemiologists have tracked patients from the early waves of 2020 and 2021.
For instance, in a comprehensive retrospective cohort analysis published from the University of Iowa Carver College of Medicine, researchers tracked long-term cardiovascular, renal, and pulmonary trajectories. They noted that patients who suffered mild or even asymptomatic initial cases, perhaps catching an early strain during the peak wave in New York in April 2020, frequently walked away feeling completely fine. Yet, subsets of these individuals began presenting with new-onset autonomic dysfunction, postural orthostatic tachycardia syndrome (POTS), or unexplained organ strain well over a year later, often catalyzed by a subsequent, seemingly minor viral exposure or reinfection.
Similarly, data from large-scale European health surveillance registries (such as those analyzed in Barcelona and other regional health departments) emphasize that the cumulative risk of chronic post-viral complications scales dramatically with each successive infection. A person who brushed off their first COVID-19 case in 2021 might find that their biological resilience is entirely depleted by a third or fourth infection years later, effectively pushing them across the threshold into chronic illness.
Understood.