Can you catch mono twice? Understanding the biology, myths, and realities of infectious mononucleosis
Given how miserable the experience is, a question frequently haunts those who have successfully recovered: Can you catch mono twice? If you find yourself battling a crushing wave of fatigue, a fever, and a raw throat months or years after your first bout, it is completely natural to wonder if the virus has returned for a second round.
To answer this question accurately, we have to look past internet myths and examine how the underlying virus behaves inside the human body. While experiencing "mono-like" symptoms more than once is entirely possible, catching a true, classic case of infectious mononucleosis a second time from the same primary pathogen is exceptionally rare.
The culprit: Meet the Epstein-Barr virus
To understand why getting mono twice is so uncommon, you first need to understand what causes it. The overwhelming majority of infectious mononucleosis cases, roughly 90% or more, are triggered by the Epstein-Barr virus (EBV), a very common member of the herpesvirus family.
EBV is remarkably widespread. Epidemiological studies show that a vast majority of the global population contracts EBV at some point in their lives, often during early childhood. When young children catch EBV, their immune systems typically handle it quietly, causing very mild symptoms or none at all. However, when a person is first infected later in life, typically during adolescence or young adulthood, the immune system reacts much more aggressively, triggering the full-blown syndrome known as infectious mononucleosis.
The virus spreads primarily through bodily fluids, most notably saliva. This explains its transmission routes, sharing drinking glasses, utensils, or toothbrushes, as well as kissing. Once EBV enters a new host, it invades specific types of immune cells (primarily B-lymphocytes) and establishes a permanent residence in the body.
Lifelong Immunity and viral latency
Once your immune system mounts its initial defense and clears the acute phase of mononucleosis, it creates a specialized army of antibodies and memory T-cells designed to recognize EBV. This is where the concept of lifelong immunity comes into play.
Unlike transient viruses like the common cold or influenza, which mutate rapidly and can infect you over and over again, EBV remains stable, and your immune system never forgets it. Because your body retains these defensive antibodies, you cannot typically "catch" EBV from an external source a second time.
Instead, the virus shifts into a phase called latency. It does not vanish from your system; rather, it goes to sleep inside your white blood cells, remaining inactive for the rest of your life. For the vast majority of people, this dormant virus stays quiet permanently, kept firmly in check by a vigilant immune system.
Because your immune system maintains a permanent structural defense against EBV, a true reinfection, meaning catching a fresh strain from someone else who is shedding the virus, is virtually non-existent in immunocompetent individuals. Your body already knows the blueprint of the virus and neutralizes it before it can cause a new primary infection.
Differential diagnosis: Mimics and alternative pathogens
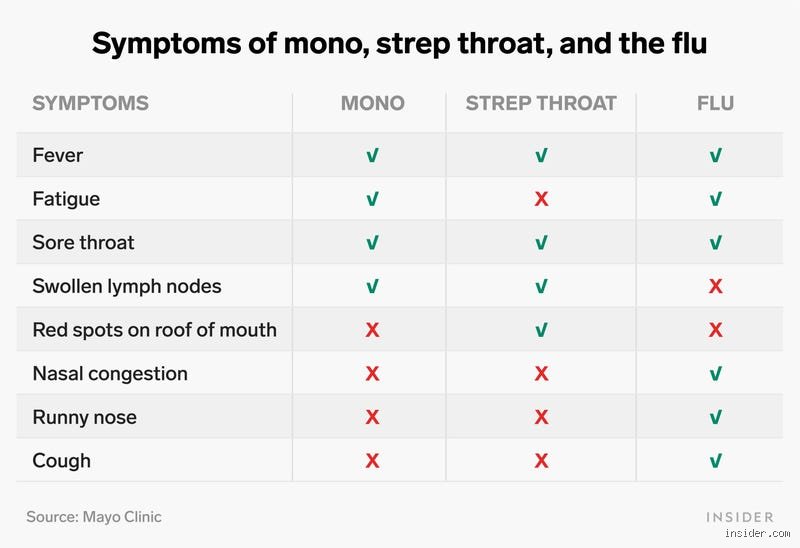
When a patient presents with classic signs of infectious mononucleosis, such as severe pharyngitis, posterior cervical lymphadenopathy, profound fatigue, and low-grade fever, yet has a documented history of a prior EBV-induced mono infection, clinicians must look beyond primary Epstein-Barr virus. True clinical recurrences of acute EBV mononucleosis are exceedingly rare because initial infection confers lifelong humoral and cellular immunity. Therefore, experiencing identical symptoms usually points toward alternative pathogens capable of producing a "mononucleosis syndrome."
The most prevalent mimic is Cytomegalovirus (CMV), another member of the herpesvirus family. While CMV mononucleosis shares many overlapping features with EBV, including prolonged fatigue, atypical lymphocytosis, and elevated hepatic transaminases, it frequently presents with a milder sore throat and less pronounced lymph node enlargement, though high fevers remain common.
Other notable non-EBV triggers include:
Toxoplasma gondii: A parasitic infection typically contracted through contact with contaminated soil or undercooked meat, presenting with prominent lymphadenopathy.
Primary HIV Seroconversion: Acute human immunodeficiency virus infection can closely mimic mononucleosis, underscoring the importance of comprehensive viral screening in at-risk populations.
Adenovirus and Hepatitis Viruses: Pathogens that can induce generalized malaise, pharyngitis, and hepatic inflammation.
Differentiating between true EBV persistence, viral reactivation, and an entirely separate pathogen requires specific serological panels, including viral capsid antigen (VCA) antibodies, Epstein-Barr nuclear antigen (EBNA) status, and CMV-specific IgM and IgG testing.
Long-Term management and Post-Viral sequelae
For the vast majority of individuals, recovery from infectious mononucleosis is gradual but complete. However, understanding why the body feels persistently drained long after the acute phase resolves is critical for proper recovery.
The reality of Post-Viral fatigue
While acute symptoms like fever and sore throat typically subside within two to four weeks, the hallmark exhaustion can linger. Post-viral fatigue syndrome occurs because the immune system expends vast energetic resources managing cellular inflammation and keeping the latent virus under control. Pushing through this fatigue too quickly often delays recovery, making structured rest and gradual re-entry into daily activities essential components of medical advice.
Splenic safety and activity restrictions
A vital clinical priority during any acute mononucleosis presentation, whether primary or a secondary mimic, is protecting the spleen. Transient splenomegaly (enlargement of the spleen) occurs in a significant percentage of cases, rendering the organ vulnerable to trauma. Physicians universally advise abstaining from contact sports, heavy weightlifting, and high-impact physical exertion for a minimum of three to four weeks, or until ultrasound imaging confirms the spleen has returned to its normal physiological dimensions. Ignoring these precautions risks splenic rupture, a medical emergency requiring immediate surgical intervention.
Summary and clinical takeaways
To encapsulate the core question: Can you catch mono twice?
Lifelong Immunity: True reinfection with the Epstein-Barr virus resulting in a second primary case of acute mononucleosis is biologically exceptional. Once encountered, the immune system maintains immunological memory.
The Latent Reservoir: EBV remains dormant within B-lymphocytes for life. While minor asymptomatic viral shedding or reactivation can occur under conditions of severe physiological stress or immunosuppression, it rarely manifests as the classic, full-blown acute syndrome.
The Culprits Behind "Second Times": When individuals believe they have caught mono a second time, they are usually experiencing a mononucleosis-like syndrome caused by a completely different infectious agent, such as Cytomegalovirus or toxoplasmosis, or dealing with prolonged post-viral fatigue from the initial infection.
Navigating persistent exhaustion or recurrent systemic symptoms warrants professional medical evaluation rather than assumption. Comprehensive diagnostic blood work remains the only definitive method to map antibody profiles, rule out alternative pathogens, and ensure a safe, monitored path back to full health.